Related Experiment Video
Updated: Jul 9, 2026
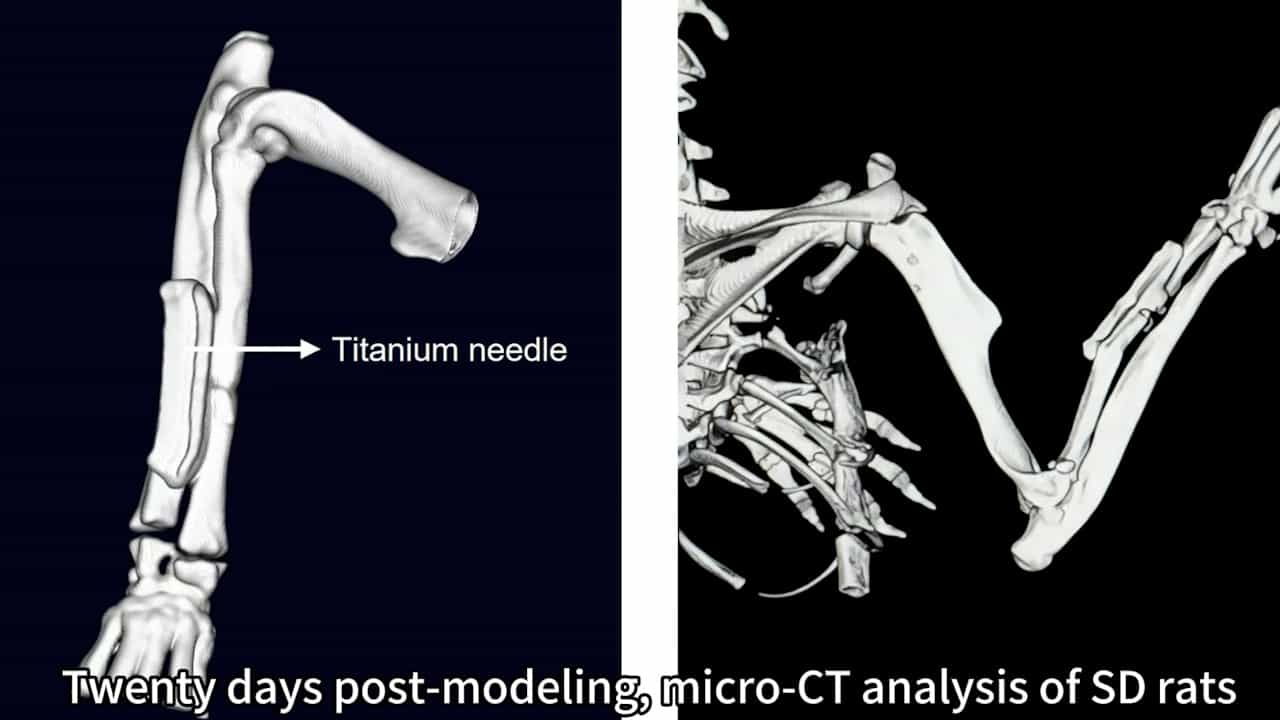

Development of a Novel Internal Fixation Model for Rat Radial Fractures: Fracture Healing Assessment and Dorsal Root Ganglion Isolation
Published on: March 13, 2026
Workers' compensation status is associated with increased complications following distal radius fracture open
Sai Prasada Rao K Manikonda1, Kaleb J Patterson1, Joshua M Varghese1
1Department of Orthopedic Surgery, Baylor College of Medicine, Houston, TX, USA.

Abstract:
BackgroundWhile workers' compensation (WC) patients often experience worse orthopedic outcomes, complication patterns following distal radius fracture (DRF) open reduction and internal fixation (ORIF) remain poorly defined. Prior DRF-specific studies include only small, regional cohorts. This study leverages Epic Cosmos to conduct the first nationwide analysis comparing complications between WC and non-WC populations.MethodsThis retrospective study queried the Epic Cosmos database for DRF ORIF procedures (2017-2024). WC patients (N = 4,101) were matched 1:5 with non-WC patients (N = 20,505) based on demographic and comorbidity characteristics. Patients required ≥6-month follow-up (mean 48.2 ± 28.6 and 48.9 ± 27.3 months for WC and non-WC patients, respectively). A subgroup analysis excluding patients with prior tendon injuries evaluated if WC status independently contributed to complication risk.ResultsWC patients had higher odds of complex regional pain syndrome (CRPS) (1.6% vs. 0.8%; OR 2.17, 95% CI [1.60, 2.91], p < 0.001), subsequent hardware removal (14.7% vs. 10.4%; OR 1.48, 95% CI [1.34, 1.63], p < 0.001), and postoperative stiffness (21.1% vs. 19.0%; OR 1.14, 95% CI [1.04, 1.23], p = 0.003), and lower odds of skin infection (2.9% vs. 4.0%; OR 0.73, 95% CI [0.59, 0.88], p = 0.001); all four associations remained significant after Bonferroni correction. No differences existed for venous thromboembolism, myocardial infarction, pulmonary embolism, or mechanical complication. Excluding prior tendon injury, CRPS remained significantly elevated in WC patients (OR 2.62, 95% CI [1.92, 3.57], p < 0.001).ConclusionsWC status is associated with higher risks of CRPS, subsequent hardware removal, and stiffness. Notably, CRPS risk remains elevated even after controlling for prior tendon injuries. As the largest WC-specific complication analysis for DRF ORIF to date, this exploratory study suggests that payer status may be a clinically meaningful correlate of postoperative morbidity. Future prospective studies are needed to confirm these associations.

