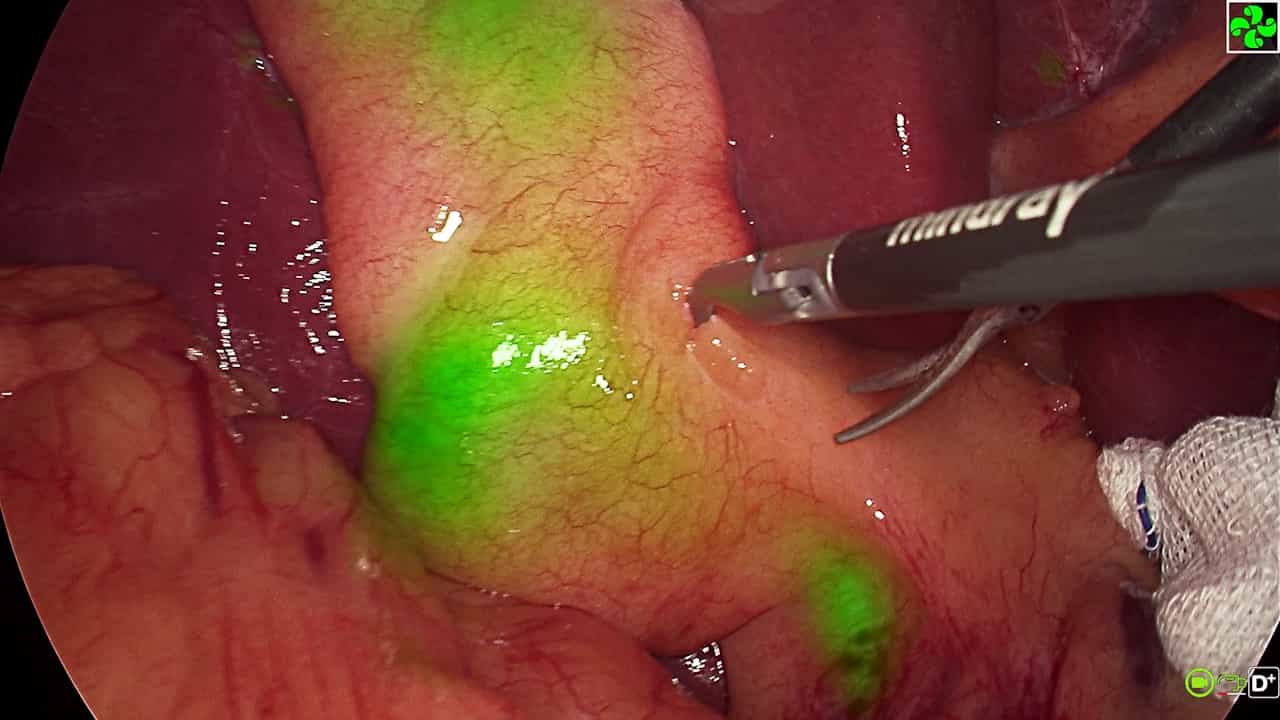
Related Experiment Video
Updated: Jul 14, 2026
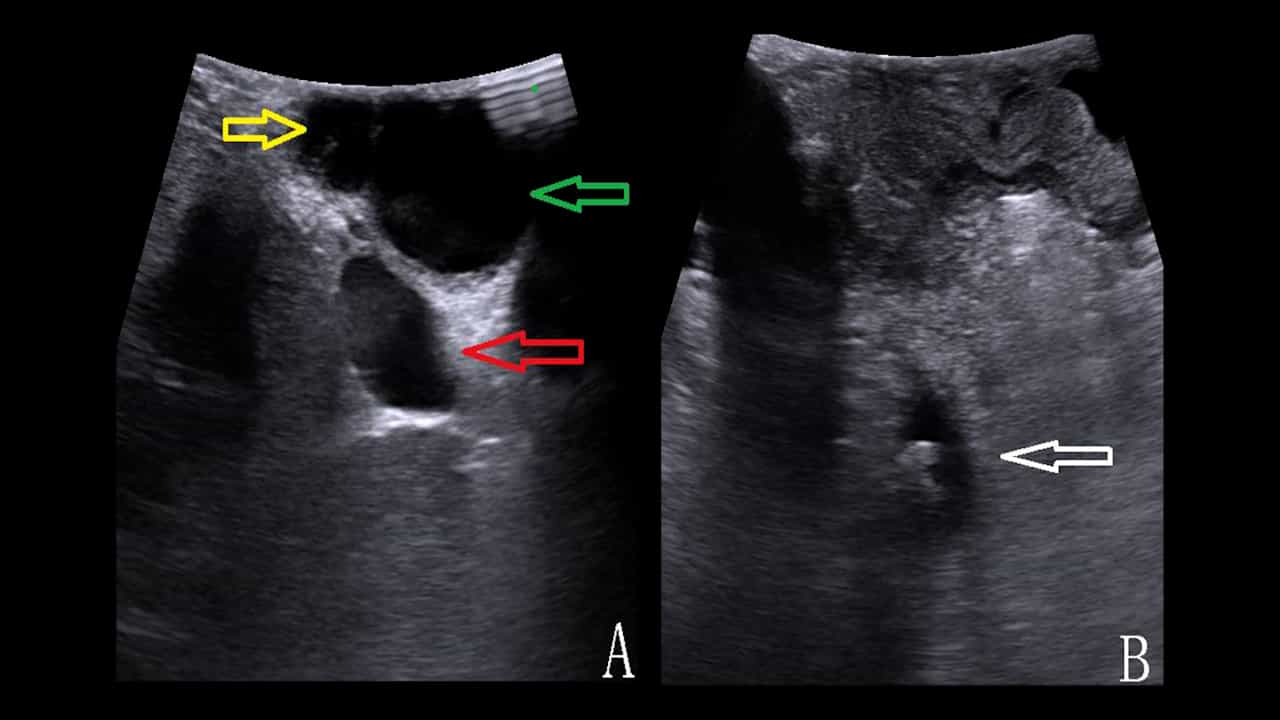

Application of Laparoscopic Ultrasonography in Primary Choledochal Suture during Combined Two-lens Surgery
Published on: March 28, 2025
Outcomes and complications of three-incision versus single-incision laparoscopic cholecystectomy: a systematic review
Mosab Said1, Ahmad Alzyoud2, Fadi Alkhawaja3
1Faculty of Medicine, The Yarmouk University, Irbid, Jordan. mosabsaeed155@gmail.com.

Background:
Laparoscopic cholecystectomy (LC) is widely regarded as the gold-standard for the management and treatment of gallbladder disease. Traditionally, LC has been performed using multiple small incisions to allow placement of trocars and instruments. However, single-incision laparoscopic surgery has emerged as a potential alternative, purportedly offering cosmetic and recovery benefits, though the evidence for these advantages remains inconsistent in the literature.
Methods:
Nine studies published between 2010 and 2019, enrolling a total of 1,884 patients, were eligible for inclusion. A systematic review and meta-analysis methodology was employed adhering to PRISMA guidelines. Outcomes included conversion to open or additional-port surgery, operative time, postoperative hospital stay, biliary complications, postoperative wound infection, port-site (umbilical) hernia, and postoperative pain. Sensitivity analysis were performed using the leave-one-out method and restricted to randomized controlled trials (RCT-only analysis).
Results:
There was no statistically significant difference between single-incision laparoscopic cholecystectomy (SILC) and three-incision laparoscopic cholecystectomy (TILC) in terms of conversion rate (OR 1.05, 95% CI 0.64-1.72; P = 0.84), postoperative hospital stay (MD - 0.05 days, 95% CI - 0.11 to 0.02; P = 0.14), wound infection (OR 1.35, 95% CI 0.58-3.16; P = 0.48), port-site umbilical hernia (OR 1.80, 95% CI 0.17-19.60; P = 0.63), biliary complications, or postoperative pain (MD - 0.07, 95% CI - 0.21 to 0.07; P = 0.32; I2 = 24%). Operative time was significantly longer in the SILC group (MD + 17.45 min, 95% CI 8.28-26.62; P = 0.0002; I2 = 97%).
Conclusion:
In carefully selected low-risk patients undergoing elective laparoscopic cholecystectomy, SILC is technically feasible and is not associated with significantly higher rates of conversion, wound infection, biliary complications, port-site hernia, prolonged hospital stay, or pain compared with TILC. However, SILC is associated with a statistically significant increase in operative time. These findings support SILC as an acceptable alternative to TILC in elective, low-complexity settings at experienced centres. They should not be extrapolated to patients with acute cholecystitis, significant obesity, or prior abdominal surgery, for whom the evidence base remains insufficient. High-quality randomized controlled trials including these populations are warranted.