Related Experiment Video
Updated: Jul 10, 2026


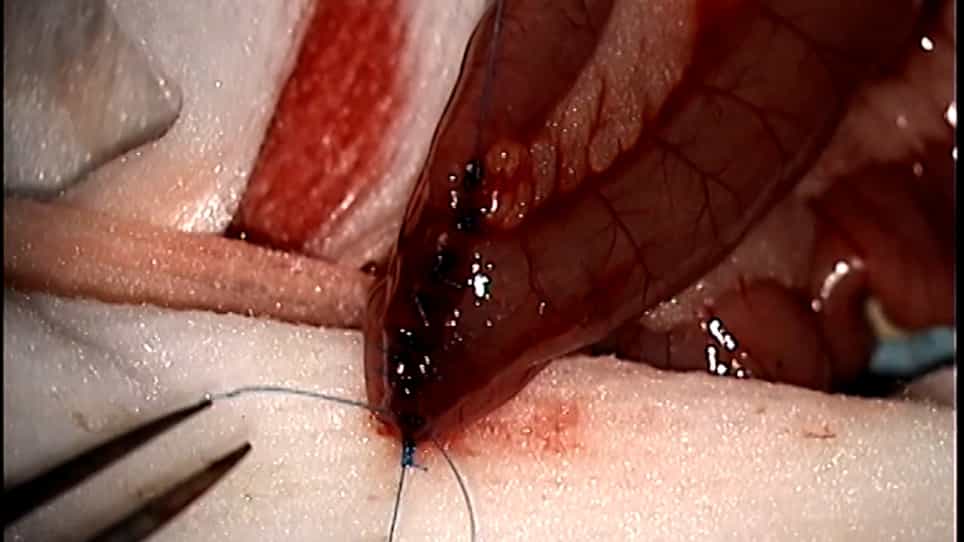
Techniques of Sleeve Gastrectomy and Modified Roux-en-Y Gastric Bypass in Mice
Published on: March 20, 2017
Sleeve gastrectomy versus Roux-en-Y gastric bypass for nonalcoholic fatty liver disease: a systematic review and
Chenming Liu1, Rui Lu2, Wenyuan Tang3
1Department of Surgery, School of Medicine, Zhejiang University, Hangzhou, China.

Background:
The efficacy of sleeve gastrectomy (SG) and Roux-en-Y gastric bypass (RYGB) in the treatment of nonalcoholic fatty liver disease (NAFLD) has not been fully elucidated.
Objectives:
The purpose of this systematic review and meta-analysis is to provide reliable evidence for clinical interpretation of the advantages and disadvantages of RYGB and SG in the treatment of NAFLD by directly comparing the efficacy of RYGB and SG in the treatment of NAFLD.
Setting:
All over the world.
Methods:
PubMed, Embase, Web of Science, and ClinicalTrials.gov were searched for relevant articles up to December 2025. Mean difference (MD) and 95% confidence interval (CI) were used for quantitative synthesis of continuous variables, and risk ratio and 95% CI were used for quantitative analysis of categorical variables. The primary outcomes of the study were changes in NAFLD activity score (NAS), fibrosis stage, and changes in liver enzymes (including alanine aminotransferase and aspartate aminotransferase) from initial to follow-up. Secondary outcomes included changes in body weight, body mass index, percentage total weight loss, and percentage excess weight loss.
Results:
A total of 16 original studies were included in our final meta-analysis. Our primary analysis showed no significant overall difference between SG and RYGB in improving NAS (MD = .23, 95% CI: .69-1.16). Exploratory subgroup analyses suggested potential time-dependent patterns, although these varied by outcome: longer-term follow-up (> 1 year) was associated with a point estimate favoring RYGB for NAS (MD = .75, 95% CI: .03-1.47), but favoring SG for alanine aminotransferase reduction (MD = -5.92, 95% CI: -8.24 to 3.60). No significant between-group difference was observed for aspartate aminotransferase changes (P = .18), and RYGB was associated with greater weight loss. Given the exploratory nature of these subgroup analyses, these findings should be interpreted cautiously and considered hypothesis-generating. Metaregression analysis revealed that the difference in weight loss between procedures was significantly associated with the effect size for NAS improvement (β = -.11, 95% CI: -.21 to .01, P = .032) and accounted for 100% of the between-study heterogeneity (R2 = 100%).
Conclusions:
Although our primary analysis showed no significant overall difference between SG and RYGB in improving NAS, RYGB was associated with greater weight loss. Metaregression findings suggested that any potential histological advantage of RYGB may be largely attributable to its superior weight loss efficacy rather than to weight-independent mechanisms. Exploratory subgroup analyses suggested potential differences in long-term histological outcomes that varied across measures and should be considered hypothesis-generating. These findings warrant confirmation in future prospective studies.