
Between definitive resection and damage control observation: a case series analysis of intraoperative decision-making
Fengqi Ruan1, Yongen Liu2, Shuai Wang2
1Department of Emergency Surgery, Linyi People's Hospital, Linyi, Shandong, China.

Objective:
To investigate surgical decision-making in patients with portal venous gas (PVG) and acute abdomen, and to summarize the basis for choosing definitive resection vs. damage control observation according to intraoperative intestinal viability.
Methods:
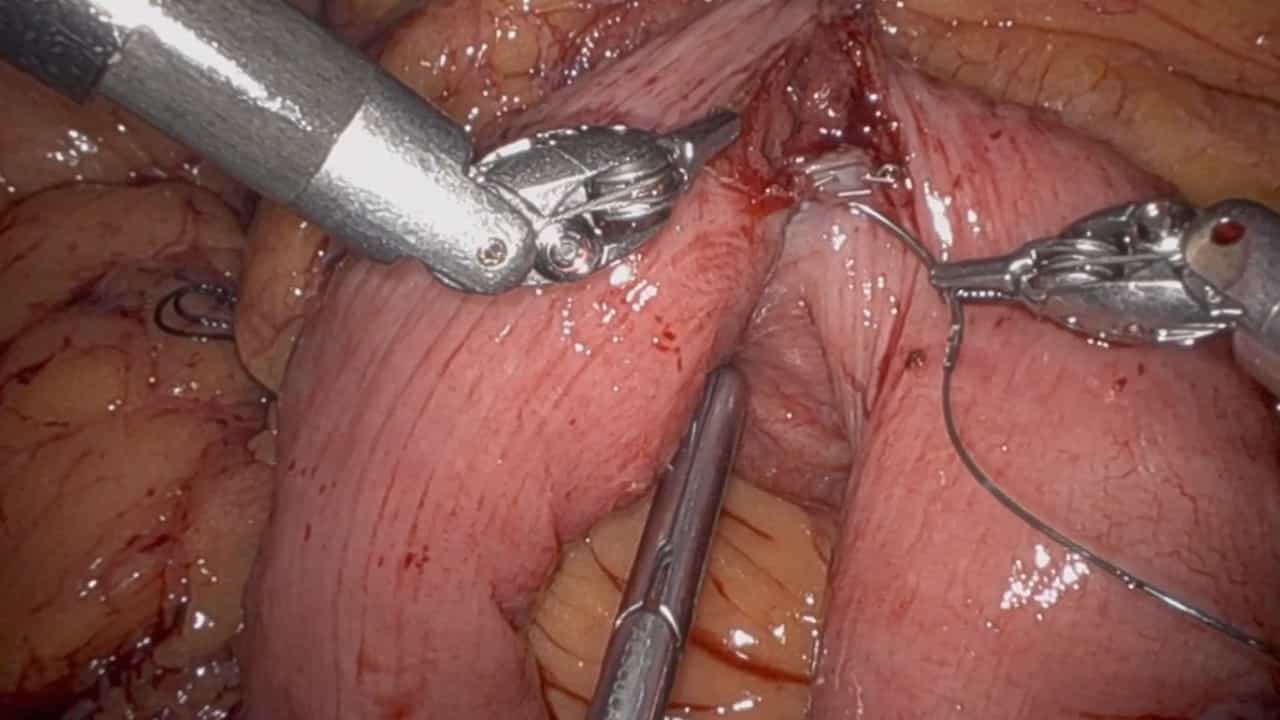
We retrospectively analyzed 4 patients with PVG and acute abdomen who underwent exploratory laparotomy at Linyi People's Hospital between April 2024 and December 2025. Based on intraoperative bowel color, peristalsis, and terminal mesenteric arterial pulsation, patients were classified into a definitive resection group (confirmed transmural necrosis, n = 2) or a damage control observation group (extensive ischemia without definite transmural necrosis, n = 2).
Results:
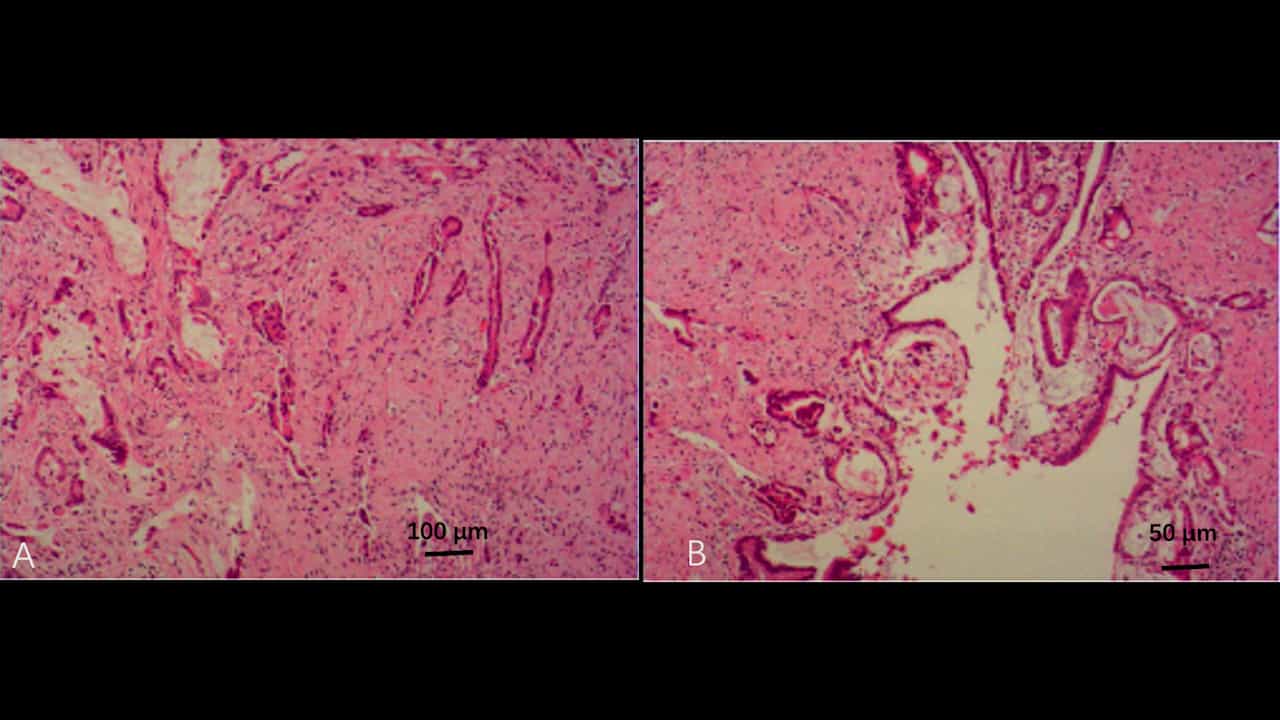
All patients presented with acute abdominal pain, and preoperative CT showed PVG with intestinal wall abnormalities or peritoneal effusion. In the definitive resection group, necrosis involved either 40 cm of jejunum or 70 cm of ileum and was treated by resection and anastomosis. Recovery was uneventful, with a mean hospital stay of 8 days. In the damage control observation group, long segments of ischemic small bowel without definite necrosis were preserved after exploration, peritoneal lavage, and drainage. These patients developed more pronounced postoperative inflammatory and coagulation abnormalities. One had a D-dimer level of 5.45 μg/mL (FEU), and another with end-stage liver disease required ICU admission and a 20-day stay. All patients survived to discharge.
Conclusion:
Based on this small case series, PVG may indicate serious intestinal pathology in acute abdomen and supports timely exploration. Intraoperative bowel viability assessment may guide resection or preservation of borderline ischemic bowel. These exploratory findings require confirmation in larger studies.