Related Experiment Video
Updated: Jul 10, 2026


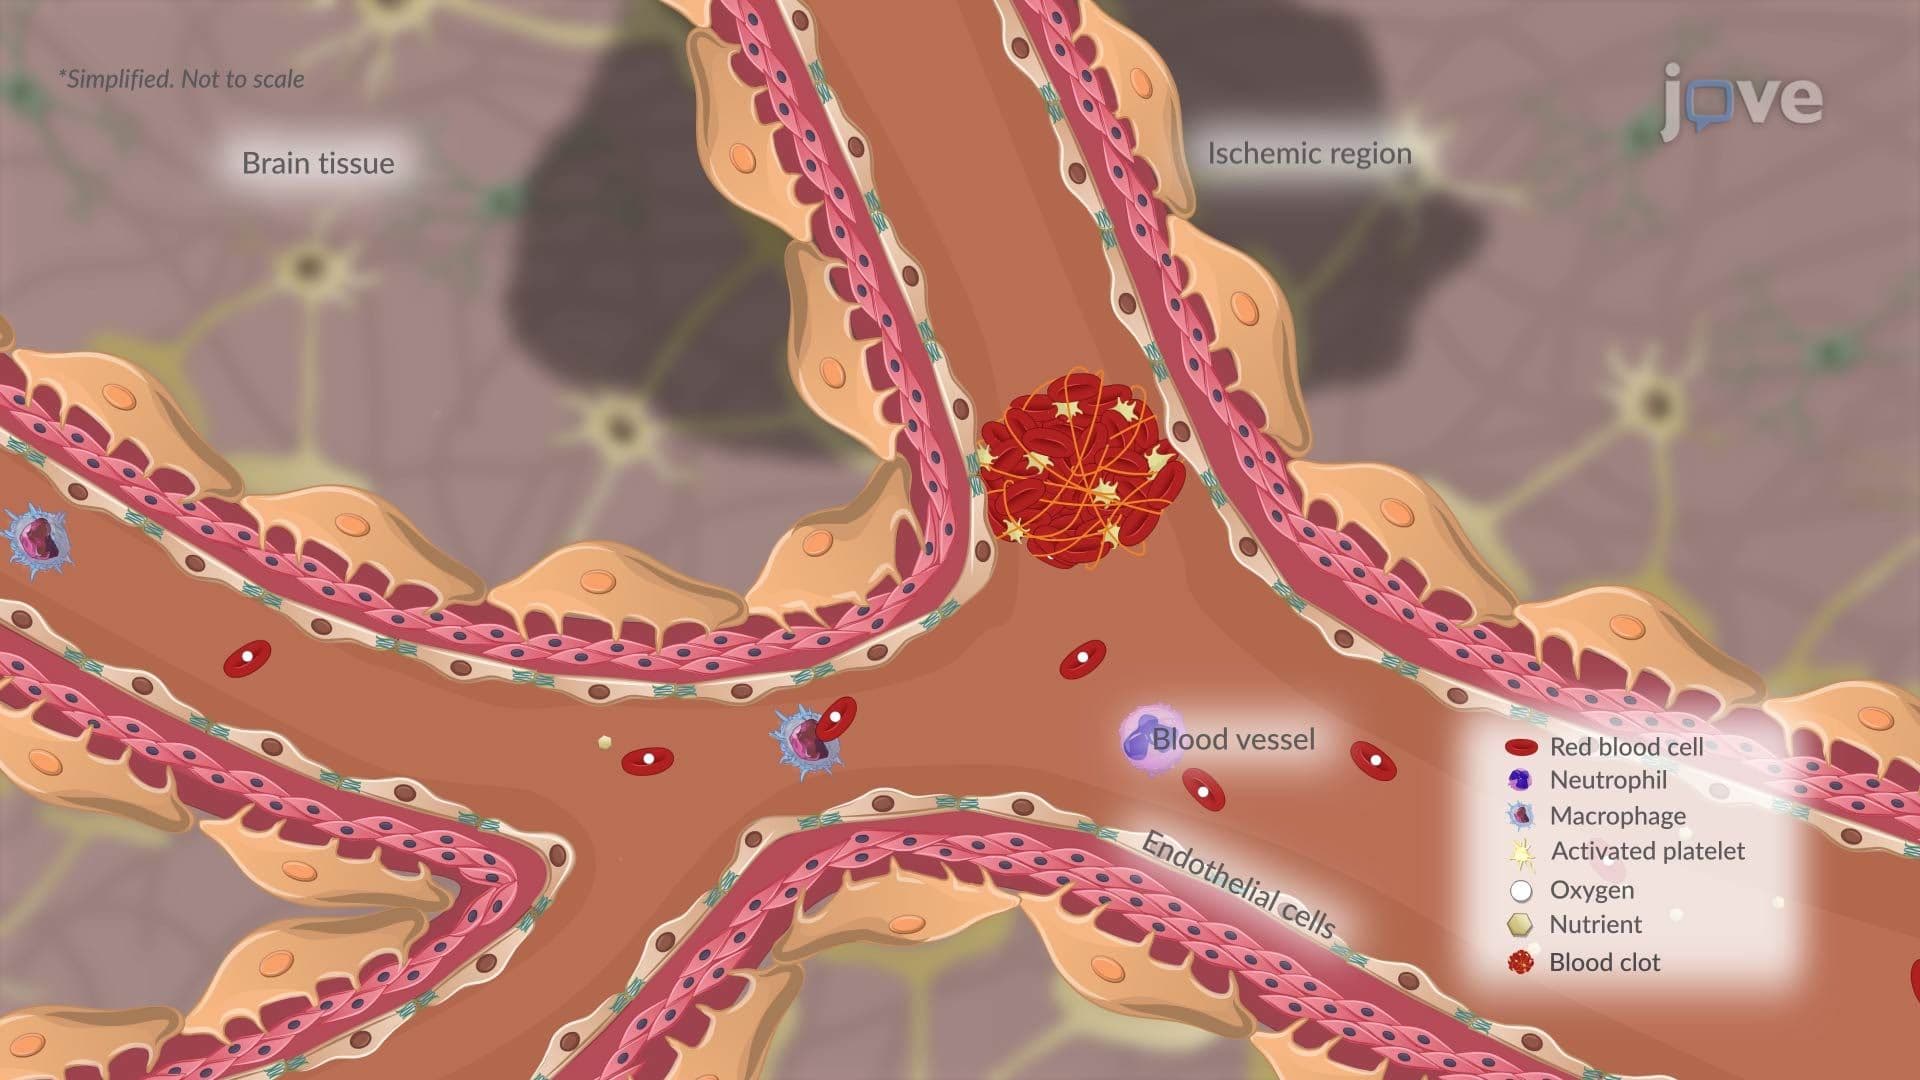
Circumscribed Capsular Infarct Modeling Using a Photothrombotic Technique
Published on: June 2, 2016
Case Report: Asymmetric recovery unmasking watershed infarction in a patient with ICU-acquired weakness
Bingqing Zhao1, Meng Yu2, Peining Zhou1
1Department of Respiratory and Critical Care Medicine, Peking University First Hospital, Beijing, China.

Background:
Intensive Care Unit-acquired weakness (ICUAW) typically manifests as generalized, symmetrical flaccid paralysis. However, atypical asymmetric patterns can occur when concurrent neurological complications are present, posing a significant diagnostic "double-masking" challenge in critically ill patients.
Case Presentation:
A 59-year-old female with severe pneumonia, septic shock, and complex endocrine comorbidities developed profound muscle weakness following survival from acute respiratory failure. Initially, the generalized weakness was attributed to ICUAW, supported by electrophysiological studies and a muscle biopsy. However, the patient exhibited distinct asymmetrical motor recovery, with persistent left-sided deficits despite a negative cranial computed tomography (CT). Subsequent cranial magnetic resonance imaging (MRI) revealed fresh watershed infarctions in the right hemisphere. A tailored rehabilitation strategy focusing on mitochondrial metabolism and active physical therapy led to significant functional improvement, with full recovery reported at a 2-year follow-up.
Conclusion:
This case highlights that the weaning process can act as a hemodynamic "stress test," unmasking latent cerebrovascular fragility in complex ICU patients. Clinicians should maintain a high index of suspicion for asymmetric recovery patterns in ICUAW. A multimodal approach is essential for accurate diagnosis and management.