Clinical outcomes after transition from weight-based to fixed-dose glucarpidase for high-dose methotrexate toxicity at a large academic medical center
Related Experiment Videos
Melissa L Bastacky1, Mario Martinez1, Shrina Duggal1
1Department of Pharmacy, UPMC Presbyterian-Shadyside Hospital, Pittsburgh, Pennsylvania, USA.

Abstract:
IntroductionDelayed methotrexate clearance can result in life-threatening toxicities including renal failure. Treatment includes vigorous hydration, urine alkalinization, leucovorin rescue, and glucarpidase. While traditional glucarpidase dosing is weight-based, its pharmacokinetic properties support possible use of non-weight-based dosing strategies. We evaluated clinical outcomes after transition from weight-based to fixed-dose glucarpidase for high-dose methotrexate (HDMTX) toxicity at a large academic medical center.MethodsAdult patients requiring inpatient glucarpidase for HDMTX-associated renal insufficiency between October 2014 and June 2025 were retrospectively reviewed. Patients receiving weight-based glucarpidase prior to implementation of a fixed 2000-unit dosing strategy were included for comparison. The primary objective was to compare time to renal recovery. Secondary outcomes were exploratory and included time to glucarpidase administration, peak serum creatinine (Scr) fold-change, dialysis requirement, and hospital length of stay (LOS).ResultsFourteen patients were included for analysis. Time to renal recovery was nearly identical between groups. The fixed-dose group received glucarpidase significantly sooner after HDMTX compared to the weight-based group (median 45.1 h vs. 71.5 h, p = 0.015) and had significantly lower max fold change in Scr (median 2.8-fold vs 3.8-fold, p = 0.034). The need for dialysis and median LOS trended towards fewer patients requiring dialysis (n = 0 vs n = 4, p = 0.070) and shorter LOS (19.1 days vs 39.3 days, p = 0.074) for the fixed-dose group.ConclusionsTransitioning from a weight-based to 2000-unit fixed-dose for glucarpidase at our institution resulted in sustained efficacy and safety. Further research is necessary to define optimal glucarpidase dosing.
Related Concept Videos
 01:27
Pharmacogenetics of Phase II Enzymes: N-acetyltransferase, Thiopurine S-methyltransferase, UDP-glucuronosyltransferase
 01:29
Therapeutic Drug Monitoring: Affecting Factors
 01:24
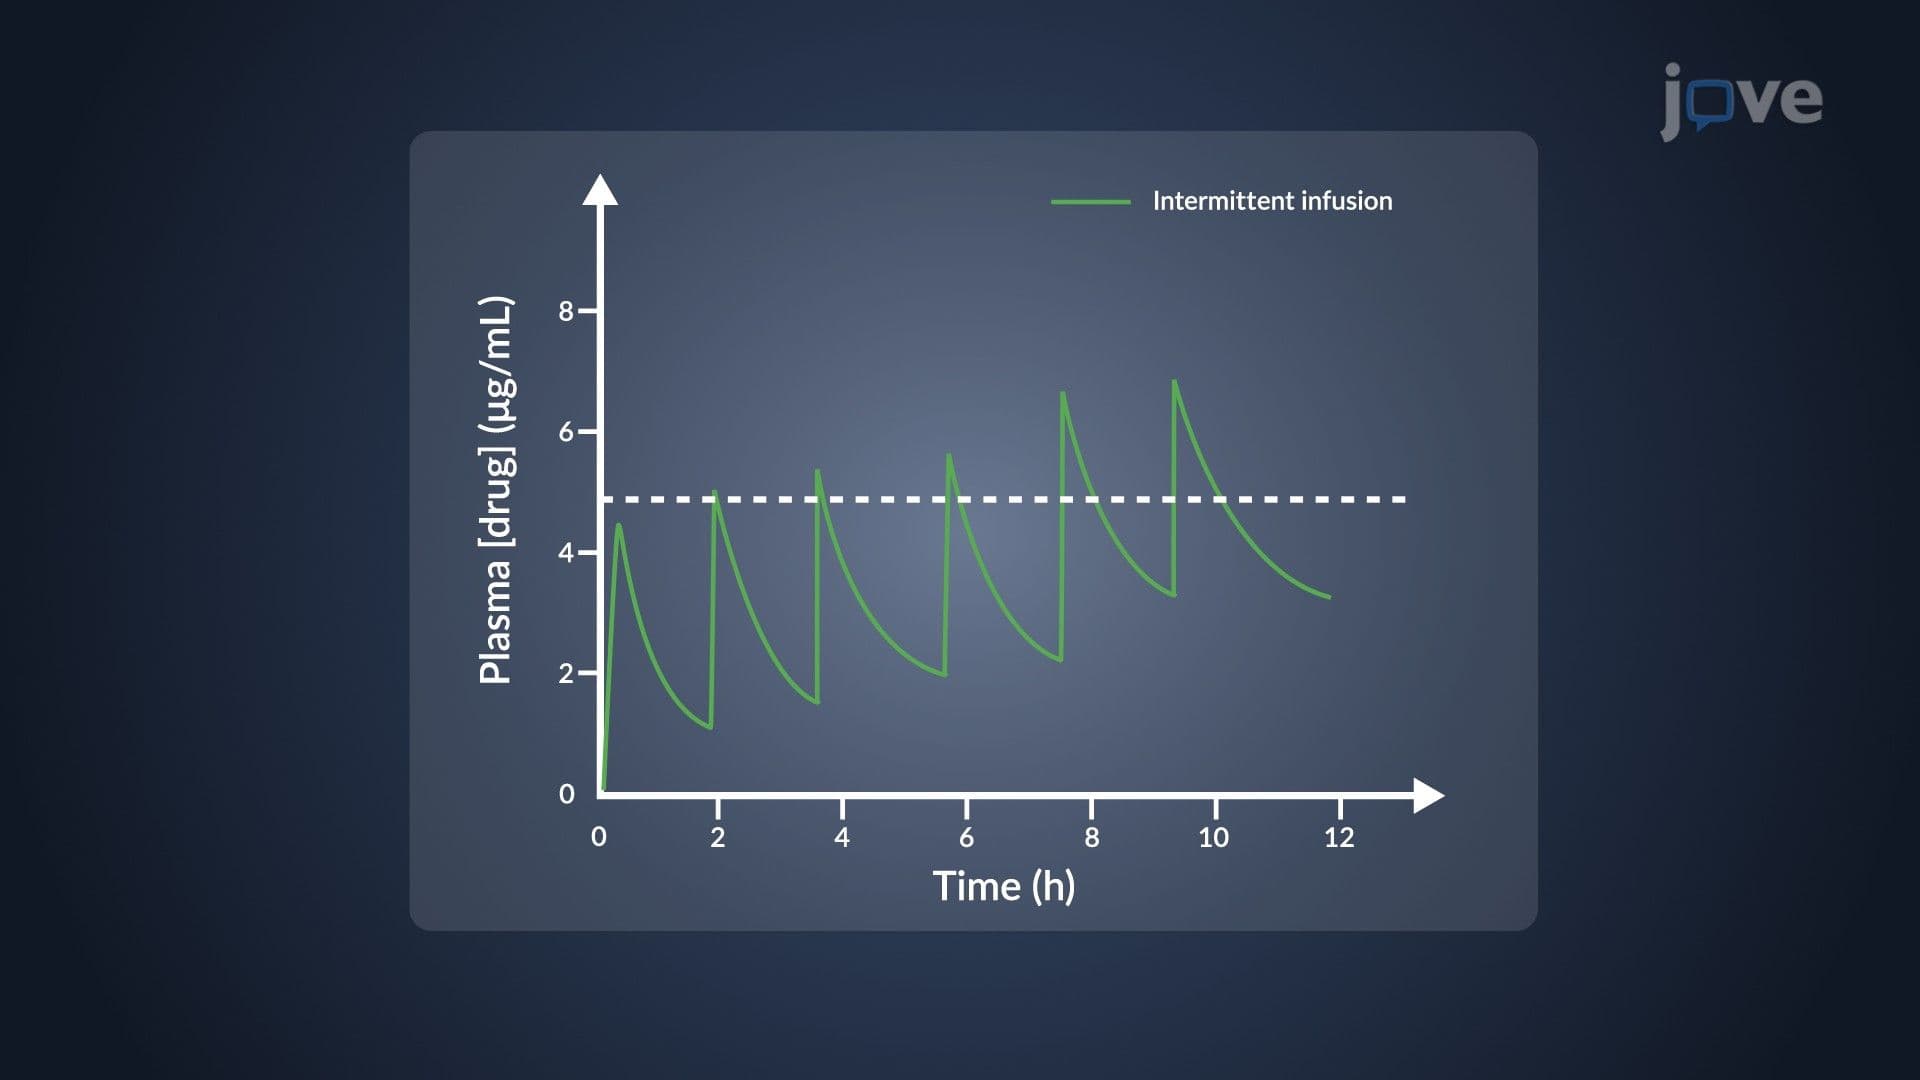
Drug Accumulation During Multiple Dosing: Intermittent IV Infusions
 01:21
Drug Dosing: Obese Patients
 01:11
Renal Failure: Dose Adjustments
Reduced renal clearance and elimination rate are common outcomes of renal impairment. These alterations lead to a prolonged elimination half-life and an altered apparent volume of distribution for drugs. As a result, dosage adjustments are typically necessary to maintain optimal drug levels in the body.
However, dosage adjustments...
 01:08
Effect of Hepatic Disease on Pharmacokinetics: Dose Adjustments Due to Hepatic Impairment