Related Experiment Video
Updated: Jul 10, 2026
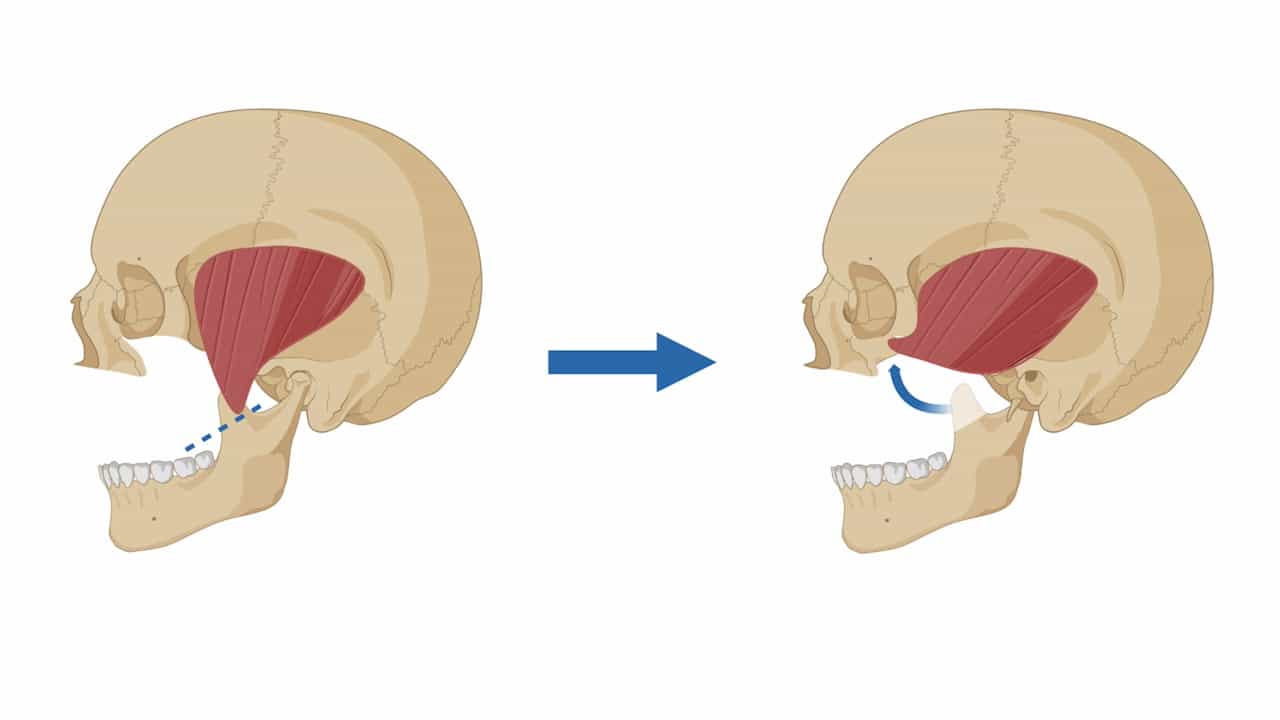

Coronoid-Temporalis Pedicled Flap for Orbital Floor Defect Reconstruction
Published on: December 5, 2025
Free Flap Versus Pedicled Flap for Oral Cavity Reconstruction: A Systematic Review and Meta-Analysis of Clinical
Ahmed Al Qattan1, Salah Al Din Al Azri1, Ali Al Mashaikhi1
1Oral and Maxillofacial National Unit, Al Nahdha Hospital, Muscat, Oman.

Background And Objectives:
Oral cavity reconstruction is typically carried out with free flap or pedicled flap techniques. Free flaps are regarded as the commonly accepted standard for surgical reconstruction; however, pedicled flaps remain a practical and valuable option in resource-limited settings, particularly with reliable options such as SCAIF, SMIF, and PMMF, and are especially suitable for patients with prior radiation, significant comorbidities, advanced age, or when microvascular reconstruction is not feasible. The objective of this systematic review and meta-analysis was to compare clinical outcomes and complication rates between free and pedicled flap reconstructions.
Methods:
Searches of PubMed and Google Scholar were performed up to the latest study identifying observational studies that reported clinical effects and complications of free flap and pedicled flap in patients undergoing oral reconstruction. Data were extracted using a predesigned data collection form. Meta-analysis was conducted using RevMan Web version 7.13.0 to compare clinical outcomes and complications between the 2 surgical reconstruction techniques. Analysis was represented as mean difference (MD) and odds ratio (OR) for continuous and categorical outcomes, respectively, with 95% CI. P<0.05 was considered significant.
Results:
Nine observational studies met the inclusion criteria. Patients who underwent free flap reconstruction had a significantly longer duration of hospital stay as compared with patients with pedicled flap repair (MD: 4.21; 95% CI: 1.52, 6.89; P=0.002). No statistically significant difference in surgery time was seen between both techniques (MD: 84.29; 95% CI: -37.18, 205.77; P=0.17). Patients with free flap reconstruction had a comparatively lower risk of dehiscence (OR: 0.39; 95% CI: -0.20, 0.78; P=0.007) but a higher risk of overall complications compared with patients with pedicled flaps (OR: 2.13; 95% CI: 1.04, 4.36; P=0.04). There were no statistically significant differences between free and pedicled flaps in terms of dehiscence in the donor (OR: 0.29; 95% CI: 0.04, 2.23; P=0.23), infection rates (OR: 1.24; 95% CI: 0.61, 2.52; P=0.56), or fistula formation (OR: 0.79; 95% CI: 0.23, 2.65; P=0.70), although the rates were numerically higher in the pedicled flap group.
Conclusions:
Free flap reconstruction was associated with longer hospital stay, lower risk of dehiscence, and higher complications in donors, while pedicled flaps showed comparable outcomes for infection and fistula. Both techniques showed acceptable outcomes in this systematic review and meta-analysis, highlighting the importance of selecting the reconstruction technique based on patient needs and available resources.