Related Experiment Video
Updated: Jul 12, 2026
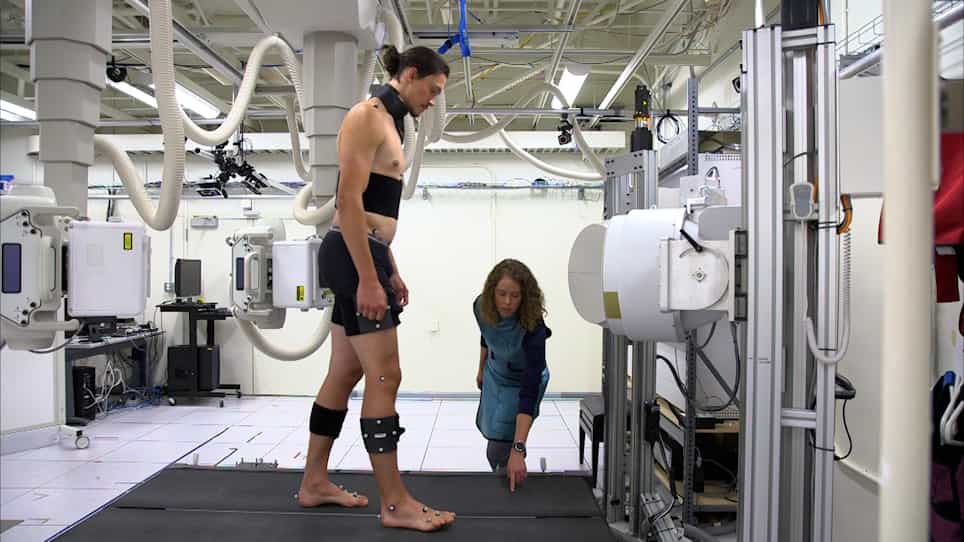

In Vivo Quantification of Hip Arthrokinematics during Dynamic Weight-bearing Activities using Dual Fluoroscopy
Published on: July 2, 2021
Although patients with femoroacetabular impingement demonstrate abnormal kinematics during single-leg squat, their
Yuang Hao1, Yao Pan1, Jinwoo Kim2
1Department of Sports Medicine, Peking University Third Hospital, Institute of Sports Medicine of Peking University, Beijing, China; Beijing Key Laboratory of Research and Translation for Drugs and Medical Devices in Precision Diagnosis and Treatment of Sports Injuries, Beijing, China; Engineering Research Center of Sports Trauma Treatment Technology and Devices, Ministry of Education, Beijing, China.

Introduction:
Patients with femoroacetabular impingement syndrome may exhibit altered hip and ankle kinematics during single-leg squat, but whether hip flexion-adduction coordination variability is affected remains unclear. This study aimed to compare hip and ankle kinematics and hip coordination angle variability between patients with FAIS and healthy controls during single-leg squat.
Methods:
20 patients diagnosed with femoroacetabular impingement syndrome (FAIS) and 20 gender-matched healthy controls were recruited prior to surgical intervention. The single-leg squat (SLS) test was conducted using a motion capture system. We measured hip and ankle joint angles at knee flexion angles of 30° and 60°, along with hip flexion - adduction coordination angle variability throughout the squat cycle. Additionally, we assessed isometric strength of hip flexors, extensors, adductors, abductors, and internal and external rotators.
Results:
During the single-leg squat, the FAIS group exhibited a statistically significantly greater hip adduction angle than the healthy control. At 60° knee flexion, hip adduction angle was statistically significantly higher in the FAIS group during both descent (p = 0.039, np2 = 0.11) and ascent (p = 0.035, np2 = 0.12). At 30° knee flexion, hip adduction angle was also statistically significantly higher in the FAIS group during descent (p = 0.002, np2 = 0.24) and ascent (p = 0.004, np2 = 0.20). Ankle dorsiflexion angle was statistically significantly lower in the FAIS group. Specifically, at 60° knee flexion, dorsiflexion angle was statistically significantly lower during descent (p = 0.002, np2 = 0.23) and ascent (p < 0.001, np2 = 0.27). At 30° knee flexion, dorsiflexion angle was also statistically significantly lower during descent (p = 0.002, np2 = 0.23) and ascent (p = 0.001, np2 = 0.25). Secondary analyses showed that hip adduction was statistically significantly negatively associated with hip extensor strength at 60° knee flexion during both the descending phase (r = -0.57, p = 0.009) and ascending phase (r = -0.58, p = 0.007). Finally, hip flexion-adduction coordination angle variability (CAV) did not differ between groups (p = 0.72, np2 = 0.003).
Conclusion:
Patients with FAIS exhibit altered hip and ankle kinematics during the single-leg squat. The hip adduction angle at 60° knee flexion during the SLS was associated with hip extensor strength, whereas hip adduction-flexion coordination angle variability remained largely unchanged.
Level Of Evidence:
Level Ⅲ, case control.

