Related Experiment Video
Updated: Jul 12, 2026
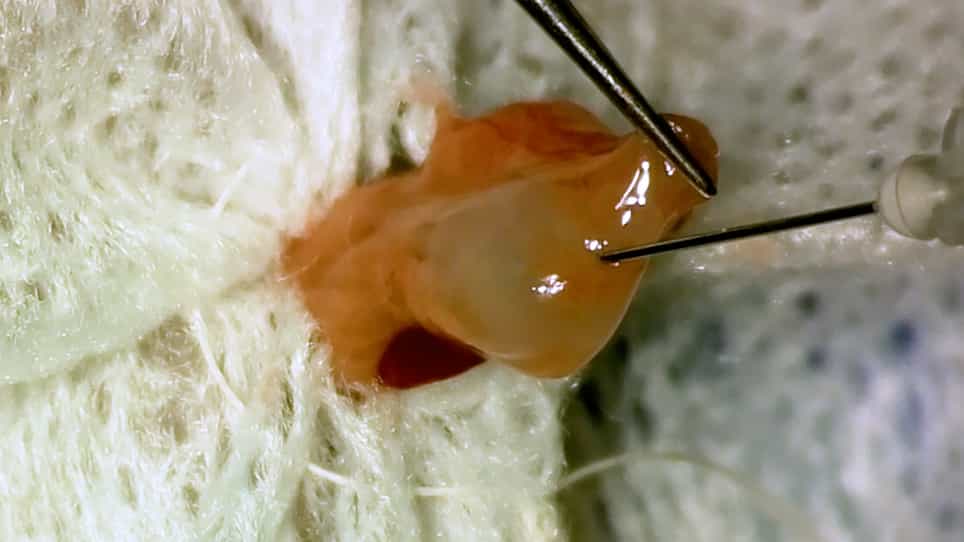
An Orthotopic Resectional Mouse Model of Pancreatic Cancer
Published on: September 24, 2020
Cost-effectiveness of first-line treatments for metastatic pancreatic cancer
Ying Dong1, Yiqing Yin1, Guiyue Wang1
1Department of Anesthesiology, Department of Cancer Neuroscience, Tianjin Medical University Cancer Institute and Hospital, National Clinical Research Center for Cancer, Tianjin Key Laboratory of Digestive Cancer, Tianjin's Clinical Research Center for Cancer, Tianjin, 300060, China.

Background:
The NAPOLI-3 trial demonstrated that NALIRIFOX significantly improves overall survival (OS) and progression-free survival (PFS) compared with nab-paclitaxel plus gemcitabine (GEM-NAB-PAC), while the PRODIGE4-ACCORD11 trial showed a survival benefit of FOLFIRINOX over gemcitabine in patients with metastatic pancreatic cancer. Notably, these trials enrolled previously untreated patients, establishing NALIRIFOX, GEM-NAB-PAC, and FOLFIRINOX as first-line treatment options. Given the high costs and toxicity associated with these regimens, an economic evaluation is needed to inform treatment selection. Therefore, this study evaluated the cost-effectiveness of first-line NALIRIFOX, GEM-NAB-PAC, and FOLFIRINOX compared with gemcitabine in patients with metastatic pancreatic adenocarcinoma from a U.S. healthcare payer perspective.
Methods:
A three-state partitioned survival model was developed with a lifetime horizon and a 1-week cycle length. Clinical efficacy data were derived from the NAPOLI-3 and PRODIGE4-ACCORD11 trials. Costs, health state utilities, and adverse event disutilities were obtained from published literature and public databases. Costs and outcomes were discounted at an annual rate of 3%. Total costs, quality-adjusted life-years (QALYs), and incremental cost-effectiveness ratios (ICERs) were estimated. A willingness-to-pay (WTP) threshold of US$150,000 per QALY was applied. Deterministic and probabilistic sensitivity analyses were conducted to assess model robustness.
Results:
Model-predicted median PFS and OS closely matched trial-reported outcomes, supporting good internal validity. In the base-case analysis, using gemcitabine as the reference comparator, FOLFIRINOX demonstrated the most favorable cost-effectiveness, with an ICER of US$6,864 per QALY gained. NALIRIFOX yielded the largest QALY gain and had an ICER of US$114,614 per QALY, whereas GEM-NAB-PAC was associated with the highest ICER (US$231,750 per QALY). At the WTP threshold of US$150,000 per QALY, FOLFIRINOX and NALIRIFOX were considered cost-effective compared with gemcitabine, while GEM-NAB-PAC was not.
Conclusions:
From a U.S. healthcare payer perspective, FOLFIRINOX represents the most cost-effective first-line treatment for metastatic pancreatic cancer, while NALIRIFOX may be considered a cost-effective alternative at commonly accepted WTP thresholds. GEM-NAB-PAC was not cost-effective under the base-case assumptions.


