Related Experiment Video
Updated: Jul 12, 2026
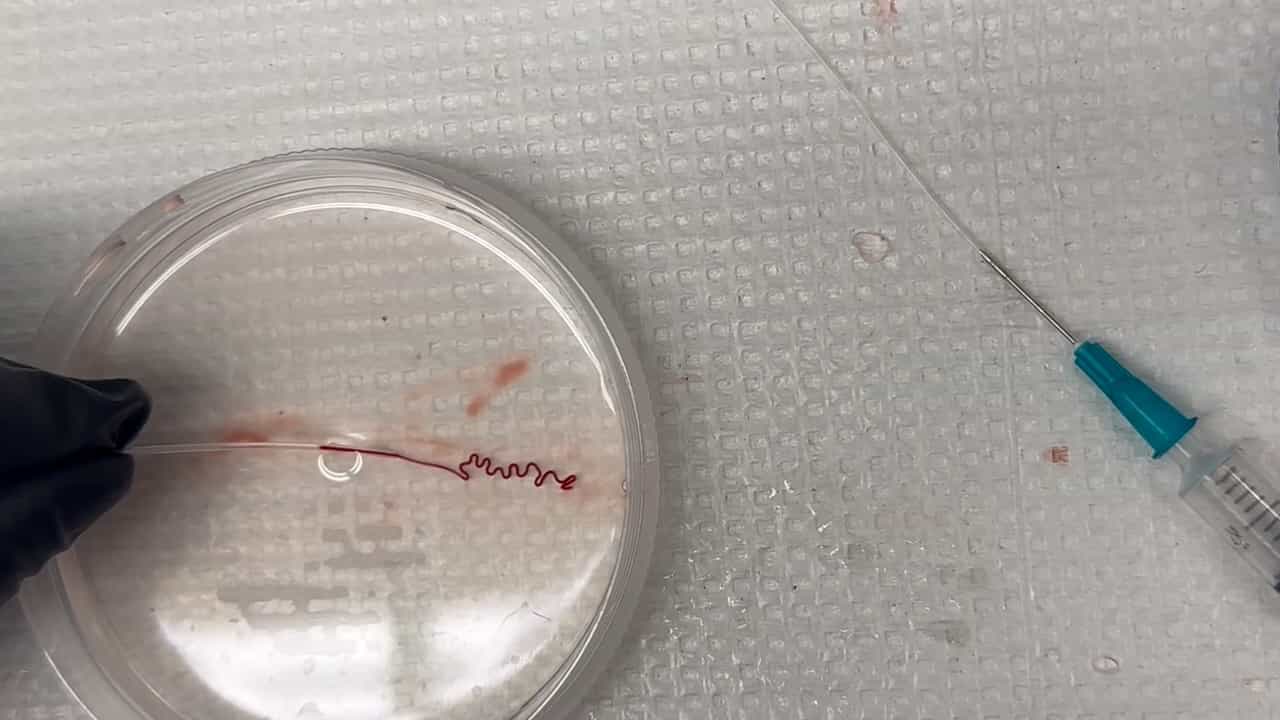

The Stroke Preclinical Assessment Network Multi-Laboratory Model of Thromboembolic Stroke with Thrombolysis: TE-MCAo
Published on: December 19, 2025
Real-World Practice in Secondary Stroke Prevention Following Embolic Stroke of Undetermined Source: Secondary
Hassan Aboul-Nour1,2,3, James Ernest Siegler4,5, Sean L Thompson1,2
1Department of Neurology, Emory University, Atlanta, GA.

Background And Objectives:
Multiple clinical trials have failed to show benefit of anticoagulation over antiplatelets in preventing recurrent stroke among patients with embolic stroke of undetermined source (ESUS). However, there are limited data on antithrombotic prescribing patterns and clinical outcomes in a real-world setting.
Methods:
This is a subgroup analysis of a multicenter retrospective observational cohort of consecutive adults with ESUS (admitted between 2015 and 2023). Patients were categorized according to antithrombotic initiation by day 7 after stroke or discharge, whichever was sooner: single antiplatelet therapy (SAPT), combination antiplatelet therapy (CAPT) without anticoagulation (AC), or AC with or without antiplatelet therapy (AP) initiated within the first 7 days of index stroke. Differences in treatment strategies were compared between patients admitted between 2015-2018 and 2019-2023 approximating the publication of RESPECT ESUS and NAVIGATE ESUS trials. The primary composite outcome of recurrent ischemic stroke, major bleeding, intracerebral hemorrhage, or death was assessed using unadjusted and adjusted Cox proportional hazards regression.
Results:
Of the 2,328 included patients, 1,537 (66.0%) were prescribed SAPT, 561 (24.1%) CAPT, and 230 (9.9%) AC ± AP. Compared with other treatment groups, patients treated with CAPT were less likely to be female, but more likely to have atherosclerotic risk factors and presented with milder symptoms. Patients treated with AC ± AP were younger, more likely to have a prior stroke, a higher NIHSS, a large vessel occlusion, and reduced left ventricular ejection fraction. Compared with patients admitted from 2015 to 2018, those admitted between 2019 and 2023 were more frequently prescribed AC ± AP (11.3% vs 5.9%) or CAPT (26.7% vs 17.2%) and less frequently prescribed SAPT (62.0% vs 76.9%, p < 0.001). Compared with SAPT, neither CAPT nor AC were associated with any significant difference in the primary composite outcome. Of the secondary outcomes, CAPT was associated with lower risk of death vs SAPT in unadjusted and adjusted models (aHR 0.69, 95%CI, 0.48-0.98).
Discussion:
In this large multicenter cohort study, there was an increased frequency of discharge on AC in ESUS patients after the publication of ESUS randomized trials. Treatment with CAPT or AC ± AP was not associated with a reduced risk of recurrent stroke compared with SAPT.
Trial Registration Information:
The study is registered on ClinicalTrials.gov (NCT06398366).
