Related Experiment Video
Updated: Jul 12, 2026
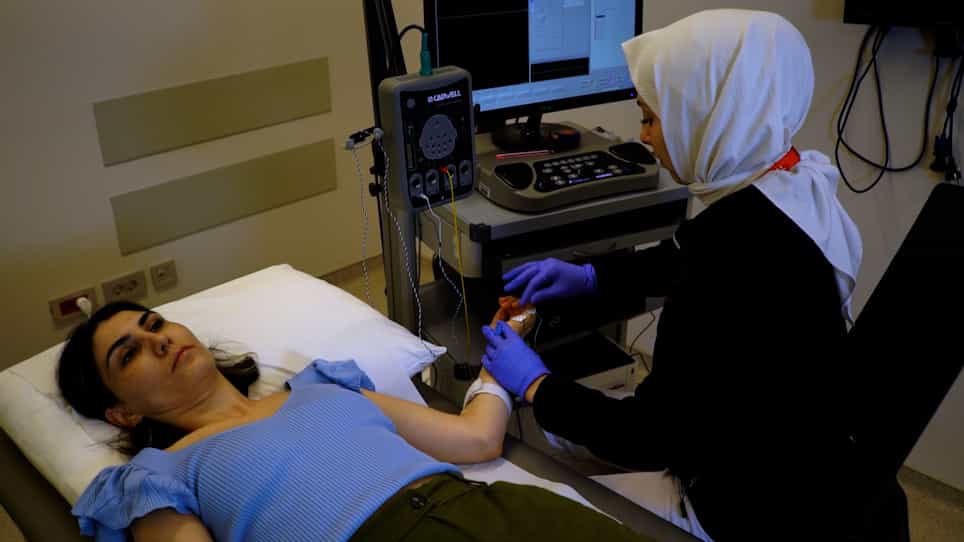

Transaxillary First Rib Resection for Treatment of the Thoracic Outlet Syndrome
Published on: September 13, 2020
Early and Emergency Department Management of Infraclavicular Brachial Plexus Injuries Secondary to Shoulder Trauma
Praveen Baskaran1, Abigail S Bower2, Ashley I Simpson3
1Trauma and Orthopaedics, Barnsley Hospital NHS Foundation Trust, South Yorkshire, GBR.

Abstract:
Infraclavicular brachial plexus injury is an uncommon but potentially disabling complication of shoulder trauma, particularly glenohumeral dislocation and proximal humerus fracture or fracture-dislocation. Reported frequencies of neurological deficit vary widely because of heterogeneous definitions and ascertainment methods. Systematic reviews consistently identify the axillary nerve as the most commonly affected nerve following dislocation; however, multi-nerve deficits indicating cord-level involvement are clinically significant because recovery may be delayed or incomplete. Emergency care priorities for suspected infraclavicular brachial plexus injury centre on early, repeated, and well-documented neurological examination mapped to named cords and terminal branches, alongside prompt, gentle reduction of dislocations when a nerve deficit is present. Analgesia that facilitates examination without obscuring baseline deficits and imaging should be tailored to the fracture pattern and assessment of associated vascular red flags. Time-sensitive referral to orthopaedic and specialist peripheral nerve services is essential when red flags are identified. Concurrent vascular injury is a critical red flag that must be recognised early and escalated because it may compound nerve injury through compression or ischaemia and is itself limb-threatening. UK BOASt (British Orthopaedic Association Standards for Trauma) standards emphasise documentation of nerve function at the earliest opportunity and following interventions, alongside efficient referral pathways. This article is a narrative review with a pragmatic emergency department pathway proposal. It synthesises systematic reviews, large observational studies, and UK national standards. The proposed pathway is an expert-opinion synthesis that incorporates checklist-based documentation, staged imaging, and clear thresholds for escalation and specialist referral. It is intended for local adaptation and audit and has not been prospectively validated. The aim is to reduce missed injuries, optimise time-sensitive reconstructive opportunities, and mitigate medicolegal risk.

Related Concept Videos
 01:26
Flail Chest-II
Assessment:
1. Clinical Evaluation:
History:
 01:22
Spinal Nerves: Plexus I
The Cervical Plexus
The cervical plexus, formed by the anterior rami of the first four...
 01:23
Muscles of the Shoulder
Anterior Thoracic Muscles
The anterior thoracic muscles include the serratus anterior, subclavius, and...
 01:12
Arteries of the Upper Limbs
 01:25
Pericarditis IV: Nursing Management
 01:25
Cardiopulmonary Resuscitation IV: Pharmacological Management