Related Experiment Video
Updated: Jul 14, 2026
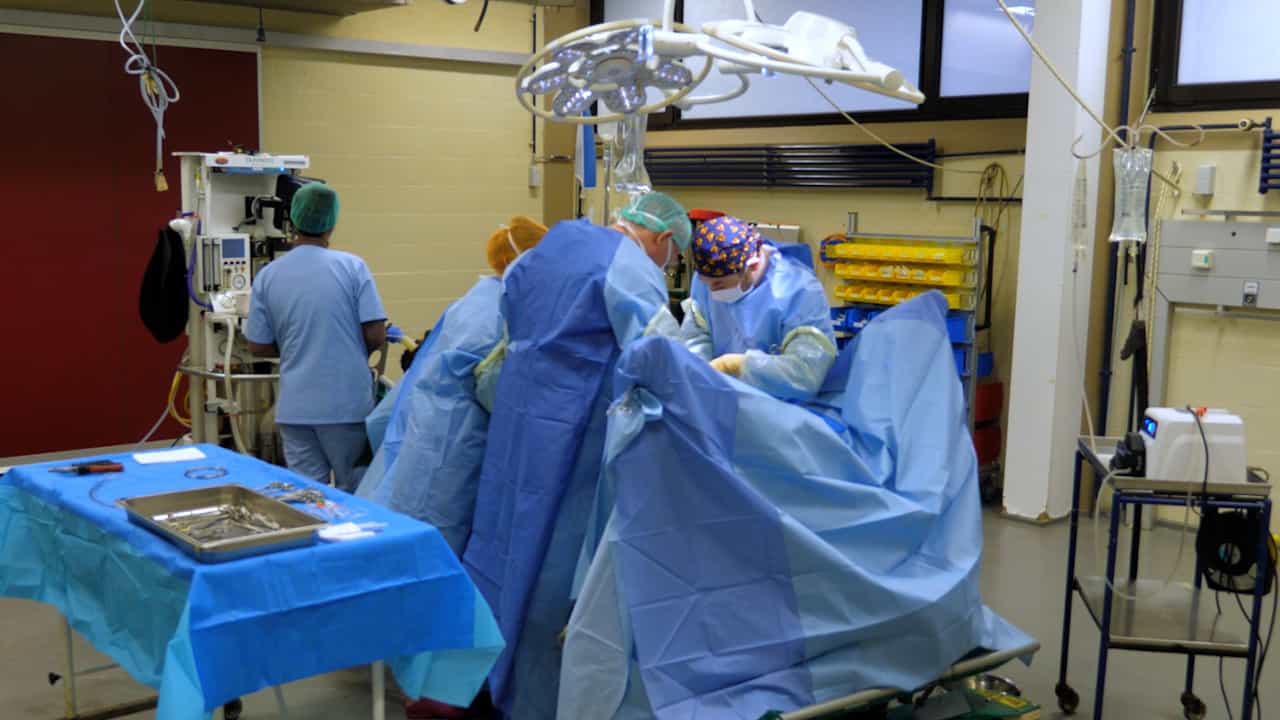

Surgical Closure of Equine Abdomen, Prevention, and Management of Incisional Complications
Published on: May 10, 2024
Negative-pressure wound therapy for perineal wound complications after abdominoperineal resection/extralevator APR:
1Department of Obstetrics and Gynecology, Zhejiang Hospital, No. 1229, Gudun Road, Sandun Town, Xihu District, Hangzhou City, 310030, Zhejiang Province, China.

Background:
Closed‑incision negative-pressure wound therapy (ciNPT), or incisional negative-pressure wound therapy (NPWT), has been used prophylactically to reduce perineal wound morbidity after oncologic abdominoperineal resection (APR) and extralevator abdominoperineal excision (ELAPE). However, published evidence is heterogeneous and includes prophylactic incisional use as well as therapeutic/intracavitary applications. We conducted a systematic review and meta‑analysis of NPWT strategies for perineal wound outcomes following oncologic APR/ELAPE.
Methods:
A systematic search was executed across PubMed, Scopus, Web of Science, and the Cochrane Library from inception to July 2025, including studies that evaluated the role of NPWT in postoperative perineal wounds after oncologic APR/ELAPE. We included both prophylactic closed-incision NPWT (ciNPT) after primary closure and therapeutic NPWT for open/infected perineal wounds; quantitative pooling was limited to comparable comparative studies. The outcomes of interest were the perineal wound complications and infection, surgical revision, and hospital stay. Data were synthesized through a DerSimonian-Laird random effect meta-analysis model, with risk ratios (RR) or mean differences with their 95% confidence interval (CI), pooling the dichotomous or continuous outcomes, respectively.
Results:
Our review included eight studies with three comparative studies pooled with a total of 270 patients. Although the raw incidence of perineal wound complications was lower in the NPWT group relative to the control group (36.5% versus 53.6%), the pooled analysis revealed no statistical significance (RR = 0.79, 95% CI [0.42-1.48], p = 0.46). Similarly, no significant differences between the two groups were observed in terms of perineal wound infection (p = 0.35), surgery revision (p = 0.53), and hospital stay (p = 0.77).
Conclusions:
This meta-analysis demonstrated no significant clinical benefit for NPWT in managing postoperative perineal wound after oncologic APR/ELAPE. Further randomized controlled trials with standardized protocols are needed to clarify the role of NPWT in this area.