Related Experiment Video
Updated: Jul 15, 2026

Focused Assessment with Sonography for Trauma (FAST) Exam: Image Acquisition
Published on: September 22, 2023
Risk factors for mis-triage between medical and surgical causes in emergency patients with non-traumatic abdominal
Jinlong Zheng1, Yang Liu1, Wen Chen1
1Department of Emergency, Xiangyang Central Hospital, Affiliated Hospital of Hubei University of Arts and Science, Xiangyang, China.

Objective:
To analyze the current status of mis-triage between medical and surgical causes in emergency patients with non-traumatic abdominal pain, explore its influencing factors, and provide evidence-based support for optimizing emergency triage processes and improving triage accuracy.
Design:
This was a retrospective case-control study using data from the hospital information system and is reported in accordance with the STROBE guidelines.
Methods:
A retrospective case-control study was conducted. Clinical data were obtained from electronic medical records of non-traumatic abdominal pain patients who presented to the emergency department of a tertiary hospital between January 2024 and December 2025. Based on consistency between the final diagnosis and the initial triage direction (medical vs. surgical), patients were assigned to either a correctly triaged group or a mis-triage group (including medical diseases misdirected to surgery and surgical diseases misdirected to medicine). Multivariate logistic regression was performed to identify factors independently associated with mis-triage.
Results:
A total of 13,416 patients with non-traumatic abdominal pain were included, among whom 1,076 cases (8.02%) experienced mis-triage between medical and surgical causes. Of these, 58.10% were surgical diseases misdirected to medicine, and 41.90% were medical diseases misdirected to surgery. Multivariate logistic regression identified the following factors independently associated with mis-triage: number of accompanying symptoms (OR = 1.224, 95%CI: 1.094-1.370), pain score (OR = 0.783, 95%CI: 0.741-0.828), working years of triage nurse (OR = 0.960, 95%CI: 0.944-0.977), mode of arrival (OR = 0.959, 95%CI: 0.942-0.975), male sex (OR = 1.140, 95%CI: 1.005-1.293), and walking (OR = 1.757, 95% CI: 1.301-2.371) (all P < 0.05).
Conclusion:
A certain proportion of mis-triage occurs in emergency patients with non-traumatic abdominal pain, with surgical diseases being more frequently misdirected to medicine. A higher number of accompanying symptoms, lower pain score, triage by less experienced nurses, and presence of fever are major risk factors for triage error. It is recommended to strengthen specialized training for emergency triage nurses, develop triage support tools integrating typical symptoms with point-of-care testing, and enhance dynamic assessment for older adults with more accompanying symptoms, in order to reduce mis-triage rates and ensure patient safety.
Related Concept Videos
 01:22
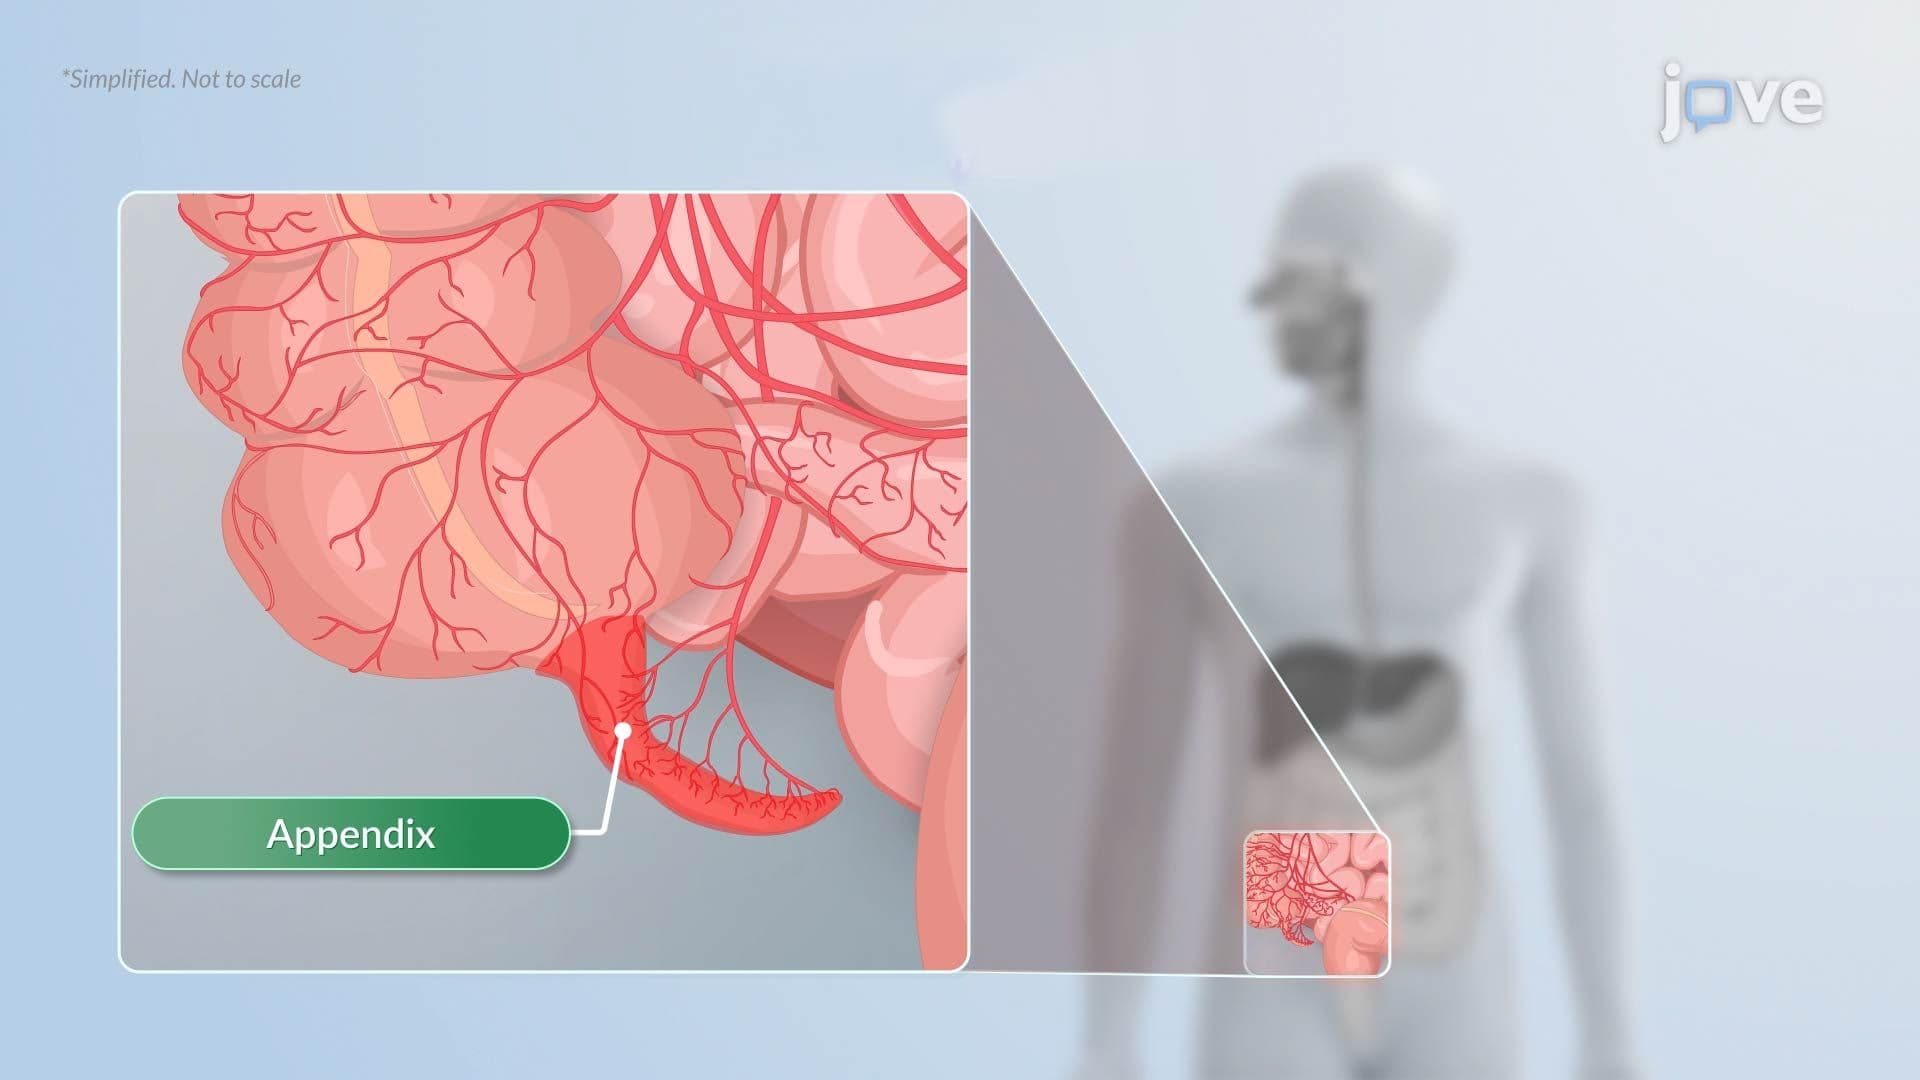
Appendicitis-I: Introduction
Etiology: Appendicitis can arise from various causes, primarily rooted in the obstruction of the appendix lumen. Factors contributing to this obstruction include fecal accumulation, lymphoid hyperplasia and, in...
 01:21
Aneurysm II: Clinical Manifestations and Diagnostic Studies
 01:29
Appendicitis-II: Diagnostic Studies and Management
Diagnosing Appendicitis
It requires a multifaceted approach, starting with a detailed physical examination to pinpoint the location and nature of the pain and identify any associated symptoms. Laboratory tests play a crucial role. A complete Blood Count (CBC) typically reveals leukocytosis (an increased number of...
 01:30
Acute Pancreatitis II: Clinical Manifestations and Management
 01:20
Cholecystitis
 01:19
Appendicitis