Related Experiment Video
Updated: Jul 15, 2026


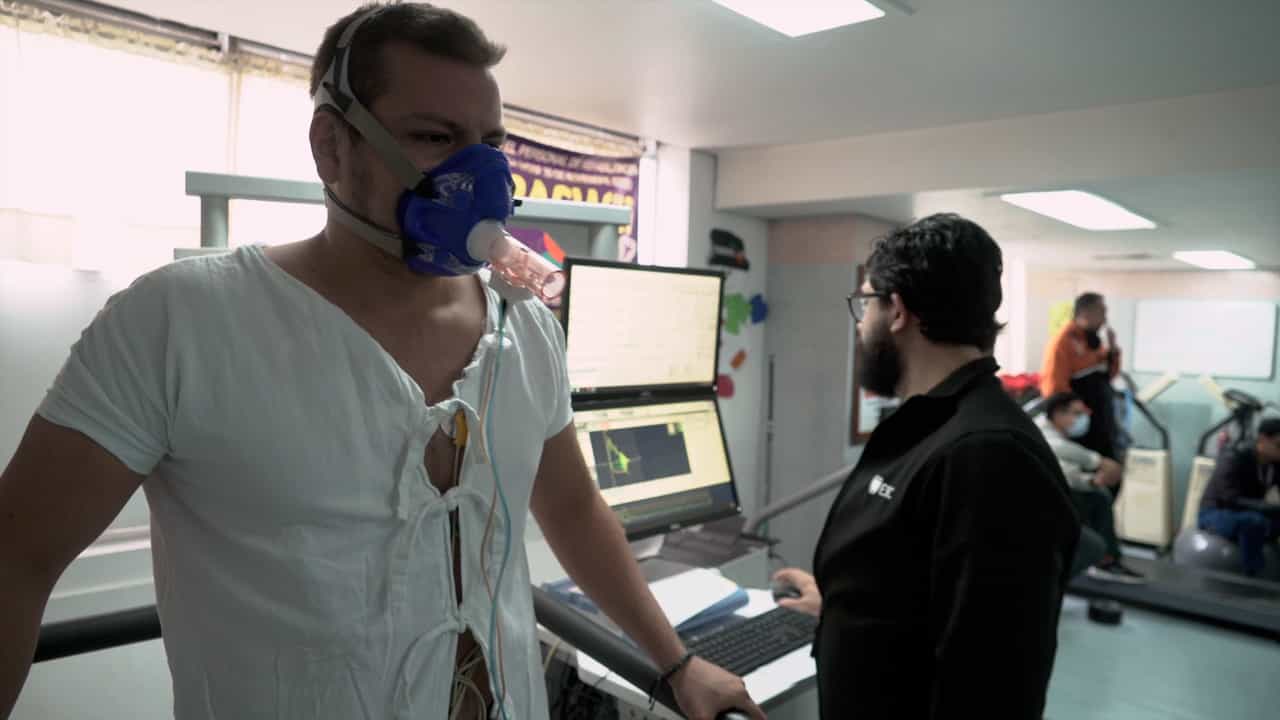
A Novel Digital Platform for a Monitored Home-based Cardiac Rehabilitation Program
Published on: April 19, 2019
Generating evidence using electronic alerts during routine care: a fully automated randomized controlled trial of
Yang Chen1,2, Daniel Higgins3, Yogini Jani3,4
1Institute of Health Informatics, Faculty of Population Health Sciences, University College London, Gower Street, London WC1E 6BT, UK.

Aims:
Many medical treatments lack robust evidence of safety and effectiveness from randomized controlled trials (RCTs). This is partly due to the cost and complexity of performing traditional RCTs and because randomization is not routinely embedded in clinical care. We aimed to evaluate the feasibility of conducting a pragmatic RCT fully integrated into the electronic health record (EHR) system to streamline patient identification, randomization, treatment allocation, and outcome assessment in patients admitted with acute heart failure.
Methods And Results:
THIRST Alert was a single-centre parallel-group, open-label, feasibility RCT embedded in a hospital EHR system from May 3 to 1 November 2023. Adult patients who received more than one dose of intravenous furosemide within 48 h of admission were eligible. An interruptive alert was triggered when physicians accessed the medication order chart of eligible patients, inviting them to enrol the patient in the study. Enrolled patients were randomized to either 'oral fluid restriction of 1 L per day' or 'no fluid restriction'. The co-primary feasibility outcomes were the total number of patients recruited and the documented difference in oral fluid intake within 48 h of randomization. Twenty-three patients (16%) were enrolled from 145 eligible patient admissions; there were no repeat admissions among enrolled patients. A total of 1191 enrolment alerts were triggered, reaching 216 individual clinicians. 22/23 trial participants (96%) had a diagnosis of heart failure. No significant difference in oral fluid intake was observed between the treatment groups (median difference 518 mL; 95% confidence interval: -235 to 1270; P = 0.18). Documented oral intake was numerically higher in the oral fluid restriction group (1168 mL; interquartile range [IQR] 932-1620 mL) compared to the group without restriction (650 mL; IQR 75-1102 mL), which may reflect documentation bias rather than a true increase in oral fluid intake or a lack of intervention efficacy.
Conclusion:
This study demonstrates the feasibility of a pragmatic RCT fully integrated within a hospital EHR system in acute care. Although alert-to-enrolment rate was modest, the overall recruitment rate was comparable to conventional acute care RCTs, highlighting the potential of EHR-embedded trials to efficiently address evidence gaps in the management of conditions such as acute heart failure.
Clinicaltrialsgov:
NCT05869656.
Related Concept Videos
 01:22
Heart Failure VI: Adjunct Therapies
 01:30
Heart Failure VII: Nursing Interventions
 01:30
Acute Kidney Injury IV: Diagnostic Studies and Prevention
 01:22
Acute Kidney Injury VI: Nursing Management
 01:22
Heart Failure Drugs: Diuretics
 01:30
Heart Failure V: Medical Management