Related Experiment Video
Updated: Jul 15, 2026

Sodium Taurocholate Induced Severe Acute Pancreatitis in C57BL/6 Mice
Published on: June 28, 2021
Hepatitis A-related acute liver failure and severe acute pancreatitis with prolonged cholestasis
Zakeer Hussain Gundluru1, Venkatesh Vaithiyam2, Lalit Chandra Kummetha1
1Senior Resident, Department of Gastroenterology, GB Pant Institute of Postgraduate Medical Education and Research, New Delhi, India.

Abstract:
Acute hepatitis A virus (HAV) infection is typically self-limiting but may rarely lead to severe hepatic and extra-hepatic complications. However, HAV-related acute liver failure may lead to complicated acute pancreatitis, and bilateral pleural effusions requiring drainage, and prolonged cholestatic hepatitis.
More Related Videos
 07:10
Establishment of a Mouse Severe Acute Pancreatitis Model using Retrograde Injection of Sodium Taurocholate into the Biliopancreatic Duct
Published on: April 1, 2022
 09:44
Generation of a Rat Model of Acute Liver Failure by Combining 70% Partial Hepatectomy and Acetaminophen
Published on: November 27, 2019
Related Concept Videos
 01:25
Acute Pancreatitis I: Introduction
 01:27
Acute Pancreatitis I: Introduction
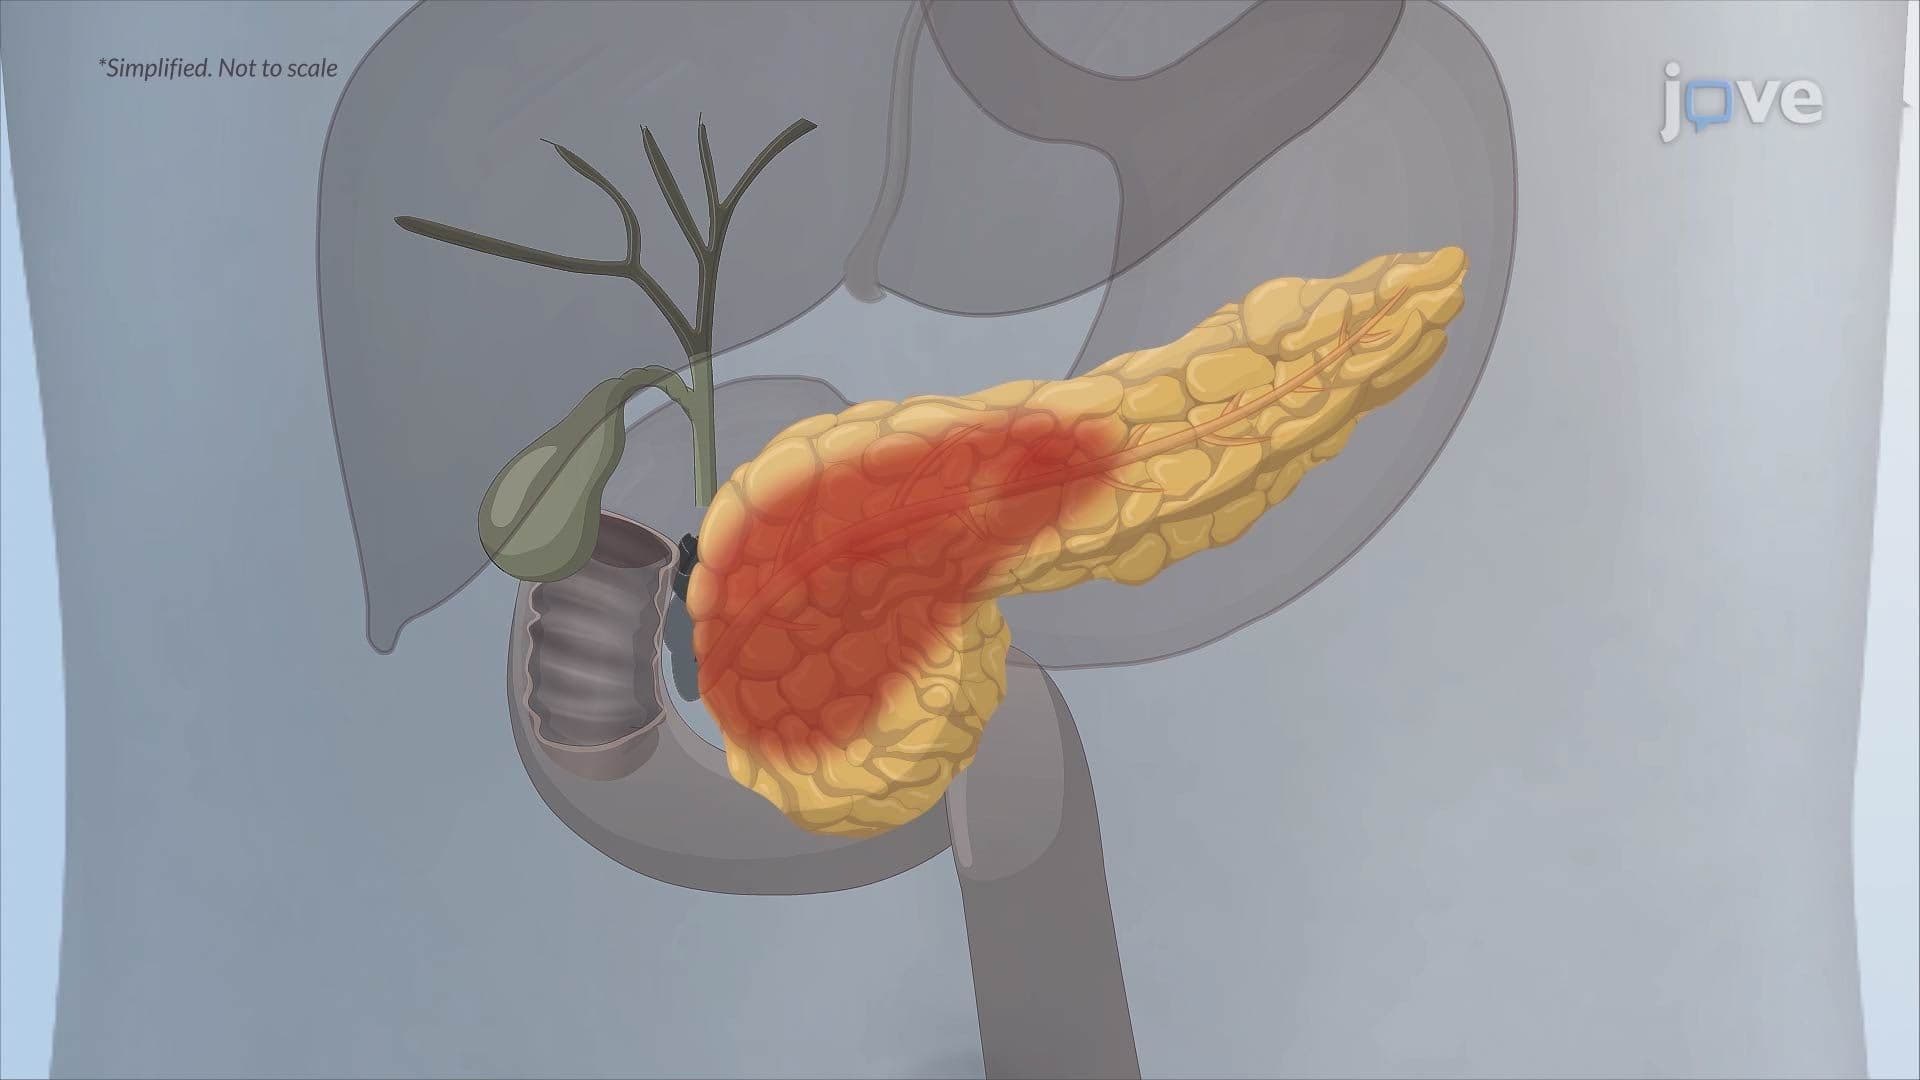
Acute pancreatitis is characterized by rapid inflammation of the pancreas, often caused by factors like gallstone blockage or excessive alcohol consumption. Chronic pancreatitis, on the other hand, is a slow, progressive inflammation that may result from long-term alcohol abuse, obstructions in the pancreatic duct, or genetic factors.
The causes of acute pancreatitis include:
 01:25
Chronic Pancreatitis I: Introduction
 01:24
Chronic Pancreatitis I: Introduction
Pancreatitis is the inflammation of the pancreas, which occurs when the immune system becomes active and causes swelling, pain, and disruptions in organ function. Pancreatitis can manifest as either an acute or chronic condition.
Acute pancreatitis arises suddenly and lasts for a brief duration, while chronic pancreatitis is a long-term affliction...
 01:21
Chronic Pancreatitis II: Pathophysiology
 01:21
Acute Pancreatitis II: Pathophysiology