Related Experiment Video
Updated: Jul 16, 2026
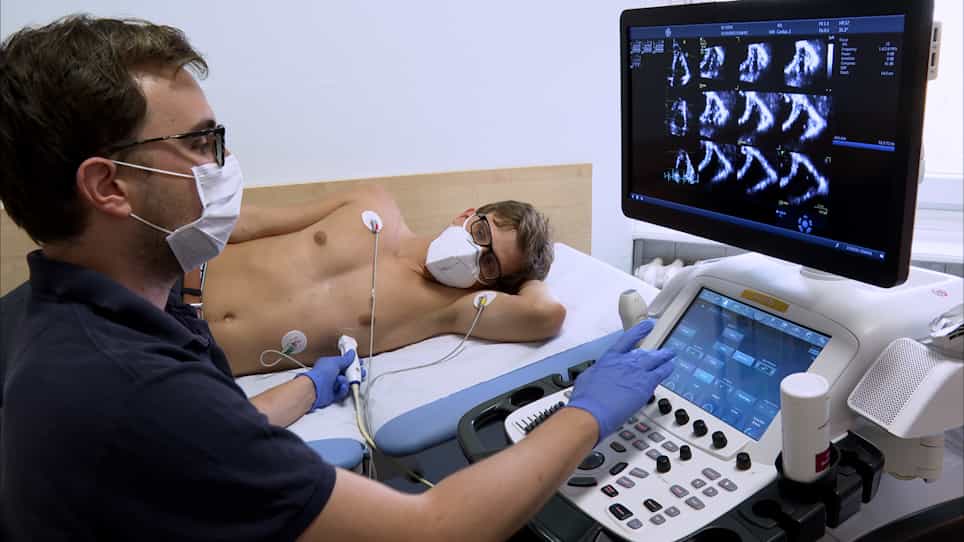

Morphological and Functional Assessment of the Right Ventricle Using 3D Echocardiography
Published on: October 28, 2020
Multimodality Imaging of Pulmonary Regurgitation and Right Ventricular Remodeling in Adults with Repaired Tetralogy
1Department of Cardiology, King Abdulaziz Medical City, Ministry of National Guard Health Affairs, King Abdullah International Medical Research Center, College of Medicine, King Saud Bin Abdulaziz University for Health Sciences, Jeddah, Saudi Arabia, alrahimija@gmail.com.

Introduction:
Chronic pulmonary regurgitation (PR) is a common late sequela after repair of Tetralogy of Fallot (TOF) and contributes to progressive right ventricular (RV) dilation, dysfunction, and adverse clinical outcomes. Multimodality imaging plays a central role in longitudinal assessment and in informing the timing of pulmonary valve replacement (PVR).
Methods:
We report a single-center, retrospective case series of seven adults with surgically repaired TOF followed at a tertiary care center. Each patient underwent serial transthoracic echocardiography (TTE) and at least two cardiac magnetic resonance (CMR) examinations over follow-up periods ranging from 5 to more than 15 years. PR severity was classified using CMR-derived regurgitant fraction according to established thresholds. RV size, systolic function, right ventricular outflow tract (RVOT) morphology, and clinical outcomes including PVR were recorded. Analyses were descriptive given the small sample size and heterogeneous nature of the cohort.
Results:
All seven patients (4 female, 3 male) survived to the most recent follow-up in 2025. PR was present in every patient, with CMR regurgitant fractions ranging from 21% to 57% at latest follow-up. Greater PR severity was associated with larger RV end-diastolic volume index (RVEDVi) and lower RV ejection fraction (RVEF) on serial imaging. RVEDVi ranged from 77 to 163 mL/m2 and RVEF from 37% to 61%. Qualitative concordance between TTE and CMR for RV remodeling was observed in 6 of 7 patients (86%). Several RVOT morphologic patterns were observed: patch-augmented RVOT with dilation, subpulmonic narrowing with turbulent flow acceleration, asymmetric branch pulmonary artery anatomy, and prosthetic pulmonary valve degeneration. Three patients underwent PVR during follow-up for severe PR, RVEDVi ≥150 mL/m2, declining RVEF, or symptomatic deterioration, and demonstrated post-procedural stabilization of RV size and improved functional status.
Conclusions:
In this single-center case series, integrated TTE and CMR provided complementary structural and functional information across a heterogeneous spectrum of post-repair RVOT anatomy, with CMR offering superior quantitative resolution of RV volumes and regurgitant fraction. The observed phenotypic variability illustrates the importance of multimodality, individualized surveillance in adults with repaired TOF, and reinforces the role of imaging integrated with clinical assessment in PVR decision-making.
Related Concept Videos
 01:22
Aortic Regurgitation II: Clinical Features and Diagnostic Tests
 01:23
Mitral Stenosis II: Clinical features and Diagnostic Tests
 01:20
Mitral Regurgitation I: Introduction
 01:23
Mitral Regurgitation II: Clinical Features and Diagnostic Tests
 01:15
Aortic Regurgitation I: Introduction
 01:25
Mitral Regurgitation III: Medical Management