Related Experiment Video
Updated: Jul 16, 2026
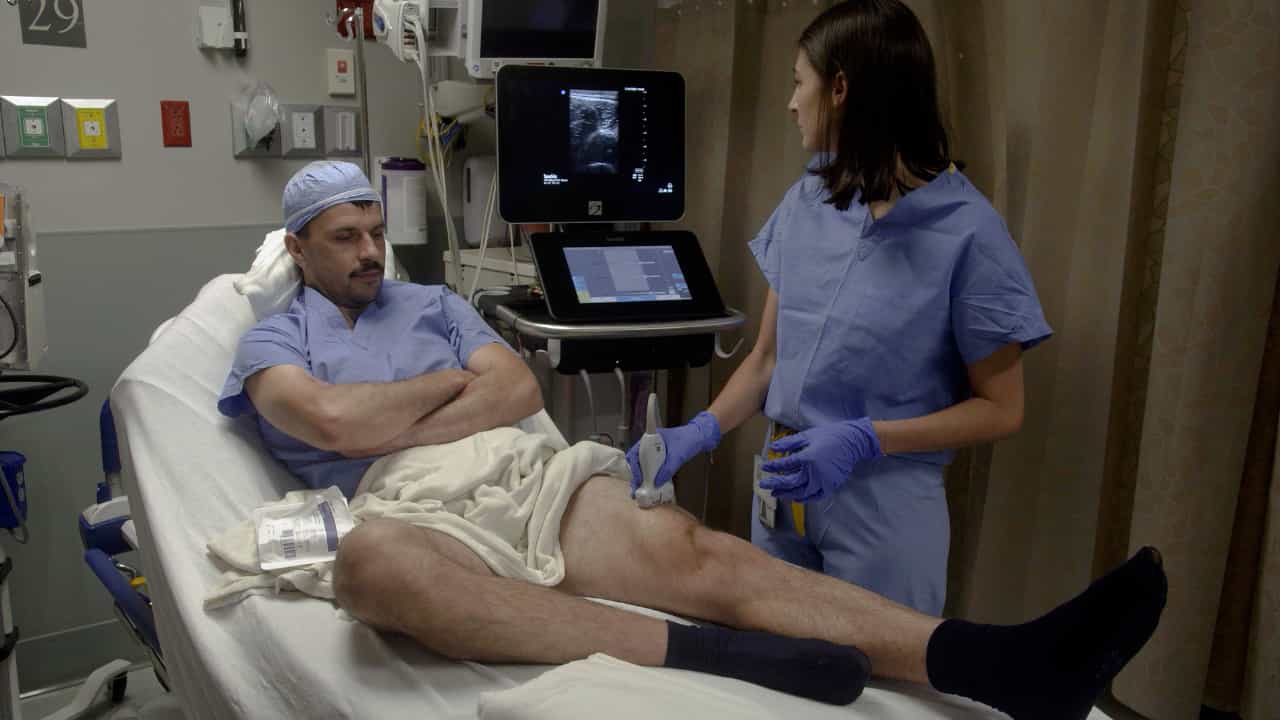
Identifying Frailty Using Point-of-Care Ultrasonography: Image Acquisition and Assessment
Published on: July 26, 2024
Association of the Primary Care Frailty Index with Postoperative Outcomes in Older Patients Undergoing Major
Andrea Costanzi1, Nicola Fazzini1, Lara Verdi2
1General Surgery Unit, San Leopoldo Mandic Hospital, ASST Lecco, 23807 Merate, Italy.

Abstract:
Background/Objectives: Frailty is increasingly recognized as a major determinant of postoperative outcomes in older patients undergoing oncologic surgery. The Primary Care Frailty Index (PC-FI), a deficit accumulation-based instrument derived from routinely available clinical information, has recently been proposed as a practical frailty assessment tool. However, evidence supporting its application in gastrointestinal surgical oncology remains limited. Methods: We conducted a retrospective cohort study including patients aged ≥65 years who underwent elective major colorectal or gastric cancer surgery between January 2022 and October 2025 at a tertiary Italian hospital. Patients with a PC-FI > 0.07 were included and categorized as having mild (0.07-0.13) or moderate-to-severe frailty (≥0.14). Postoperative outcomes included the Comprehensive Complication Index (CCI), Clavien-Dindo classification, and length of hospital stay. Receiver operating characteristic (ROC) analysis was performed to compare the discriminative performance of PC-FI, ASA classification, and the ACS Surgical Risk Calculator. Results: Ninety-two patients met the inclusion criteria. Patients with moderate-to-severe frailty were significantly older and had higher ASA class, Charlson Comorbidity Index, and ACS morbidity estimates than mildly frail patients. They also experienced a greater postoperative complication burden (mean CCI 25.96 vs. 16.40, p = 0.02) and longer hospital stay (9.89 vs. 7.43 days, p = 0.01). ROC analysis demonstrated modest discriminative performance for PC-FI (AUC 0.63), comparable to ASA classification (AUC 0.68) and the ACS morbidity score (AUC 0.70), without statistically significant differences among the three instruments. Conclusions: Higher PC-FI scores were associated with increased postoperative morbidity and prolonged recovery following major gastrointestinal oncologic surgery. Although its discriminative performance was modest and does not support its use as a stand-alone risk prediction tool, the PC-FI may represent a simple first-line frailty screening instrument to identify older patients who could benefit from comprehensive multidisciplinary perioperative assessment.
