Related Experiment Video
Updated: Jul 16, 2026
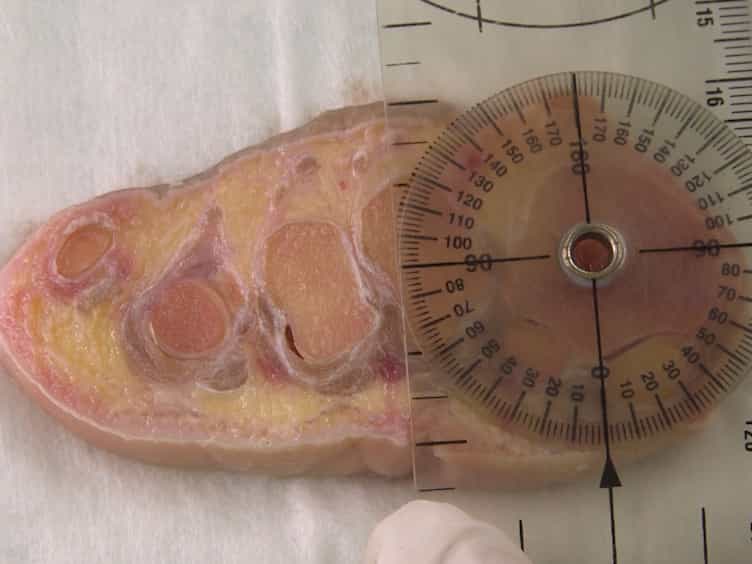

An Anatomical Study of Nerves at Risk During Minimally Invasive Hallux Valgus Surgery
Published on: February 17, 2018
Assessment of Medial Eminence Resection Timing in Hallux Valgus Surgery Using Patient-Specific Three-Dimensional
Ahmet Atilla Abdioğlu1, Göksu Yavuz Abdioğlu2
1Department of Orthopaedics and Traumatology, Trabzon Faculty of Medicine, Trabzon University, 61030 Trabzon, Turkey.

Abstract:
Background/Objectives: Distal chevron metatarsal osteotomy (DCMO) is one of the most commonly performed procedures for hallux valgus (HV) correction. Although medial eminence resection is routinely performed during DCMO, the effect of its timing on lateral translation, angular correction, and osteotomy contact area remains unclear. The aim of this study was to assess how the timing of medial eminence resection affects lateral translation, angular correction, and osteotomy contact area. Methods: Patient-specific first metatarsal models were generated from computed tomography data of 14 patients with HV using three-dimensional printing. Four groups were established according to medial eminence resection timing (before or after osteotomy) and lateral translation strategy (fixed 7 mm translation or preservation of a 5 mm contact width). DCMO was simulated in all specimens. Osteotomy contact area and the first metatarsal axis change angle (MACA) were measured and compared between the groups. Results: Under the fixed 7 mm translation condition, delaying medial eminence resection until after osteotomy resulted in a significantly larger osteotomy contact area than resection before osteotomy (236.50 ± 37.78 vs. 201.07 ± 22.54 mm2; p < 0.001). When lateral translation was limited by preservation of a 5 mm osteotomy contact width, delayed medial eminence resection achieved significantly greater angular correction (MACA: 20.71 ± 1.64° vs. 15.36 ± 1.45°; p < 0.001), while maintaining a comparable osteotomy contact area. Conclusions: Delaying medial eminence resection until after DCMO may allow greater lateral translation and angular correction while preserving osteotomy contact area in HV correction.