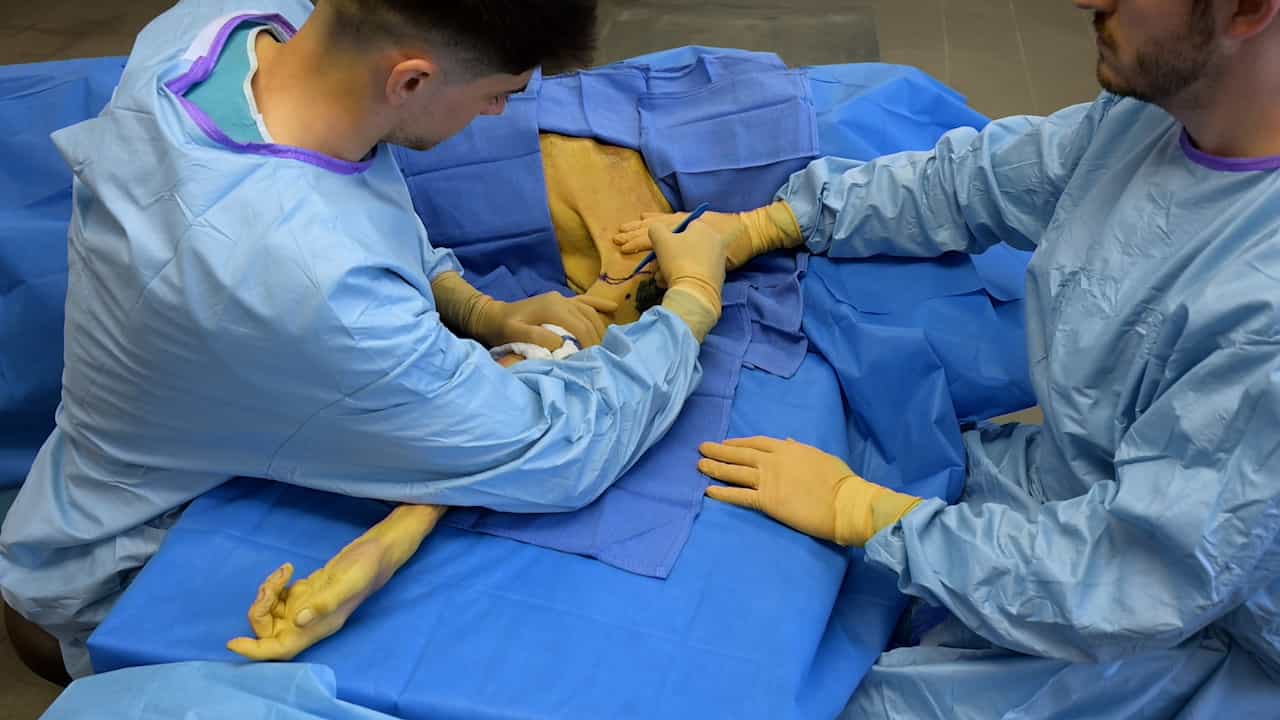
Related Experiment Video
Updated: Jul 16, 2026


Surface Electromyographic Biofeedback as a Rehabilitation Tool for Patients with Global Brachial Plexus Injury Receiving Bionic Reconstruction
Published on: September 28, 2019
Transhumeral Amputation with Biceps Tenodesis Sling for Flail Shoulder After Irreversible Brachial Plexus Injury in
Alexander Gardetto1,2, Gianluca Marcaccini3, Ludovico Coldebella3
1Competence Center for Bionic Prosthetics, Department of Plastic, Aesthetic and Reconstructive Surgery with Hand Surgery, Brixsana Private Clinic, 39042 Bressanone, Italy.

Abstract:
Background: Irreversible brachial plexus injury can leave patients with a painful, insensate, and nonfunctional flail limb, often after failed reconstructive attempts and with limited remaining surgical options. This study describes a modified transhumeral amputation technique incorporating a passive biceps brachii traction sling to improve residual limb stability and prosthetic readiness in this challenging setting. Methods: This retrospective, uncontrolled five-case series assessed the feasibility, perioperative safety, descriptive clinical outcomes, and early prosthetic integration of transhumeral amputation with a biceps brachii-based traction sling. Eligible patients had irreversible brachial plexus palsy, complete loss of useful upper-limb function, chronic shoulder instability or traction-related symptoms, pain, and persistent distress related to the paralysed limb as a burdensome nonfunctional appendage. Outcomes included the Disabilities of the Arm, Shoulder and Hand (DASH) score, Visual Analog Scale (VAS) for pain, and SF-36 Physical Functioning and Emotional Well-Being domains. Results are reported descriptively as individual values and medians without hypothesis testing. Results: All five patients completed follow-up, which reached 30 months. After combined transhumeral amputation, biceps sling construction, RPNI, rehabilitation, and prosthetic fitting, patient-reported scores changed in this small uncontrolled series as follows. The median DASH score changed from 64 preoperatively to 50 postoperatively; in this context, DASH reflects global perceived disability and may be influenced by pain relief, altered expectations, prosthetic compensation, psychosocial adaptation, and the removal of a burdensome limb rather than restoration of upper-limb function. Median VAS pain score changed from 7 to 0; VAS captured overall pain intensity only and did not separately measure phantom limb pain, mechanical pain, neuropathic pain, deafferentation pain, or traction-related symptoms. SF-36 Physical Functioning changed from 75 to 100, and Emotional Well-Being from 75 to 100. Four patients were fitted with a myoelectric prosthesis, and one elected to use a cosmetic prosthesis. No postoperative surgical complications, socket-related complications, prosthesis abandonment, clinical shoulder dislocation, or obvious failure of the construct were observed. Two Paralympic athletes returned to competitive sport after rehabilitation. Conclusions: The combined procedure was technically feasible in five highly selected patients and was not associated with observed surgical or prosthetic complications during follow-up. After combined transhumeral amputation, biceps sling construction, RPNI, rehabilitation, and prosthetic fitting, patient-reported scores improved in this small uncontrolled series. The specific contribution of the biceps sling relative to amputation itself, RPNI, prosthetic rehabilitation, and patient selection remains unknown. Larger prospective studies with objective assessment of shoulder and stump stability are needed to validate these preliminary findings and refine patient-selection criteria.