Related Experiment Video
Updated: Aug 6, 2026
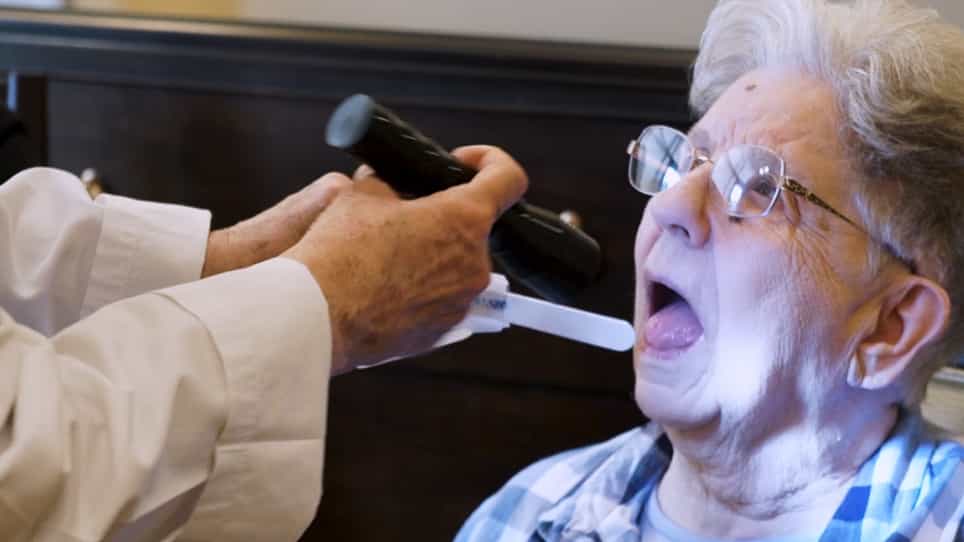

Oral Health Assessment by Lay Personnel for Older Adults
Published on: February 2, 2020
Oral Health Interventions for Culturally and Linguistically Diverse Children and Caregivers: A RE-AIM Systematic
1School of Dentistry, Faculty of Health, Medicine and Behavioural Sciences, The University of Queensland, Herston, QLD, Australia.

Objectives:
To characterise implementation reporting completeness of oral health interventions for culturally and linguistically diverse (CALD) children and caregivers using the RE-AIM framework (Reach, Effectiveness, Adoption, Implementation, Maintenance).
Methods:
Six databases (PubMed, Embase, CINAHL, Scopus, Web of Science, Cochrane Library) were searched for studies published 2010-2025 (PROSPERO CRD42024531750; PRISMA 2020). Eligible studies evaluated oral health interventions for CALD children aged 0-18 years from immigrant, refugee, or asylum-seeking backgrounds. Risk of bias was assessed with RoB 2, MMAT, and ROBINS-I. A 22-item RE-AIM coding tool assessed reporting completeness across five domains, categorised as low (< 60%), moderate (60%-69.9%), or high (≥ 70%).
Results:
Eleven studies were included (USA n = 9, UK n = 1, Australia n = 1; samples 36-1207). Two of three RCTs were rated High risk (RoB 2), all six non-randomised studies Serious risk (ROBINS-I), and two mixed-methods studies Low and Moderate (MMAT). Reporting completeness was predominantly low (72.7% of studies). Reach (84.1%) and Adoption (86.4%) were well-documented; Effectiveness (32.3%) showed the largest gap. Clinical outcomes (dmft/DMFT) were assessed in 36.4% of studies; cost was not reported in any study. Follow-up of 18 months or longer was limited to 18.2%, and attrition (5.6%-47%) in refugee populations reflected structural mobility rather than intervention failure.
Conclusions:
Reporting completeness was substantially incomplete for Effectiveness, cost, and long-term follow-up, though several gaps reflect structural constraints in CALD settings rather than reporting failures alone. Future studies should prospectively embed validated reporting checklists that capture intervention structure and implementation, select outcomes matched to the phase of evidence (proximal in early-phase, clinical in adequately powered trials), and design retention strategies suited to mobile and recently resettled populations.
Related Concept Videos
 01:21
Barriers to Effective Communication II
Cultural barriers:
Differences in values, beliefs, religion, knowledge, and tradition can significantly impact communication. Awareness of nonverbal cues is critical, especially when conversing with a patient from a different culture. What appears appropriate in one culture may be inappropriate in another.
Semantic barriers:
As a result of their tendency to use...
 01:21
Health Literacy
 01:30
Community Based Intervention
Foundations of Community Mental Health Programs
Central to the success of community-based interventions is the...