Related Experiment Video
Updated: Aug 6, 2026


Laparoscopic Non-Mesh Cerclage Pectopexy with Uterine Preservation for Pelvic Organ Prolapse
Published on: October 25, 2024
Should Maximum Urethral Closure Pressure Be Measured on Prolapse Reduction?
Hans Peter Dietz1, Ka Lai Shek2, Joseph Descallar3,4
1Sydney Urodynamic Centres, Sydney, Australia. hpdietz2@bigpond.com.

Introduction And Hypothesis:
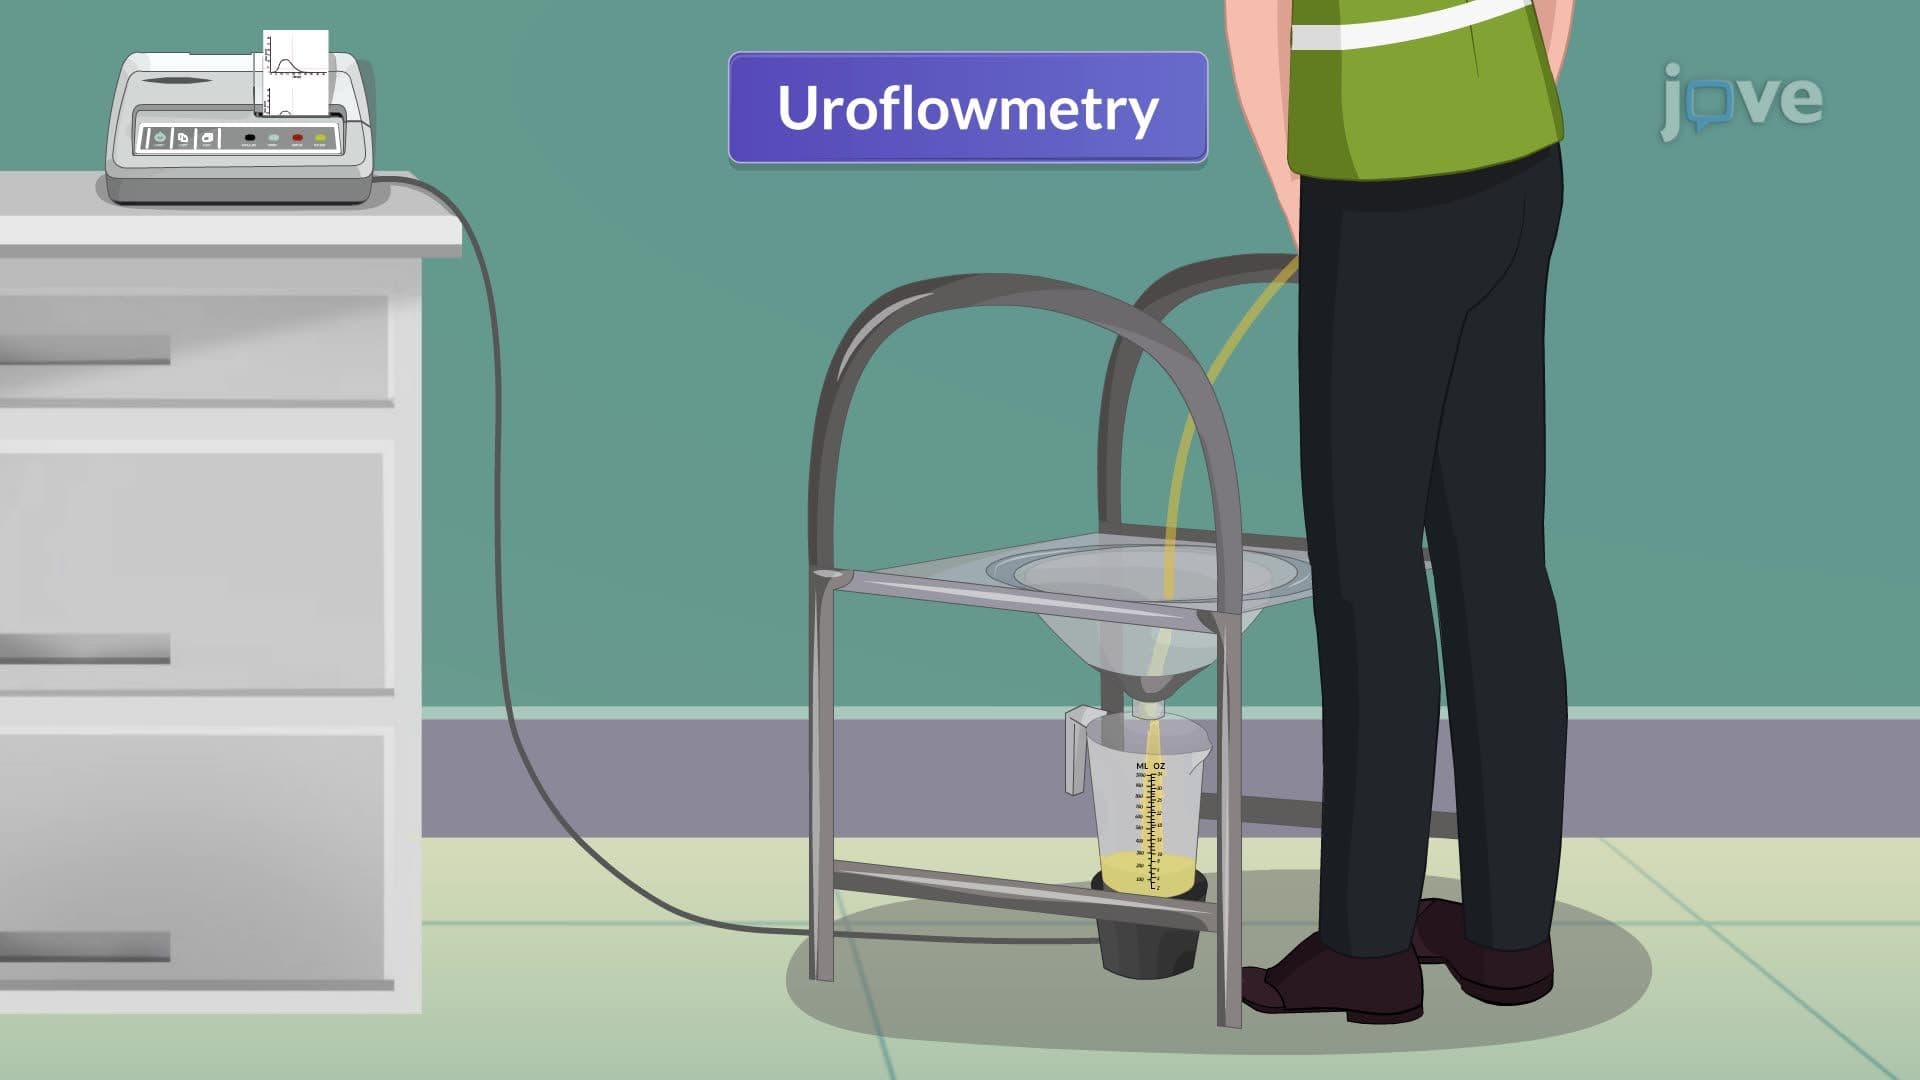
Maximum urethral closure pressure (MUCP) is a measure of urethral quality and is associated with urodynamic stress incontinence (USI). A confounder of this relationship is pelvic organ prolapse (POP). We investigated the effect of prolapse reduction on MUCP and its association with USI.
Methods:
We carried out an observational study using data sets of 1992 women seen at a tertiary urogynaecological centre in 2017-2024. All had undergone a questionnaire, POPQ examination and translabial ultrasound. MUCP was obtained after bladder emptying, at rest and during POP reduction. USI was rated mild, moderate, marked or severe. Associations between MUCP/MUCP on prolapse reduction and USI were tested using nominal regression. Nagelkerke R2 were used to compare association strength.
Results:
Of 1992 women seen for urodynamic testing, 1737 had MUCP obtained at rest and POP reduction. Most complained of stress urinary incontinence (72.8%), and 7% reported splinting to void. On clinical examination, 82.8% had significant prolapse. USI was diagnosed in 61.9%, detrusor overactivity in 22.6% and voiding dysfunction in 31.9%. Mean MUCP was 39.1 cm H2O at rest (standard deviation [SD] 18.2) and 33.9 (SD 17.6) on prolapse reduction (p < 0.001). This reduction was greater in women reporting splinting (p = 0.004) and weakly associated with Ba (p < 0.001), C (p < 0.001 and Bp (p = 0.02). MUCP at rest and MUCP on prolapse reduction were significant predictors of USI and USI grading (all p < 0.001). MUCP on prolapse reduction was not markedly superior to MUCP at rest in the association with USI grading (Nagelkerke R2 = 0.14 and 0.13 respectively).
Conclusions:
Symptoms of splinting and objective prolapse on POPQ predict a lower MUCP on prolapse reduction. However, as the latter does not significantly increase predictive value, prolapse reduction is probably unnecessary in clinical practice.