Related Experiment Video
Updated: Aug 6, 2026
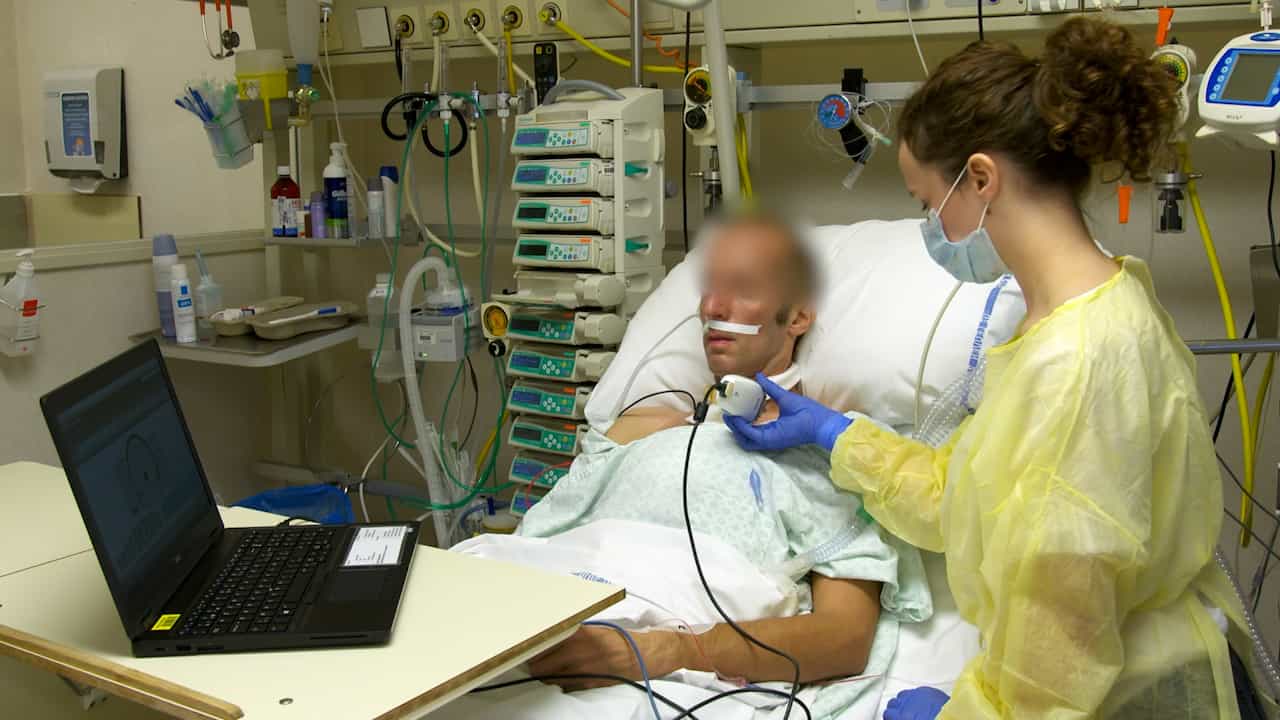
Inspiratory Muscle Training as an Adjunct to the Treatment of Weaning Failure in Critically Ill Patients: A Practical Guide
Published on: January 30, 2026
Longitudinal analysis of inspiratory support requirements in obesity hypoventilation syndrome: is NIV de-escalation
Vivien Moro1, Zsuzsanna Takacs2, Szabolcs Baglyas2
1Department of Anesthesiology and Intensive Therapy, Semmelweis University, Budapest, Hungary moro.vivien@semmelweis.hu.

Background:
Optimal long-term management and inspiratory support requirements remain debated in obesity hypoventilation syndrome (OHS).
Objectives:
This prospective, observational study assessed inspiratory support requirements in OHS patients initiating noninvasive ventilation (NIV) after acute hypercapnic respiratory failure, using a volume-assured mode targeting normocapnia.
Methods:
Ventilator data and clinical parameters were collected at baseline, 1 month, 3 months, 6 months and 12 months after initiation of NIV. Inspiratory support requirements were assessed using driving pressure and apparent respiratory system compliance and compared over time using the Wilcoxon test and Friedman analysis of variance. Groups with persistent and minimal inspiratory support needs at 1 year were compared using Mann-Whitney, χ2 and Cochran Q tests.
Results:
Of 40 enrolled patients, 39 completed the study. Therapeutic adherence (37 (94.9%)) and efficacy (35 (89.7%)) were high. Inspiratory support requirements decreased over the study period (12.1 (9.6-14.9) to 9.9 (6.3-12.2) cmH₂O, p<0.001), though 84.6% of patients still required >5 cmH₂O driving pressure. Initial driving pressure, higher minute ventilation and higher apparent respiratory system compliance were associated with reduced support requirements after 1 year, but no baseline parameter reliably predicted minimal support need. Reduced ventilatory support at 6 months demonstrated the strongest correlation with maintaining lower driving pressure at 12 months.
Conclusions:
Inspiratory support needs reduce over 12 months in OHS patients acutely initiated on long-term NIV, but few patients showed only minimal inspiratory support requirements to maintain normocapnia. Reliable reduction was apparent after 6 months of treatment, suggesting that respiratory muscle recovery is slower than previously assumed. Further studies are needed to verify whether an initial 'hit hard' approach with sequential de-escalation of ventilatory support results in optimal outcome.
Related Concept Videos
 01:25
Hyperpnea and Hyperventilation
 01:23
Mechanical Ventilation III: Noninvasive Ventilation
Noninvasive Positive-Pressure Ventilation (NIPPV)
 01:27
Chronic Obstructive Pulmonary Disease-IV: Assessement and Diagnostic Studies
Medical History
 01:23
Mechanical Ventilation II: Invasive Ventilation
Negative-Pressure Ventilators
Negative-pressure ventilators create a vacuum around the chest or body to draw air into the lungs, simulating breathing. This method does not require an...
 01:29
Mechanical Ventilation I: Indication and Settings
 01:21
Acute Respiratory Failure-II
The underlying physiological abnormalities that contribute to hypoxemic respiratory failure include: