Related Experiment Video
Updated: Aug 11, 2026
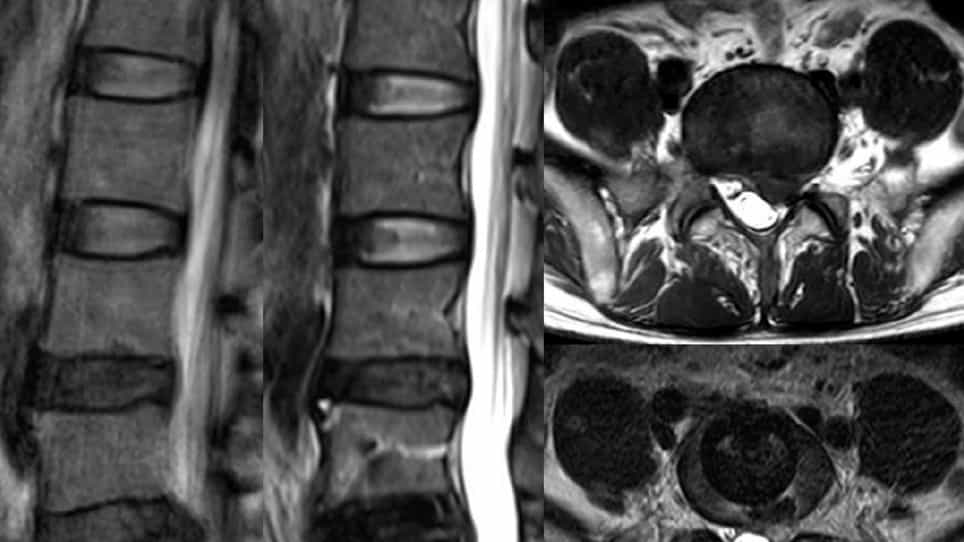
A Mobile Outside-in Technique of Transforaminal Lumbar Endoscopy for Lumbar Disc Herniations
Published on: August 7, 2018
Minimally invasive tubular lumbar microdiscectomy in pediatric patients: a single-center case series
Nick De Oliveira1, Sam Kavarana1, Jim Rogers1
1Vanderbilt University School of Medicine, Nashville, TN, USA.

Purpose:
Minimally invasive tubular lumbar microdiscectomy (MIS-MCD) is used for lumbar disc herniation (LDH) in adults, but pediatric data remain limited. This study aimed to evaluate clinical presentation, perioperative outcomes, and recovery patterns after MIS-MCD, and to explore risk factors for reherniation and reoperation in a pediatric cohort.
Methods:
We performed a retrospective case series of consecutive pediatric patients undergoing primary single-level MIS-MCD for LDH from 2014-2024 at a tertiary center by a single surgeon. Patients with primarily traumatic, neoplastic, or infectious pathology were excluded. Primary outcomes included early symptom improvement, return to activities, reherniation, and reoperation. Risk factors for reherniation were explored using Fisher's exact tests.
Results:
Thirty-four patients were included (mean age 16.7 ± 1.7 years; 55.9% male; mean BMI 30.6 ± 7.4 kg/m2). Most participated in organized sports (58.9%), with sport/exertional mechanisms being the most common identifiable cause (41.2%). Congenital spinal stenosis (CSS) was present in 20.6%. Mean symptom-to-surgery interval was 9.2 ± 8.3 months. Length of stay was 0.5 ± 0.6 days, median blood loss was 15 mL, and no durotomies occurred. Initial symptom improvement was reported by 94.1%, and 79.4% returned to prior activities. Over a median follow-up of 20.4 months, reherniation occurred in 8 patients (23.5%) and reoperation in 6 (17.6%). Reherniation was significantly associated with CSS (62.5% vs. 7.7%; p < 0.001). All reoperations were repeat MIS-MCD; none required fusion.
Conclusion:
MIS-MCD is safe and effective in pediatric patients. Reherniation is concentrated in patients with CSS, suggesting preoperative canal narrowing identification may guide counseling and surveillance.
Insights
Minimally invasive tubular lumbar microdiscectomy (MIS-MCD) is safe for pediatric lumbar disc herniation (LDH). Congenital spinal stenosis (CSS) is a key risk factor for reherniation in these young patients.
Area of Science:
- Neurosurgery
- Pediatric Orthopedics
- Spinal Surgery
Background:
- Minimally invasive tubular lumbar microdiscectomy (MIS-MCD) is a standard treatment for adult lumbar disc herniation (LDH).
- Limited data exist on MIS-MCD outcomes in pediatric populations.
- Pediatric LDH presents unique challenges and requires specific considerations for surgical management.
Purpose of the Study:
- To evaluate the clinical presentation, perioperative outcomes, and recovery patterns of pediatric patients undergoing MIS-MCD.
- To identify risk factors associated with reherniation and reoperation following MIS-MCD in children.
- To assess the safety and efficacy of MIS-MCD in a pediatric cohort.
Main Methods:
- Retrospective case series of pediatric patients (2014-2024) undergoing primary single-level MIS-MCD for LDH.
- Exclusion of patients with traumatic, neoplastic, or infectious spinal pathology.
- Analysis of primary outcomes including symptom improvement, return to activities, reherniation, and reoperation rates.
Main Results:
- Thirty-four pediatric patients (mean age 16.7 years) were included; 20.6% had congenital spinal stenosis (CSS).
- High rates of initial symptom improvement (94.1%) and return to activities (79.4%) were observed.
- Reherniation occurred in 23.5% and reoperation in 17.6%, with CSS significantly associated with reherniation (p < 0.001).
Conclusions:
- MIS-MCD demonstrates safety and effectiveness in pediatric patients with LDH.
- Congenital spinal stenosis is a significant risk factor for reherniation in this population.
- Preoperative identification of canal narrowing in patients with CSS may inform patient counseling and surveillance strategies.