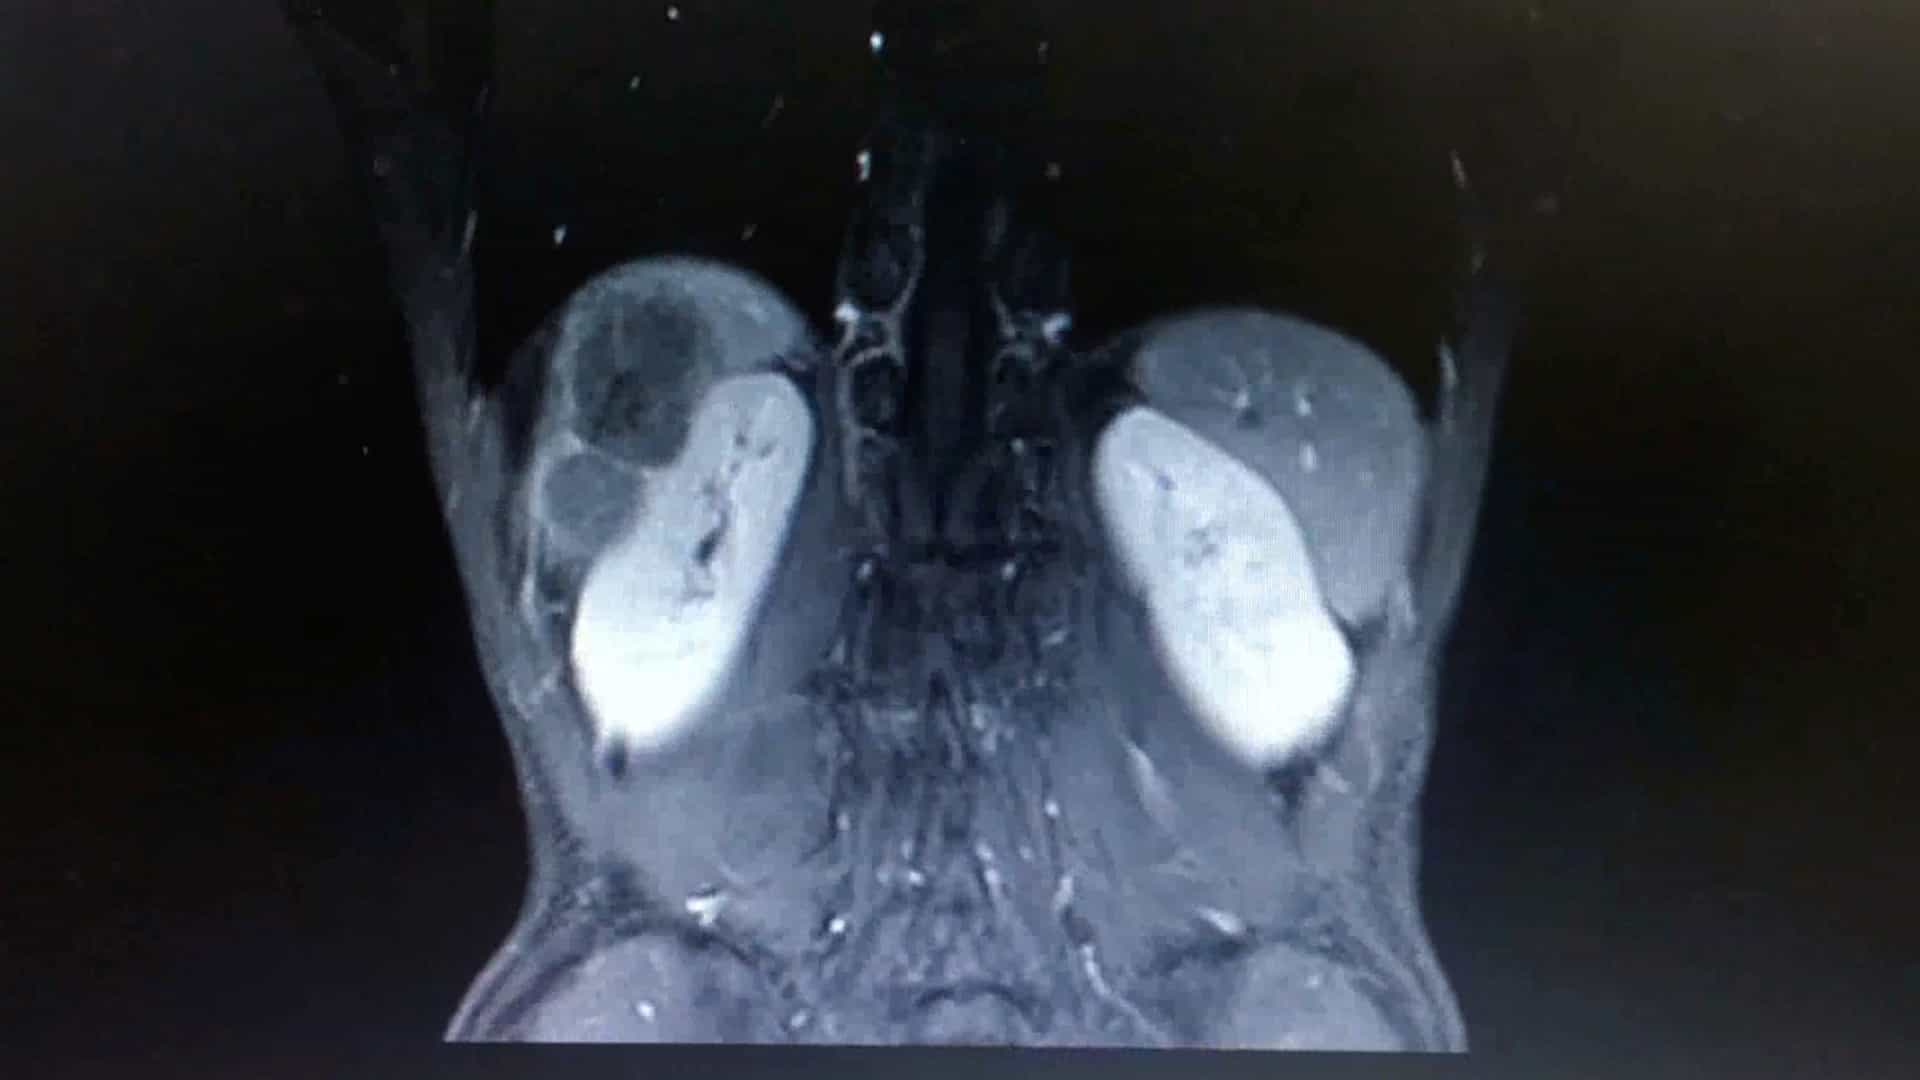
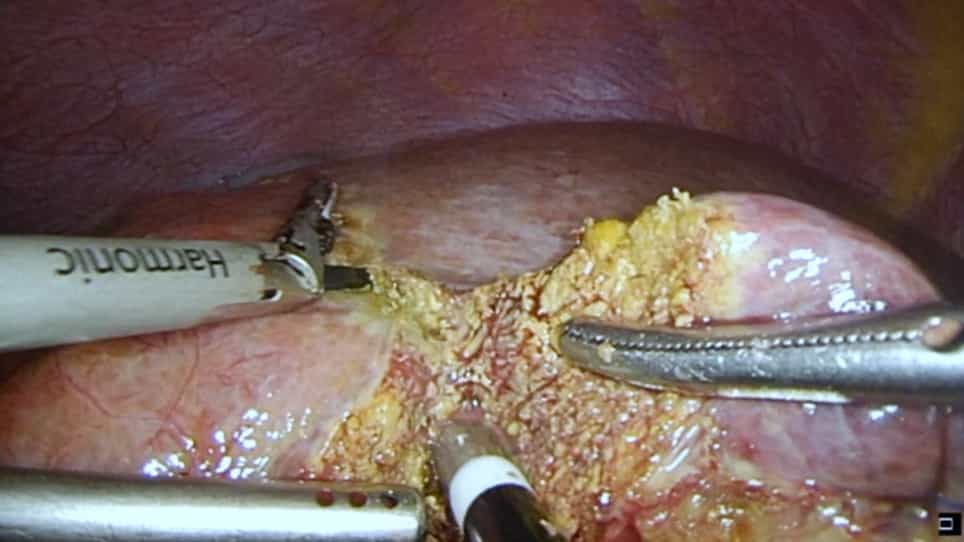
Related Experiment Video
Updated: Aug 6, 2026

Laparoscopic Left Hemihepatectomy Combined with Caudate Lobe Resection
Published on: April 11, 2025
Perioperative mortality and survival after lymph node excision in hepatocellular carcinoma: a national cancer
Huisong Lee1, Kyung Uk Jung2, Michael Luu3
1Department of Surgery, Ewha Womans University Mokdong Hospital, Ewha Womans University College of Medicine, Seoul, Republic of Korea.

Background:
The oncologic benefit of lymph node excision (LNE) during hepatectomy for hepatocellular carcinoma (HCC) remains controversial. This study examined the association between LNE, perioperative mortality, and long-term survival following curative-intent liver resection.
Methods:
The National Cancer Database (2004-2021) was queried to identify patients who underwent curative hepatectomy for HCC. Patients who underwent liver transplantation, palliative surgery, or had distant metastases were excluded. Propensity score matching (PSM) was performed to balance patients undergoing hepatectomy with and without LNE. Multivariable logistic regression was used to identify factors associated with 30- and 90-day mortality. Overall survival (OS) was compared among patients according to LNE.
Results:
After matching (n = 8,728), all PSM-matched variables achieved standardized mean differences < 0.10, confirming excellent balance. LNE was independently associated with increased perioperative mortality. Removal of 1-3 lymph nodes was associated with increased odds of 30- and 90-day mortality (OR 1.37 and 1.38, respectively), while removal of ≥ 4 nodes conferred higher risk (OR 1.64 and 1.67, respectively). Older age, greater comorbidity burden, and advanced T stage were also associated with increased postoperative mortality. In survival analyses, OS did not differ significantly between No-LNE and pN0 groups (P = 0.151), with comparable 5-year survival rates and median survival.
Conclusions:
In this national cohort, LNE performed during curative hepatectomy for HCC was associated with increased postoperative mortality, without an apparent long-term survival benefit in patients with node-negative disease. These findings should be interpreted with caution given the observational design and inherent indication bias.