Related Experiment Video
Updated: Aug 6, 2026
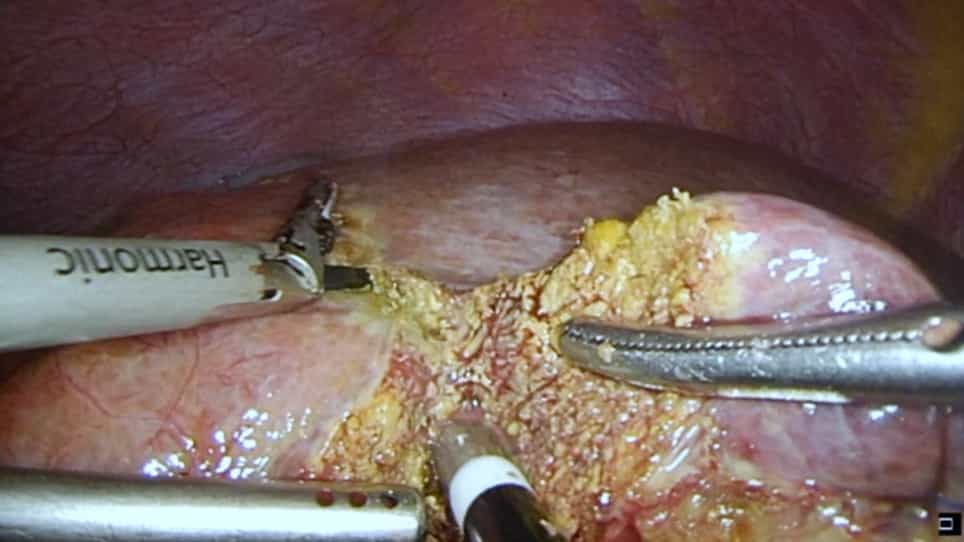
Application of Hemostatic Devices in Laparoscopic Hepatectomy
Published on: April 19, 2022
Predictive Value of Preoperative Thromboelastography, C-Reactive Protein, and Thrombomodulin for Postoperative
Yiling Hu1, Weifeng Shen1, Hui Zhou1
1Department of Laboratory Medicine, The First Hospital of Jiaxing, Affiliated Hospital of Jiaxing University, 314000 Jiaxing, Zhejiang, China.

Aim:
Postoperative complications following hepatectomy remain common and are closely associated with patient prognosis. Conventional preoperative assessment may not adequately capture perioperative coagulation disturbances, systemic inflammation, and endothelial injury. This study aimed to develop and internally validate a multidimensional preoperative prediction model integrating thromboelastography (TEG)-related parameters with inflammatory and endothelial biomarkers.
Methods:
This single-center retrospective cohort study included 195 consecutive patients who underwent elective hepatectomy between March 2022 and May 2025. The cohort was randomly divided into a training set (n = 136) and a validation set (n = 59) at an approximate 7:3 ratio. The primary outcome was the occurrence of Clavien-Dindo grade ≥II complications within 30 days postoperatively. All clinically relevant candidate variables were entered into a least absolute shrinkage and selection operator (LASSO) regression model for feature selection. Variables retained by LASSO were further evaluated before inclusion in the multivariable model. Two multivariable logistic regression models were subsequently constructed: a baseline clinical model (Model 1) and an extended biomarker model (Model 2), which additionally incorporated C-reactive protein (CRP), thrombomodulin (TM), and thromboelastography maximum amplitude (MA). Model discrimination, reclassification, calibration, and potential clinical utility were assessed, and Shapley Additive exPlanations (SHAP) were applied as a supplementary interpretability analysis.
Results:
A total of 195 patients were included, of whom 56 (28.72%) developed postoperative complications. The final model retained seven predictors: albumin, prothrombin time, portal hypertension, surgical approach, CRP, TM, and MA. Model 2 demonstrated superior discriminative performance compared with Model 1 in the training cohort (area under the curve (AUC) 0.88 vs. 0.74, p = 0.006); a similar advantage was observed in the validation cohort (AUC 0.84 vs. 0.67, p = 0.001). Model 2 also achieved higher net reclassification improvement (NRI) and integrated discrimination improvement (IDI) values in both cohorts. Incremental value analysis indicated that the performance gain of Model 2 was primarily attributable to MA, while CRP and TM provided only limited additional predictive value. Calibration and decision curve analyses further supported the overall performance and potential clinical utility of Model 2.
Conclusions:
The extended preoperative prediction model demonstrated superior overall predictive performance compared with the model based solely on conventional clinical indicators. This improvement was driven primarily by MA, while CRP and TM, included as exploratory biomarkers within the extended framework, contributed only modest incremental value. These findings should be considered preliminary and require confirmation in larger multicenter studies with external validation before broader clinical implementation.