Related Experiment Video
Updated: Aug 6, 2026
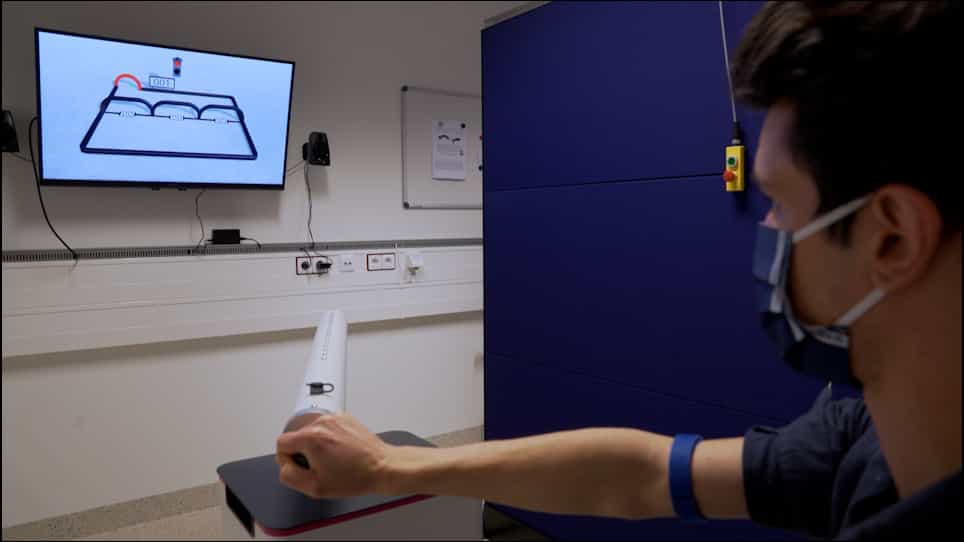

Investigating Pain-Related Avoidance Behavior using a Robotic Arm-Reaching Paradigm
Published on: October 3, 2020
Occupational Therapy Incorporating Cognitive Behavioral Therapy-Informed Components for Pain-Related Activity
Naoki Ohkusa1, Wataru Kukizaki2, Ryota Hayasaki3
1Department of Rehabilitation, Kenwakai Otemachi Hospital, Kitakyushu, JPN.

Abstract:
Postoperative pain involves not only nociceptive components but also psychological reactions such as anxiety, pain catastrophizing, and fear-avoidance, which may delay functional recovery. Although cognitive behavioral therapy (CBT) is well established for chronic pain, evidence on the use of CBT-informed components by rehabilitation professionals in the early postoperative phase after upper-limb fracture surgery remains limited. This report describes occupational therapy (OT) incorporating CBT-informed components (hereafter, CBT-informed OT) for a patient who exhibited disproportionate pain-related fear-avoidance after olecranon fracture surgery. A right-handed man in his 70s underwent open reduction and internal fixation with tension band wiring for a right olecranon fracture. On postoperative day three, he showed marked pain-related fear and avoidance of using the affected limb, with restricted activities of daily living (ADL) and inability to participate in work-related online meetings. Baseline assessment showed elbow active range of motion (AROM) of -45/80, pain on movement 6/10 on the Numerical Rating Scale (NRS), QuickDASH 76.5, Pain Catastrophizing Scale (PCS) 25, Pain Self-Efficacy Questionnaire (PSEQ) 20/60, and Canadian Occupational Performance Measure (COPM) performance and satisfaction scores of 2/10 for all identified goals. Because the baseline PCS was below the conventional cutoff, the clinical formulation identified low pain self-efficacy and fear-avoidance, rather than catastrophizing alone, as the central psychological drivers. A 12-week CBT-informed OT program was provided in three phases: (1) psychoeducation and cognitive restructuring, (2) graded goal-directed activity guided by COPM and the Aid for Decision-making in Occupation Choice for Hand (ADOC-H), and (3) pacing and self-management for return to occupational roles. At 12 weeks, the patient showed marked improvements: AROM -10/130, pain on movement 2/10 (change: -4), QuickDASH 12.5 (change: -64.0), PCS 1 (change: -24), and PSEQ 58 (change: +38). COPM performance and satisfaction improved from 2 to 10 (change: +8) for both short-term goals (independence in dressing and bathing) and the long-term goal (participation in work-related online meetings). The QuickDASH Work subscale, not assessed at baseline due to hospitalization, was 25 at 12 weeks, corresponding to mild-to-moderate residual difficulty. This single case suggests that CBT-informed OT may be a feasible approach for addressing pain-related fear-avoidance in the early postoperative phase after upper-limb fracture surgery. The temporally associated improvements in self-efficacy and occupational performance are consistent with the clinical formulation, although natural postoperative recovery cannot be excluded as a contributing factor. Controlled studies are needed to evaluate efficacy.

