A Rare Case of Subglottic Rosai-Dorfman-Destombes Disease Causing Fixed Upper-Airway Obstruction in an Adult Woman
Related Experiment Video
Updated: Aug 6, 2026
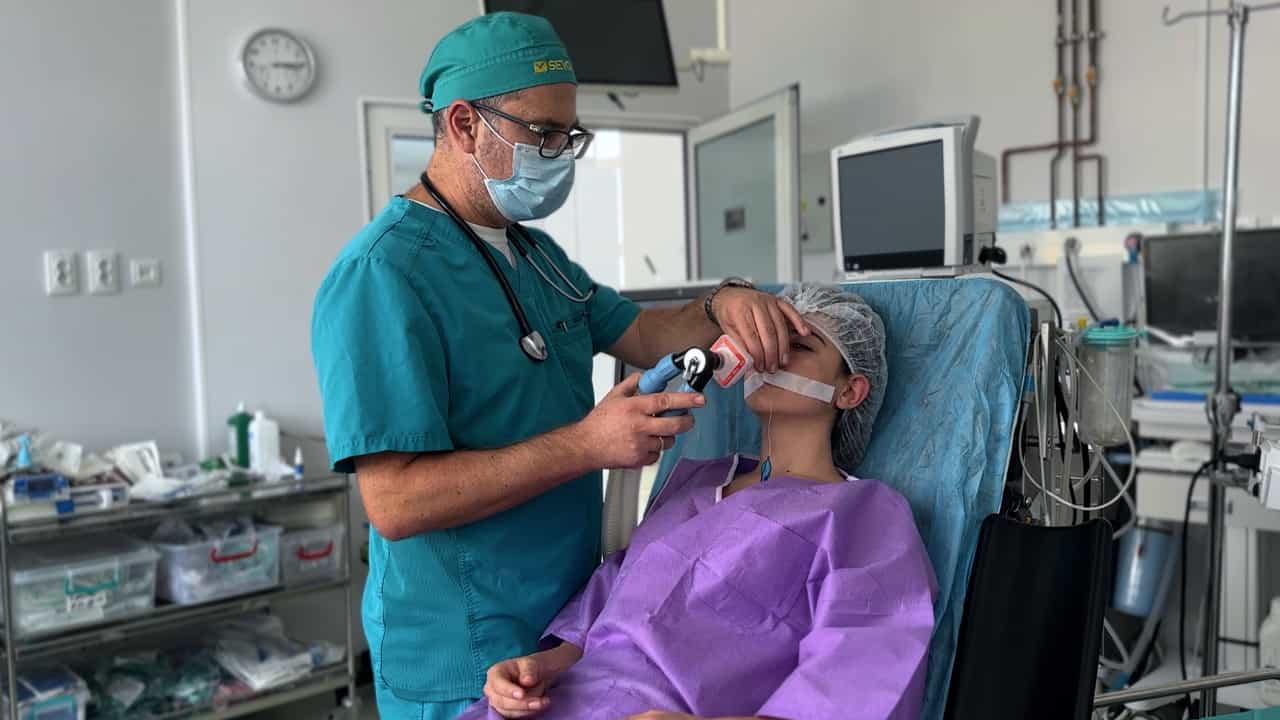
The Flexible Rhino-Laryngoscope for Awake Nasotracheal Intubation
Published on: August 2, 2024
Sheikh Abdullah1, Camryn Herbert1, Faryal Shoaib2
1Department of Internal Medicine, Louisiana State University Health Sciences Center, Shreveport, USA.

Introduction:
Rosai-Dorfman-Destombes disease (RDD) is a rare non-Langerhans cell histiocytosis that usually presents with painless cervical lymphadenopathy but may involve extranodal sites. Laryngeal or subglottic involvement is uncommon yet clinically significant because progressive fixed upper airway obstruction may initially resemble more common obstructive airway disease.
Case Description:
We report a 59-year-old lifelong non-smoker with a history of mediastinal lymphadenopathy who developed several months of progressive exertional dyspnoea and wheeze treated as moderate persistent asthma with escalating inhaled therapy and repeated systemic steroids, without sustained improvement. Pulmonary evaluation demonstrated only mild obstructive physiology with air trapping and reduced diffusing capacity, discordant with the patient's marked exertional limitation. On follow-up, she was noted to have audible biphasic stridor, prompting urgent evaluation for central airway obstruction. Flexible laryngoscopy revealed an exophytic subglottic mass causing approximately 50% fixed airway obstruction. She underwent tracheostomy for airway protection followed by excision of the lesion. Histology demonstrated a lymphoplasmacytic infiltrate with large S100 and CD68 positive histiocytes showing emperipolesis, consistent with extranodal RDD. Cross sectional imaging excluded multifocal disease. She was decannulated and remains asymptomatic under surveillance.
Conclusion:
This case underscores that fixed central airway obstruction can masquerade as refractory asthma and that biphasic stridor may be the critical bedside clue prompting reconsideration of the diagnosis. Although subglottic RDD is rare, delayed recognition may lead to life-threatening airway compromise. Compared with the usual nodal presentation and often indolent clinical course of RDD, isolated subglottic disease is unusual and clinically significant because diagnosis depends on biopsy of a structural airway lesion and localized disease may have a favourable prognosis after endoscopic treatment and surveillance.
Learning Points:
Progressive wheeze and dyspnoea with limited response to guideline-directed asthma therapy, particularly when symptom severity is disproportionate to spirometry, should prompt evaluation for non-asthma causes of airflow obstruction.Biphasic stridor is a key red flag for fixed central airway obstruction and warrants urgent airway visualization.Localized subglottic Rosai-Dorfman-Destombes disease, although rare, can be managed effectively with surgical debulking and temporary airway protection; systemic therapy is reserved for multifocal or organ threatening disease.

Related Concept Videos
 01:30
Cardiopulmonary Resuscitation V: Advanced Airway Management Techniques
 01:27
Esophageal Achalasia
 01:30
Esophageal Strictures-I: Introduction
Etiology
The primary cause of esophageal strictures is long-standing gastroesophageal reflux disease (GERD), accounting for about 70 to 80% of adult cases. Chronic acid reflux can lead to injury and scarring of the esophageal lining, culminating in...
 01:21
Tracheostomy Decannulation
Description of the Procedure
Decannulation refers to the permanent removal of the tracheostomy tube, signaling the resolution of the condition that initially necessitated the tracheostomy. The process requires a well-coordinated interplay between...
 01:22
Trachea
Anatomical Features:
Location: About half of the trachea is situated in the neck, anterior to the esophagus, and extends from the larynx (at the level of the...
 01:22
Cardiopulmonary Resuscitation II: ACLS Airway Management