Related Experiment Video
Updated: Aug 6, 2026
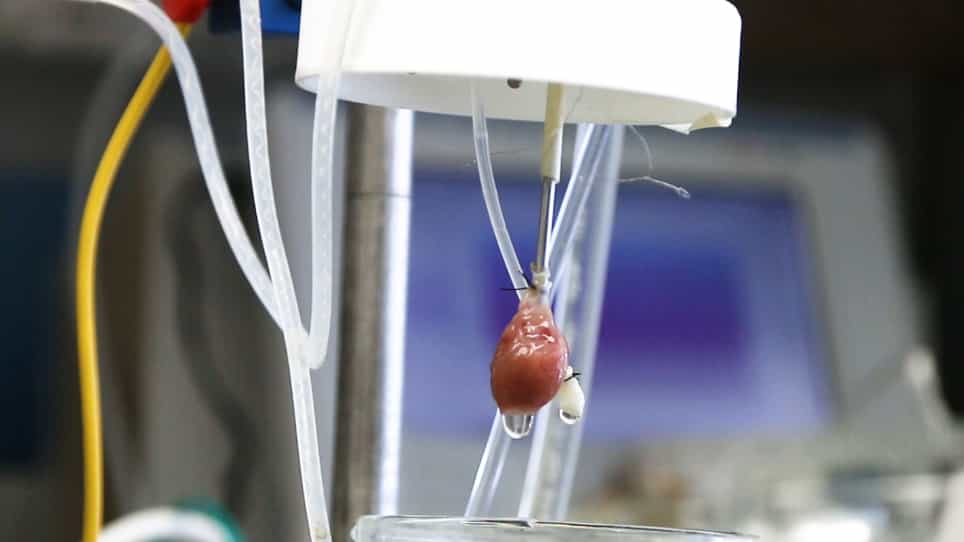

Pre-clinical Model of Cardiac Donation after Circulatory Death
Published on: August 2, 2019
Pre- and Immediate Postoperative Prediction Model for Organ Dysfunction or Death Early After Cardiac Surgery: A Post
Ellen Dresen1, Daren K Heyland2, Zheng Yii Lee1,3,4,5
1Department of Anaesthesiology, Intensive Care, Emergency and Pain Medicine University Hospital Würzburg Würzburg Germany.

Background:
Development of organ dysfunction or death is still common in patients undergoing cardiac surgery. Yet, current risk stratification tools fail to adequately incorporate both preoperative vulnerability and immediate postoperative physiological derangements. This study aims to develop a predictive model integrating these critical timepoints to identify high-risk patients for presence of organ dysfunction or death 48 hours after surgery.
Methods:
This is a post hoc analysis of an international, multicenter, randomized, controlled trial in patients undergoing cardiac surgery (n=1394). Prespecified patient characteristics (age, Clinical Frailty Scale, at nutrition risk, combined procedures, urgent surgery, moderate-severe chronic kidney disease, left ventricular ejection fraction, European System for Cardiac Operative Risk Evaluation II, cardiopulmonary bypass duration, sex, Charlson Comorbidity Index, and Sequential Organ Failure Assessment score) were included in logistic regression models employing bootstrap validation.
Results:
A total of 434 (31.1%) patients had organ dysfunction or died 48 hours after surgery. The preoperative model identified Clinical Frailty Scale, nutrition risk, urgent surgery and European System for Cardiac Operative Risk Evaluation II as significant predictors of organ dysfunction or death 48 hours after surgery (optimism-corrected area under the receiver operating characteristic curve, 0.644 [95% CI, 0.610-0.678]). Incorporation of postoperative variables (Sequential Organ Failure Assessment score at intensive care unit admission, and cardiopulmonary bypass duration) improved predictive performance (area under the receiver operating characteristic curve, 0.773 [95% CI, 0.745-0.801]).
Conclusions:
Incorporation of variables collected the day of surgery substantially improved the ability to predict organ dysfunction or death 48 hours after surgery compared with using presurgical variables only. This pragmatic, clinically actionable model may enable targeted resource allocation and personalized interventions and may provide a stratification tool for future research.
Registration:
URL: clinicaltrials.gov; Unique Identifier: NCT02002247.
