Related Experiment Video
Updated: Aug 6, 2026
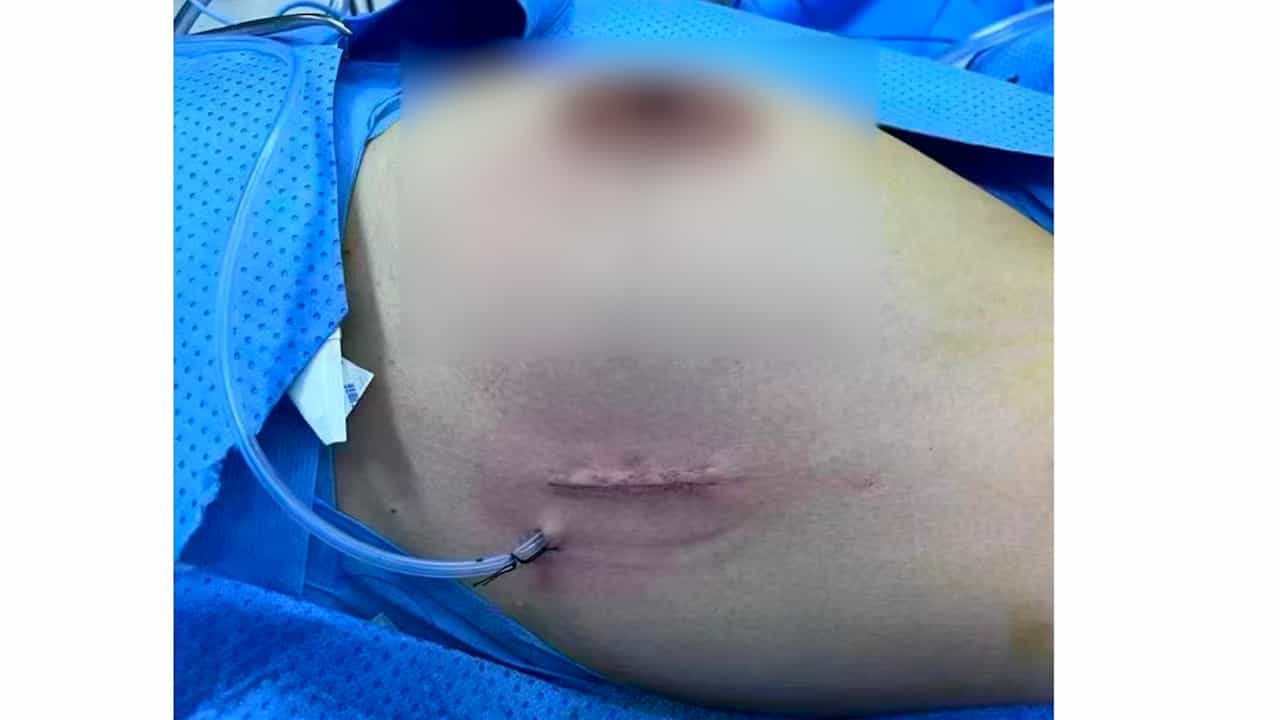
Single-port Non-liposuction Endoscopic Axillary Lymph Node Dissection in Breast Cancer Surgery
Published on: April 3, 2026
Station distribution of lymph node evaluation in surgically managed pulmonary carcinoid tumors: A 20-year
Serkan Uysal1, Ayşe Ali Hasan1, Yiğit Yılmaz1
1Department of Thoracic Surgery, Hacettepe University Faculty of Medicine, Ankara, Türkiye.

Background:
Pulmonary carcinoid tumors are rare lung neuroendocrine neoplasms in which the adequacy of lymph node evaluation remains debated, and real-world station-level staging patterns are incompletely described.
Methods:
We retrospectively reviewed consecutive patients who underwent surgical management for pulmonary carcinoid tumors or related neuroendocrine proliferation-spectrum lesions at a single institution between 2004 and 2024 (n=71). Primary analyses focused on pulmonary carcinoid tumors (n=66; typical n=53, atypical n=11, unclassified n=2). Pathologic extent was harmonized to the current ninth-edition staging framework. Kaplan-Meier survival estimates generated in Numiqo were cross-checked in SPSS.
Results:
Median age was 55 years, and 55/71 patients (77.5%) were female. Among 70 lung resections, anatomic resection was performed in 55/70 (78.6%) and sublobar resection in 15/70 (21.4%). Earlier cases were predominantly thoracotomy-based, whereas later cases increasingly underwent video-assisted thoracoscopic surgery; systematic nodal evaluation remained integral regardless of access route. Lymph node dissection or sampling was performed in 58/71 patients (81.7%), identifying nodal metastasis in 5/71 (7.0%), including two typical carcinoids with N2 disease and three atypical carcinoids (two N1, one N2). Among cases with documented nodal stations (45/58), a median of 5 stations was assessed, most commonly stations 7, 10, and 11. Median follow-up was 64.8 months; estimated 5-year overall survival was 93.2% and 5-year recurrence-free survival was 84.6%.
Conclusion:
Systematic nodal evaluation disclosed clinically meaningful occult disease, including in typical carcinoid. These findings support routine hilar-mediastinal staging and risk-adapted surveillance after resection and reinforce that minimally invasive surgery should preserve the same oncologic nodal intent as open surgery.

