Related Experiment Video
Updated: Aug 6, 2026
DIPLOMA Approach for Standardized Pathology Assessment of Distal Pancreatectomy Specimens
Published on: February 1, 2020
Impact of pathological diagnosis on postoperative outcomes after pancreatoduodenectomy: A nationwide cohort study
Jacob L van Dam1, Jelle C van Dongen1, Marc G Besselink2
1Department of Surgery, Erasmus MC Cancer Institute, Rotterdam, the Netherlands.

Background:
Benchmarking of surgical outcomes across institutions requires adjustment for established risk factors. Although pathological diagnosis is recognized as a determinant of postoperative morbidity after pancreatoduodenectomy, its independent impact on outcomes has not been systematically quantified at a national level. This study aimed to investigate the impact of pathological diagnosis on postoperative outcomes after pancreatoduodenectomy and to assess inter-hospital variation in case-mix.
Methods:
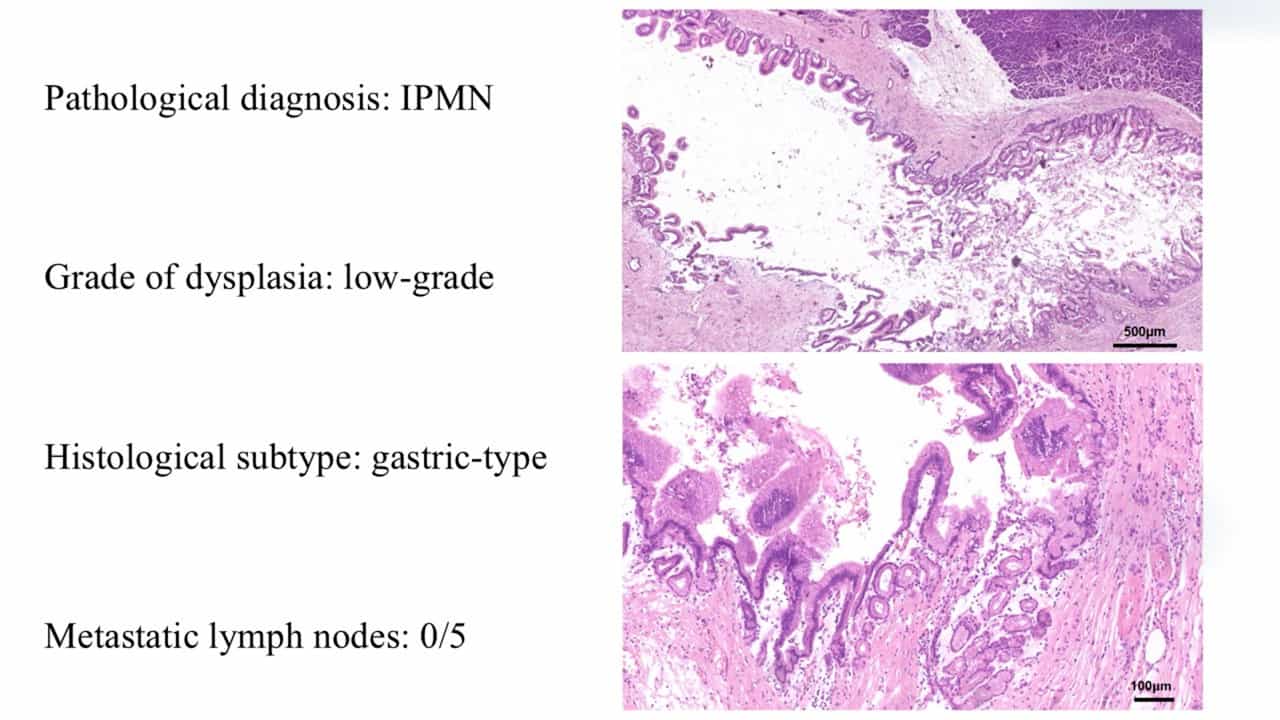
Data were obtained from the nationwide Dutch Pancreatic Cancer Audit. Postoperative complications were compared for pancreatic ductal adenocarcinoma (PDAC), distal cholangiocarcinoma (dCCA), ampullary adenocarcinoma (AAC), duodenal adenocarcinoma (DAC), non-invasive intraductal papillary mucinous neoplasm (IPMN), pancreatic neuroendocrine tumors (PanNET), chronic pancreatitis (CP), and Other Pathology. Multivariable logistic regression was used to identify independent risk factors for major complications (Clavien-Dindo grade ≥3).
Results:
Between 2014 and 2020, 4152 patients underwent pancreatoduodenectomy. The three most common diagnoses were PDAC (n = 1778; 42.8%), dCCA (n = 544; 13.1%), and AAC (n = 541; 13.0%). The rate of major complications differed between diagnoses (P < 0.001), and was lowest for CP at 21.8% and highest for PanNET at 43.9%. All diagnoses except CP showed a higher risk of major complications compared with PDAC, with CP showing no significant difference. The adjusted odds ratio for major complications was the highest for PanNET (2.59; 95% CI: 1.84-3.65) and DAC (2.32; 95% CI: 1.77-3.03).
Conclusions:
Pathological diagnosis is an independent risk factor for complications after pancreatoduodenectomy, with PanNET and DAC carrying the highest risk. Given the substantial inter-hospital variation in case-mix, audits comparing postoperative outcomes across institutions should incorporate pathological diagnosis as a covariate.