Related Experiment Video
Updated: Aug 6, 2026


Optimized Management of Endovascular Treatment for Acute Ischemic Stroke
Published on: January 18, 2018
Post-Thrombectomy FLAIR Hyperintense Vessels Are Associated with Cognitive-Attentional Impairment and Discharge
Derek A Tsang1, Karthik Lalwani1, Mona Gad1
1From the Department of Radiology (D.A.T., K.L., M.G., N.L., J.M.,N.H., C.G., C.A., V.S.Y.), Division of Neuroradiology, Johns Hopkins Medical Center, Baltimore, Maryland, USA; Tehran University of Medical Science (I.K.), Tehran, Iran; Department of Neuroradiology (D.A.L.), Rockefeller Neuroscience Institute, West Virginia University, Morgantown, WV, USA; Department of Neuroradiology (H.A.S.), MD Anderson Medical Center, Houston, TX, USA; Neuroendovascular Program (A.A.D.), Massachusetts General Hospital & Brigham and Women's Hospital, Harvard Medical School, Boston, MA, USA; Neurovascular Centre & RADIS Lab (A.A.D.), St. Michael's Hospital, Toronto Metropolitan University, Toronto, ON; Université Libre de Bruxelles (A.G.), Bruxelles, Belgium; University of Cincinnati Medical Center (A.S.), Cincinnati, Ohio; Cooper Neurological Institute (M.K.), Cooper University, Camden, NJ, USA and University of Michigan Health (G.S.), Ann Arbor, MI, USA.

Purpose:
Persistent FLAIR hyperintense vessels (FHV) after endovascular thrombectomy (EVT) may reflect residual impaired perfusion, collateral dysfunction, or no-reflow physiology despite macrovascular treatment. We evaluated whether post-EVT FHV presence was associated with cognitive-attentional impairment and discharge functional outcome in patients with ICA, M1, or M2 occlusions treated with EVT.
Methods:
This retrospective cohort study included patients with acute ischemic stroke due to ICA, M1, or M2 occlusion who underwent EVT and posttreatment MRI. FHV was assessed on posttreatment FLAIR using the NIH-FHV score and dichotomized as absent (score 0) versus present (score >0). Final infarct volume was measured on follow-up DWI. Primary outcomes were Cog-4, a summed NIHSS-derived score used as a rapid proxy for early poststroke cognitive-attentional dysfunction, and discharge modified Rankin Scale (mRS). Multivariable linear regression was used for Cog-4, and ordinal logistic regression was used for discharge mRS, adjusting for follow-up DWI infarct volume, age, admission NIHSS, ASPECTS, intravenous thrombolysis, successful reperfusion, and occlusion laterality.
Results:
Among 212 patients in the complete-covariate cohort, 71 were FHV positive and 141 were FHV negative. FHV-positive patients had higher follow-up DWI infarct volume, lower successful reperfusion rates, worse Cog-4 scores, and less favorable discharge mRS distributions. In adjusted analyses, FHV presence was independently associated with higher Cog-4 score (β = 0.97; 95% CI, 0.36-1.57; P = .002) and worse discharge mRS (OR = 1.79; 95% CI, 1.03-3.12; P = .04). In secondary analyses, increasing NIH-FHV score was also associated with higher Cog-4 score (β = 0.42 per 1-point increase; 95% CI, 0.23-0.62; P < .001) and worse discharge mRS (OR = 1.24 per 1-point increase; 95% CI, 1.04-1.48; P = .02).
Conclusion:
Post-EVT FHV presence and greater NIH-FHV burden were associated with worse Cog-4 performance, used here as a rapid proxy for early poststroke cognitive-attentional dysfunction, and worse discharge disability after ICA/M1/M2 EVT. These findings suggest that persistent FHV may provide outcome-relevant posttreatment MRI information beyond final infarct volume and angiographic reperfusion.
Related Concept Videos
 01:15
Ischemic Stroke l: Introduction
 01:15
Ischemic Stroke ll: Pathophysiology
 01:26
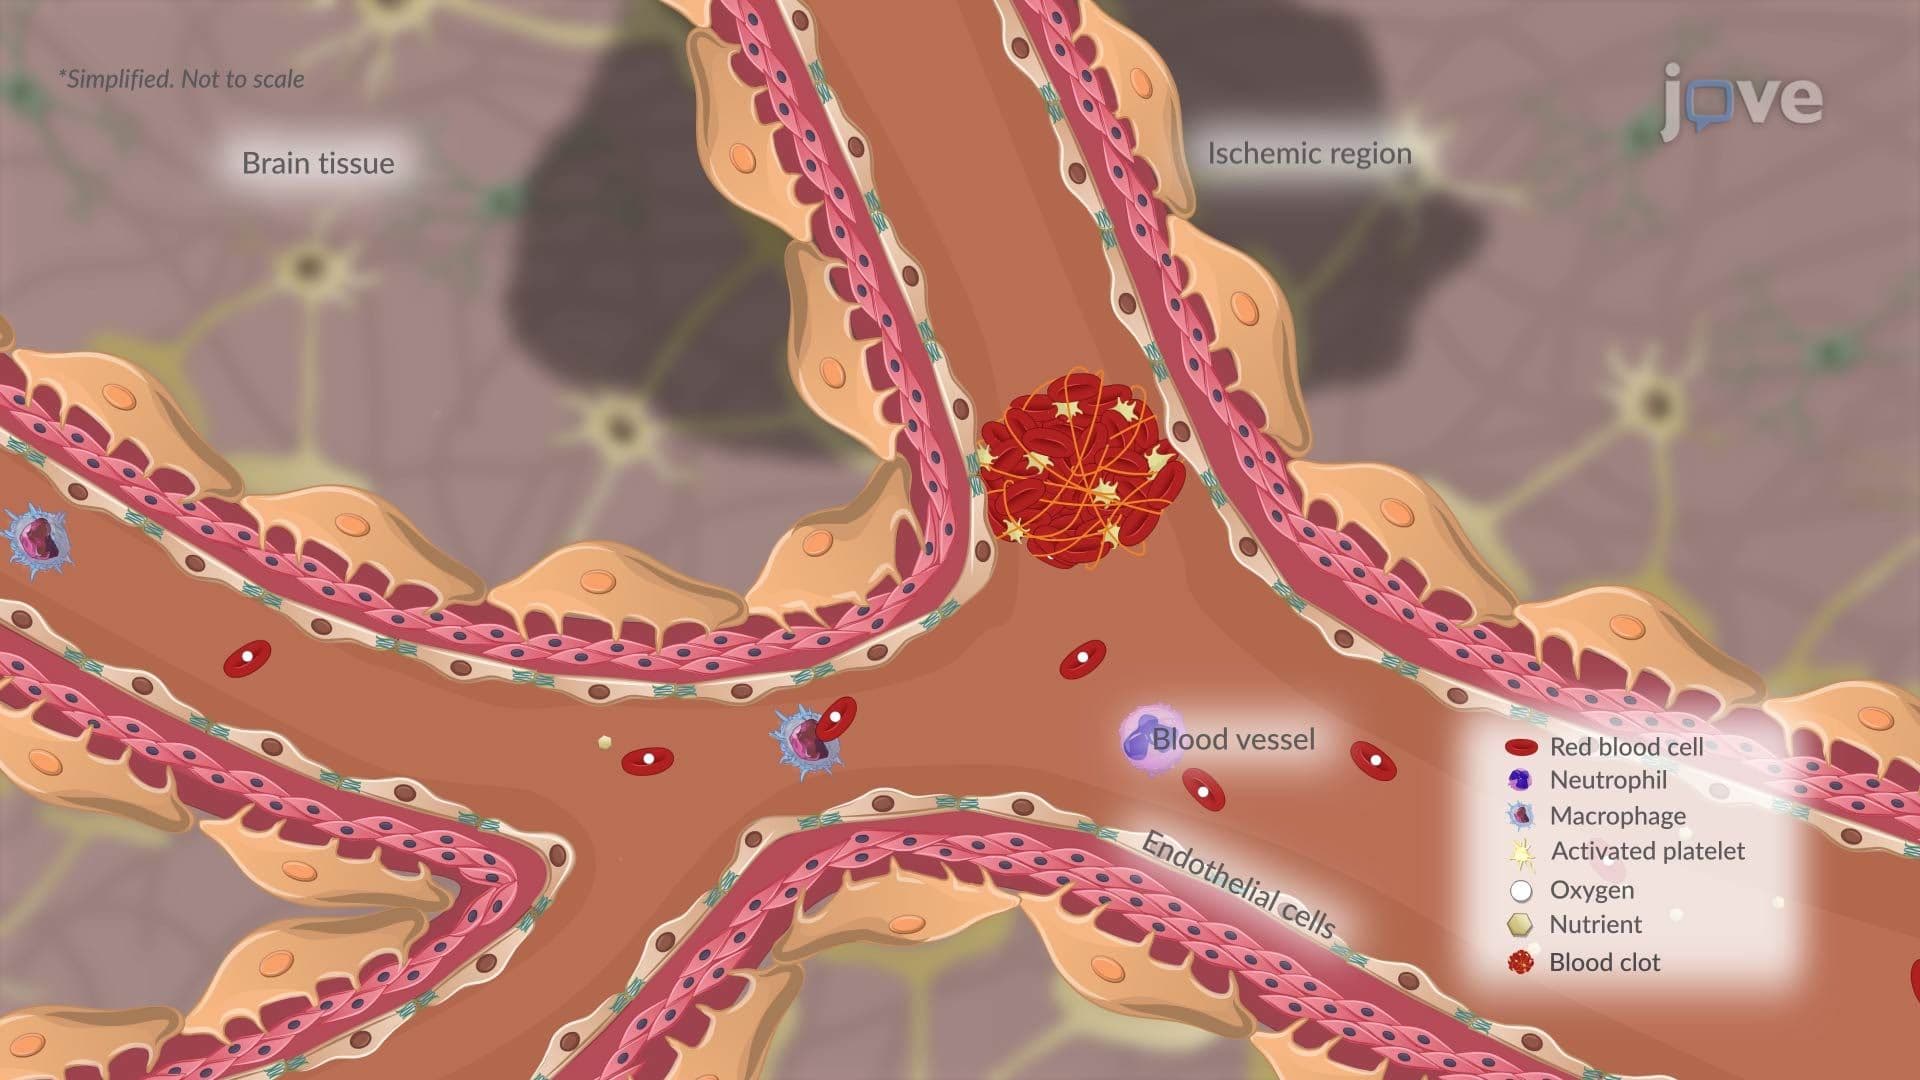
Transient Ischemic Attack l: Introduction