Related Experiment Videos
Analysis of risk factors for multidrug-resistant bacterial infections in intensive care units and application of a
Yi Fu1, Xing-Ran Zhao, Jian-Jun Luo
1Leshan People's Hospital, Leshan, Sichuan, China.

Abstract:
Multidrug-resistant (MDR) bacterial infections remain a major challenge in intensive care units, leading to prolonged hospitalization and increased mortality. Although several clinical factors have been associated with MDR infections, there is still a lack of practical and individualized predictive tools to facilitate early risk stratification in intensive care unit (ICU) patients. This retrospective single-center study included adult patients admitted to the ICU of Leshan People's Hospital between January 2020 and December 2025 who stayed for at least 48 hours and had complete microbiological records. The primary outcome was the occurrence of MDR bacterial infection, defined as resistance to at least 3 classes of antibiotics confirmed by microbiological culture and susceptibility testing. Patients were randomly divided into a training cohort (70%) and a validation cohort (30%). Univariable and multivariable logistic regression analyses were performed to identify independent risk factors. A nomogram prediction model was constructed based on significant predictors. Model performance was evaluated using receiver operating characteristic curves, area under the curve (AUC), calibration curves, the Hosmer-Lemeshow goodness-of-fit test, decision curve analysis, and internal validation using Bootstrap resampling combined with 10-fold cross-validation. A total of 876 ICU patients were included (mean age: 68.4 ± 14.7 years; 58.2% male), among whom 161 (18.38%) developed MDR bacterial infections. Multivariable logistic regression identified age > 75 years (OR: 3.350, 95% CI: 2.916-3.792), endotracheal intubation (OR: 2.079, 95% CI: 1.740-3.130), ICU stay > 1 week (OR: 3.428, 95% CI: 2.553-4.417), coma (OR: 2.735, 95% CI: 2.000-4.469), and central venous catheterization (OR: 2.438, 95% CI: 1.464-4.295) as independent risk factors. The nomogram demonstrated good discriminative ability, with an AUC of 0.827 in the training cohort and 0.812 in the validation cohort. Internal validation yielded an AUC of 0.820, with a sensitivity of 83.2% and a specificity of 82.8%. Advanced age, invasive procedures, prolonged ICU stay, and impaired consciousness are associated with an increased risk of MDR bacterial infections in ICU patients. The developed nomogram provides a practical tool for individualized risk prediction and may assist clinicians in early identification and targeted preventive strategies. However, due to the retrospective nature of the study, these findings suggest associations but do not establish causality.
Insights
Multidrug-resistant bacterial infections pose a significant threat in intensive care units. A new nomogram model effectively predicts patient risk, aiding early intervention strategies for these challenging infections.
Area of Science:
- Medical Microbiology
- Infectious Diseases
- Critical Care Medicine
Background:
- Multidrug-resistant (MDR) bacterial infections are a critical concern in intensive care units (ICUs), contributing to increased mortality and prolonged hospital stays.
- Existing clinical factors for MDR infections lack practical, individualized predictive tools for early risk stratification in ICU patients.
Purpose of the Study:
- To develop and validate a nomogram prediction model for early risk stratification of multidrug-resistant bacterial infections in intensive care unit patients.
- To identify independent risk factors associated with the development of MDR bacterial infections in the ICU.
Main Methods:
- Retrospective single-center study of 876 adult ICU patients (January 2020-December 2025).
- Patients divided into training (70%) and validation (30%) cohorts.
- Multivariable logistic regression and nomogram construction, with performance evaluated using ROC curves, AUC, calibration, and internal validation.
Main Results:
- 18.38% of patients developed MDR bacterial infections.
- Independent risk factors identified: age > 75 years, endotracheal intubation, ICU stay > 1 week, coma, and central venous catheterization.
- The nomogram showed good discriminative ability (AUC 0.827 training, 0.812 validation) and internal validation (AUC 0.820).
Conclusions:
- Advanced age, invasive procedures, prolonged ICU stay, and impaired consciousness are associated with increased risk of MDR infections in ICU patients.
- The developed nomogram serves as a practical tool for individualized risk prediction, assisting clinicians in early identification and targeted prevention.
- Findings suggest associations, but causality requires further investigation due to the study's retrospective nature.
Related Concept Videos
 01:23
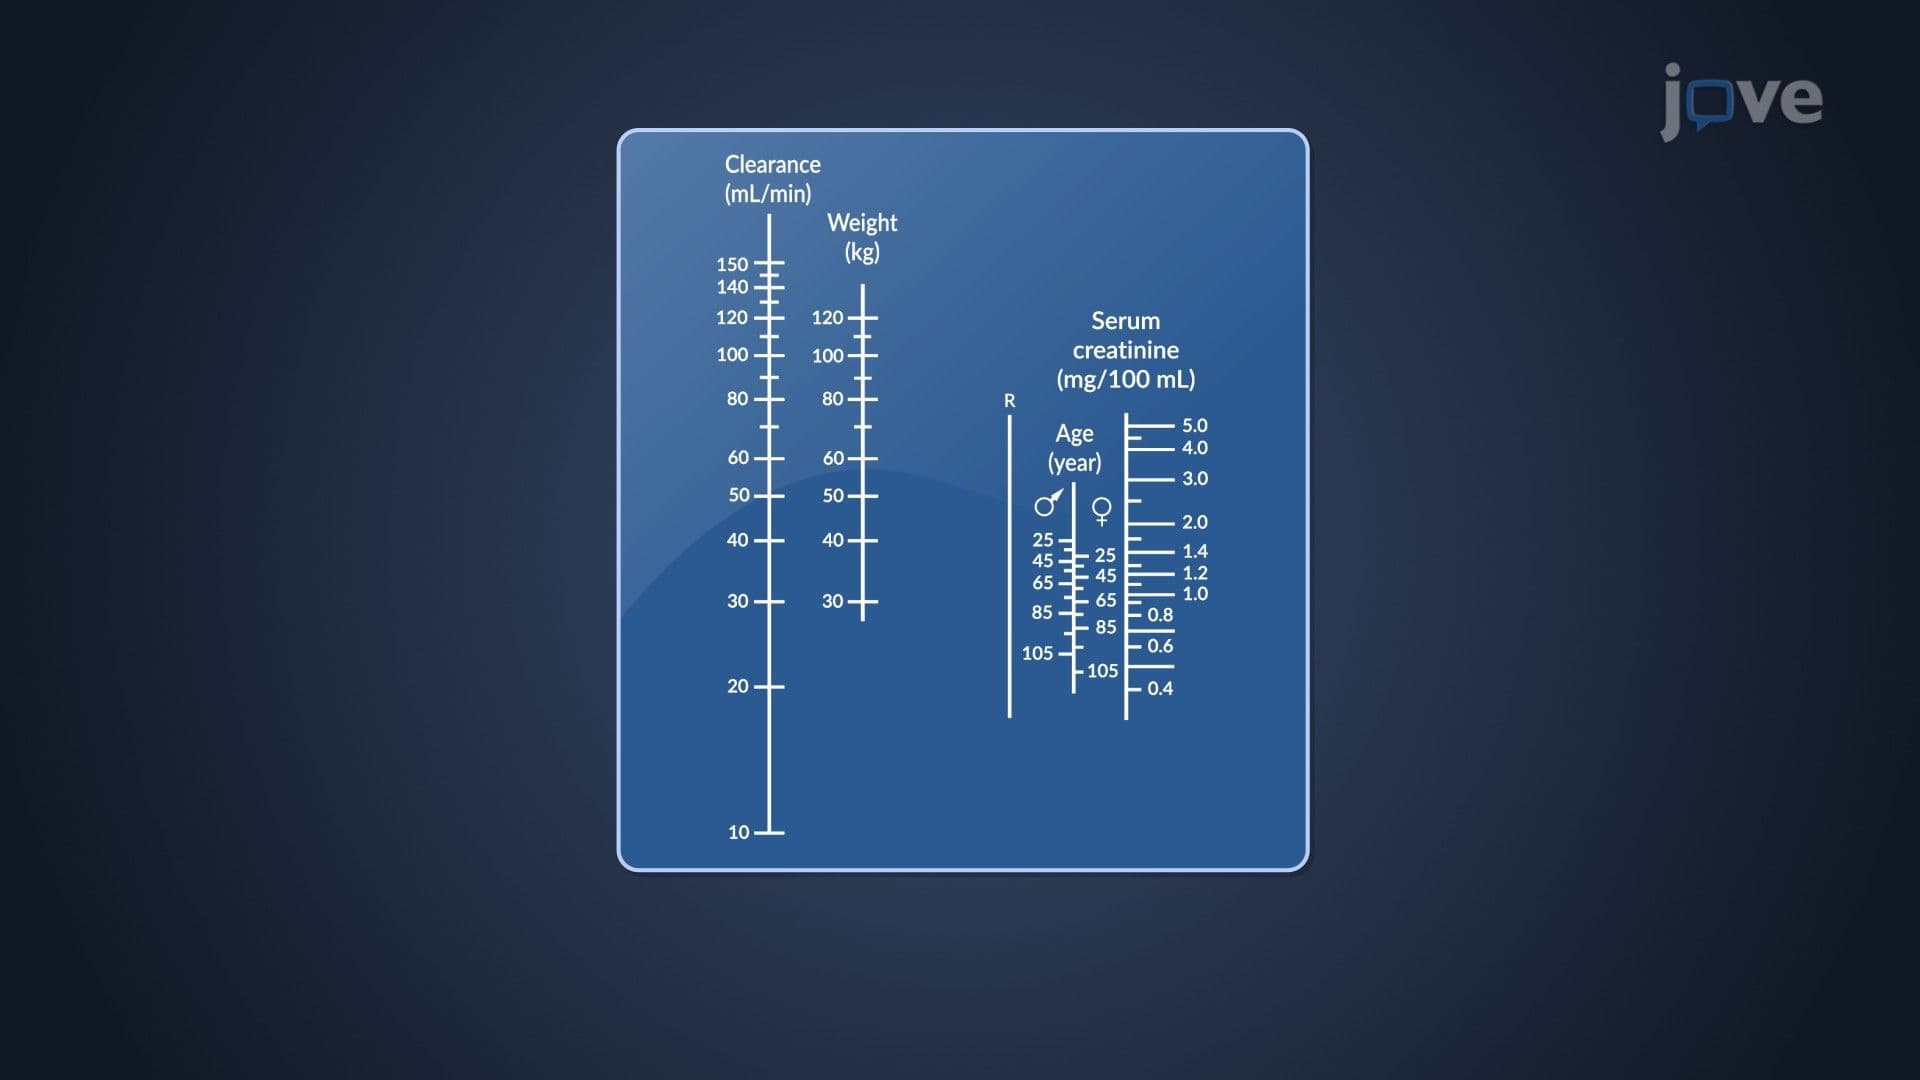
Dosage Regimen Designs: Nomograms and Tabulations
 01:27
Pharmacodynamic Models: Overview
 01:15
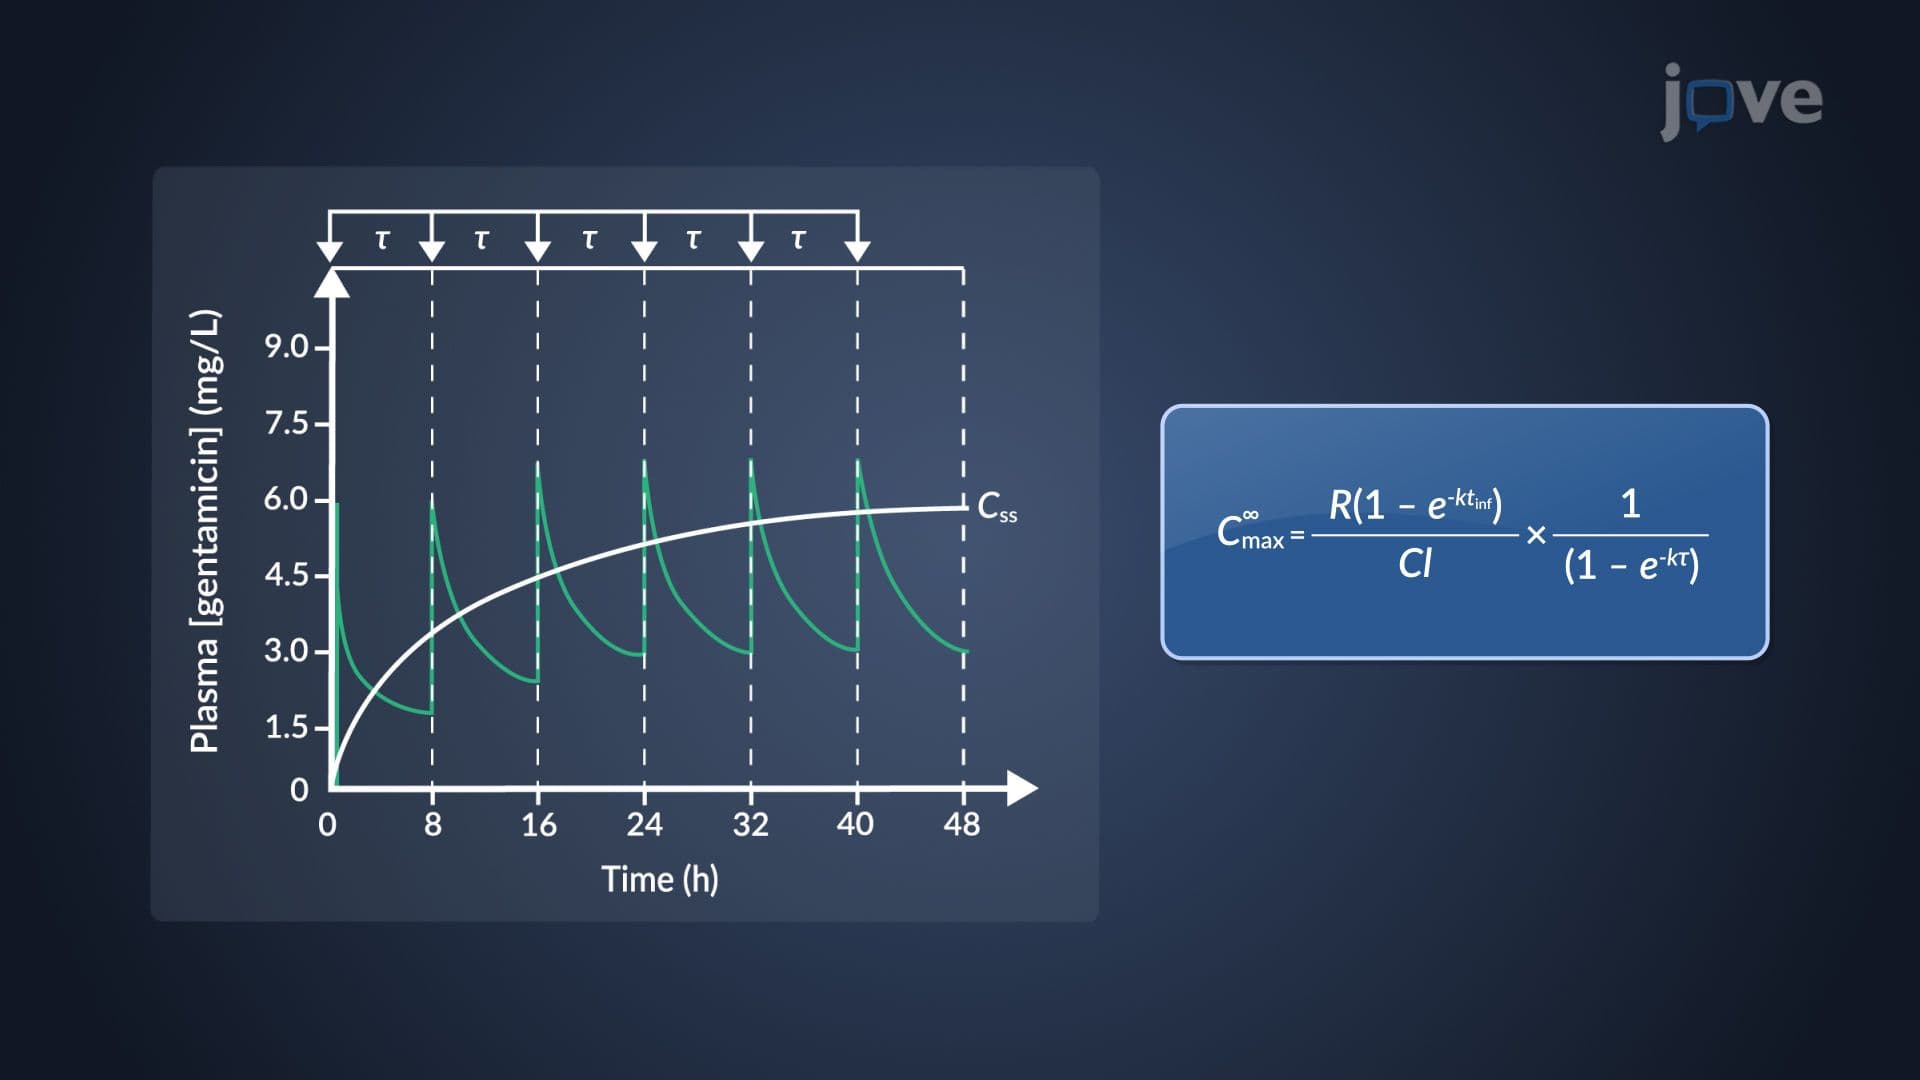
Determination of Multiple Dosing Parameters: Steady-State, Minimum and Maximum Concentrations
 01:15
Impact of Pharmacokinetic–Pharmacodynamic Models: Regulatory Decisions