Related Experiment Video
Updated: Aug 6, 2026
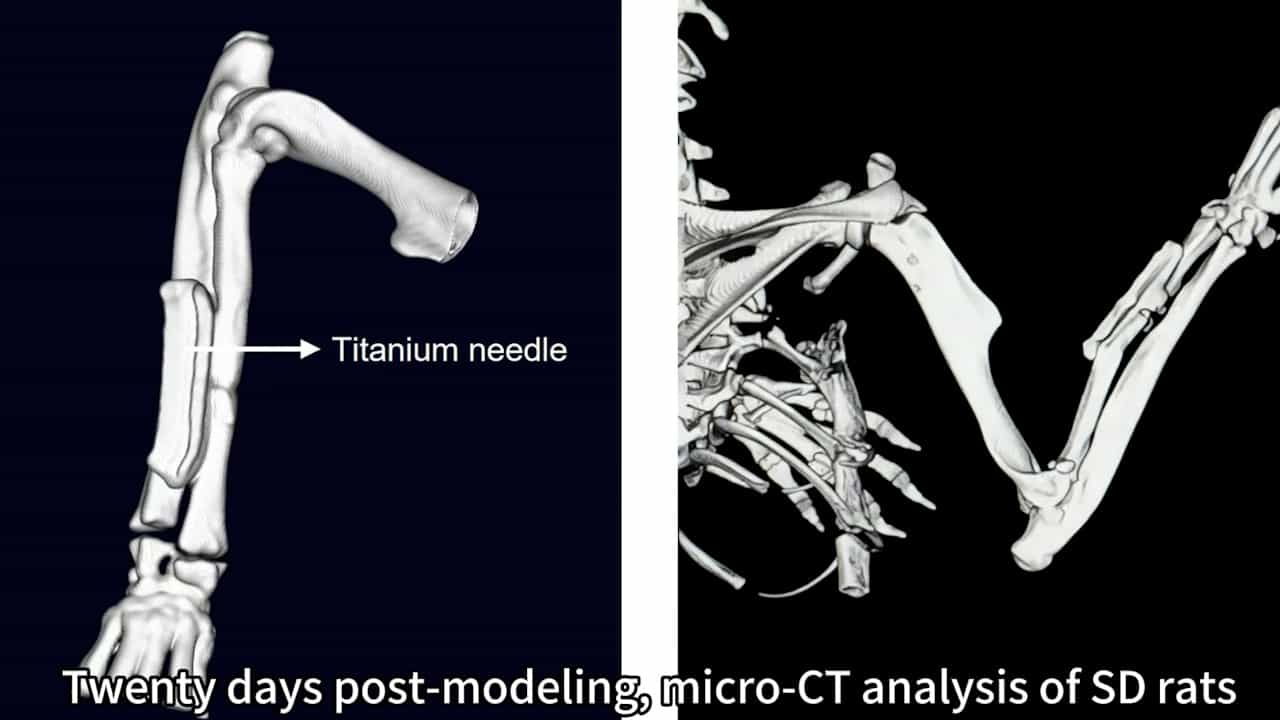
Development of a Novel Internal Fixation Model for Rat Radial Fractures: Fracture Healing Assessment and Dorsal Root Ganglion Isolation
Published on: March 13, 2026
Complications and risk factors following volar locking plate fixation of distal radius fractures: A 2-institution
Xiong Zhang1, Xiaocong Zhou2, Weijiang Bai2
1Department of Orthopedic Surgery, The First Hospital of Hebei Medical University, Shijiazhuang, Hebei, China.

Abstract:
Distal radius fractures are among the most common skeletal injuries and are increasingly treated with volar locking plate (VLP) fixation. Despite its widespread use, postoperative complications remain a significant concern. This study aimed to determine the incidence and spectrum of complications following VLP fixation and to identify independent predictors in a 2-institution cohort. Adult patients who underwent VLP fixation for acute distal radius fractures at 2 tertiary centers between January 2022 and June 2024 were retrospectively reviewed. Inclusion criteria involved operation within 3 weeks of injury and at least 12 months of follow-up. Demographic, clinical, fracture-related, perioperative, and surgeon-related variables were collected from electronic medical records. Complications were defined using standardized criteria and classified as major (requiring reoperation/implant removal) or minor (managed conservatively). Risk factors were evaluated using univariate and multivariate logistic regression. Of 1147 screened patients, 924 met eligibility criteria. Complications occurred in 116 patients (12.6%), comprising 145 events, with 3.6% major and 9.0% minor complications. The most common events were wound problems (21.9%), carpal tunnel syndrome (15.1%), and tendon irritation/rupture (12.3%). Independent predictors included chronic obstructive pulmonary disease (odds ratio [OR]: 2.25, 95% confidence interval [CI]: 1.12-5.62), osteoporosis (OR: 2.03, 95% CI: 1.68-2.43), Association for the Study of Internal Fixation type C fractures versus type A (OR: 1.97, 95% CI: 1.48-2.65), lunate facet collapse ≥5 mm (OR: 3.29, 95% CI: 1.26-7.91), and increased intraoperative blood loss (per 10-mL increment, OR: 1.12, 95% CI: 1.04-1.22). Our findings demonstrate that comorbidities, fracture complexity, and intraoperative factors independently increase complication risk. Individualized perioperative care and meticulous surgical planning may reduce morbidity and improve outcomes in high-risk patients.

