Related Experiment Video
Updated: Aug 6, 2026
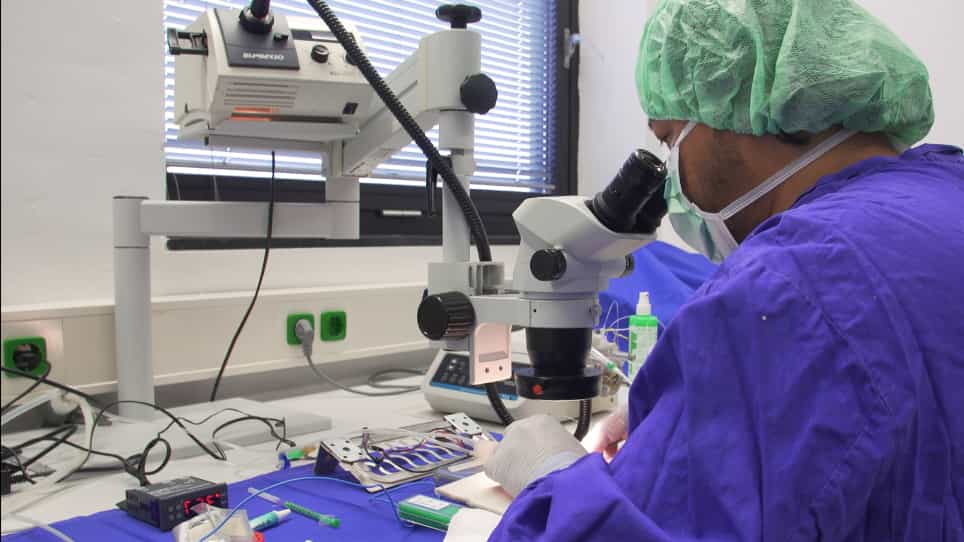

Veno-Venous Extracorporeal Membrane Oxygenation in a Mouse
Published on: October 24, 2018
Hemoperfusion during extracorporeal membrane oxygenation: an updated systematic review and meta-analysis of 8,151
Ting Xie1,2,3, Chengyi Yang1,2,4,3, Heng Tao1,2,4,3
1Intensive Care Unit, Department of Emergency Medicine, Sichuan Provincial People's Hospital, Affiliated Hospital of University of Electronic Science and Technology of China, Chengdu, China.

Background:
This systematic review and meta-analysis evaluated the clinical efficacy and safety of hemoperfusion in adults receiving extracorporeal membrane oxygenation (ECMO).
Methods:
We systematically searched PubMed, Embase, the Cochrane Library, CNKI, and CBM for studies comparing ECMO plus hemoperfusion (ECMO + HP) with ECMO alone in adult patients. The primary outcome was all-cause mortality. Prespecified subgroup analyses were conducted according to study design (RCT vs non-RCT), ECMO type (VA vs VV), and etiology (cardiogenic shock vs cardiac arrest). Risk of bias was assessed using RoB 2.0 and ROBINS-I, and Trial Sequential Analysis (TSA) was performed. The systematic review was registered with PROSPERO (CRD42025643149) and conducted in accordance with PRISMA guidelines.
Results:
Thirteen studies involving 8,151 patients were included, comprising three RCTs and ten non-RCTs. Overall, ECMO + HP did not significantly reduce all-cause mortality compared with ECMO alone (OR 0.98, 95% CI 0.49-1.94; P = 0.95; I2 = 76%). However, mortality was higher with ECMO + HP in RCTs (OR 4.96, 95% CI 1.67-14.77; P = 0.004; I2 = 34%), whereas no significant difference was observed in non-RCTs (OR 0.58, 95% CI 0.25-1.33; P = 0.20; I2 = 79%). Subgroup analyses by ECMO type showed no survival benefit with either VA-ECMO (OR 0.80, 95% CI 0.41-1.58; P = 0.53; I2 = 47%) or VV-ECMO (OR 1.23, 95% CI 0.30-4.99; P = 0.77; I2 = 77%). Among VA-ECMO patients, etiology-based analyses showed no mortality benefit in cardiogenic shock (OR 0.58, 95% CI 0.31-1.09; P = 0.09; I2 = 22%) or cardiac arrest (OR 2.42, 95% CI 0.71-8.25; P = 0.16; I2 = 26%). No significant differences were identified in other clinical outcomes or complications, and TSA indicated that the evidence remains insufficient to confirm a mortality benefit. Most studies were at moderate to serious risk of bias.
Conclusion:
In patients receiving extracorporeal membrane oxygenation, hemoperfusion did not reduce mortality and may be associated with increased mortality in randomized controlled trials. Current evidence does not support routine use of ECMO + HP in ICU condition.