Related Experiment Video
Updated: Aug 6, 2026
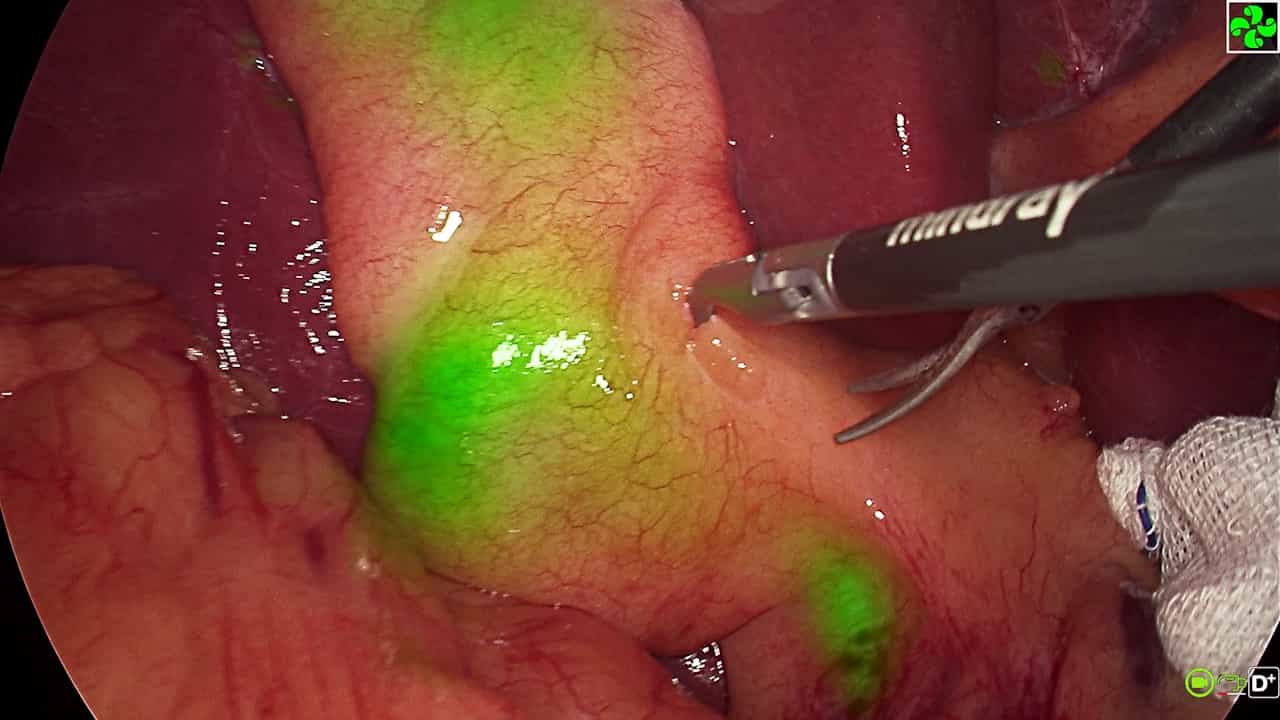

Laparoscopic Cholecystectomy with Indocyanine Green Fluorescence: Choledochoscopic Stone Extraction and Primary Duct Suture
Published on: November 25, 2025
Association Between Intraoperative Cholangiogram Use and Cholecystectomy Outcomes
Cody Lendon Mullens1,2,3, Joshua K Sinamo2, Scott C Levy1,2
1Department of Surgery, University of Michigan. Ann Arbor, MI.

Background:
Intraoperative cholangiography (IOC) is widely used during cholecystectomy to define biliary anatomy and potentially reduce bile duct injury (BDI), yet substantial surgeon-level variation in IOC use persists and its association with postoperative outcomes remains uncertain.
Study Design:
We performed a retrospective cohort study of Medicare fee-for-service beneficiaries undergoing inpatient minimally invasive cholecystectomy from 2011-2023. Surgeons were classified by IOC utilization as never (0%), selective (>0% to <90%), or routine (≥90%). The primary outcome was BDI requiring operative repair within 1 year. Secondary outcomes included postoperative endoscopic retrograde cholangiopancreatography (ERCP), perioperative complications, length of stay, readmission, and mortality. Multivariable regression adjusted for patient characteristics and secular trends.
Results:
Among 434,696 beneficiaries (mean age 74.7 ± 9.8 years; 52.0% female), 81.0% were treated by selective IOC users, 11.4% by never users, and 7.6% by routine users. Adjusted BDI rates were low and did not differ significantly across IOC-use groups. In contrast, adjusted postoperative ERCP utilization increased progressively with greater IOC use (8.1% for never, 10.4% for selective, and 12.0% for routine users; all p<0.001).
Conclusions:
Greater surgeon-level IOC utilization was associated with increased downstream ERCP use without measurable differences in BDI requiring operative repair. These findings suggest that variation in IOC practice may reflect differences in intervention thresholds rather than injury prevention and have implications for operative decision-making, resource utilization, and surgical training.