Related Experiment Video
Updated: Aug 6, 2026
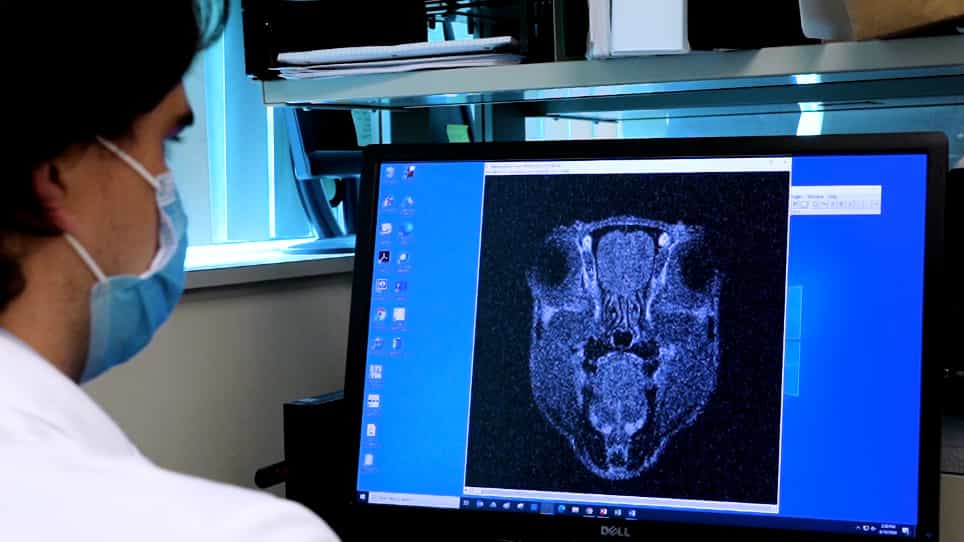
Modeling Brain Metastases Through Intracranial Injection and Magnetic Resonance Imaging
Published on: June 7, 2020
Clinical and molecular features of resected breast cancer brain metastases: a single center retrospective cohort
Nira A Krasnow1, Mia Salans2, Michelle Jayaraj3
1Department of Medicine, University of California, San Francisco, CA, USA.

Purpose:
To characterize clinical and molecular characteristics and prognosis among patients with metastatic breast cancer (MBC) who undergo brain metastasis (BM) resection.
Methods:
We retrospectively identified patients with MBC who underwent BM resection from 2006 to 2024 at a single center. Chart abstraction was utilized to identify key demographic, treatment, and outcome data. Median real-world overall survival (mrwOS) was estimated with the Kaplan-Meier method; the Cox proportional hazards model evaluated factors associated with mrwOS.
Results:
107 patients were identified with the following MBC subtypes: hormone receptor-positive (HR+), HER2-negative (HER2-) (n = 26, 24.3%), HER2+ (n = 45, 42.1%), and triple-negative (TNBC; n = 36, 33.6%). At time of initial BM surgical resection, 55 patients (51.4%) had CNS-only disease and 63 patients (58.9%) had a single BM. Most patients received systemic therapy after BM resection (n = 83/95 with available systemic therapy records, 87.4%) and postoperative radiation (n = 92/103 with available post-operative radiation records, 89.3%). Among patients with available BM receptor status (n = 92), 25 (27.2%) had receptor discordance between BM and peripheral tissue testing, mostly loss of BM HR-positivity (n = 20/92, 21.7%). Among patients with available BM NGS testing (n = 40), the most common pathogenic alterations were TP53 mutation (n = 28, 70.0%), ERBB2 amplification (n = 15, 37.5%), and PIK3CA mutation (n = 9, 22.5%); 31 patients (77.5%) had therapeutically targetable mutations. mrwOS from BM resection was longer for patients with HR+/HER2- and HER2+ MBC vs. TNBC (40.3 and 37.8 months vs. 12.6 months, p = 0.04 and p = 0.02 respectively). On multivariate analysis, receipt of systemic therapy (HR 0.09, CI 0.04-0.21, p < 0.01) and stereotactic radiosurgery (SRS) (HR 0.41, CI 0.18-0.97, p = 0.04) post-operatively were associated with longer mrwOS. Extracranial disease at time of resection (HR 4.60, CI 2.52-8.39, p < 0.01) and development of leptomeningeal disease (LMD) (HR 6.08, CI 3.00-12.31, p < 0.01) were associated with shorter mrwOS.
Conclusions:
Survival after BM resection was ~3 years in patients with HR+/HER2- and HER2+ MBC and ~1 year in patients with TNBC. Extracranial disease at time of BM resection and development of LMD were associated with worse prognosis. Loss of HR-positivity and targetable mutations were present in ~22% and ~75% of resected BMs, respectively, supporting the utility of molecular analysis of resected BMs to guide management.
