Related Experiment Video
Updated: Aug 6, 2026
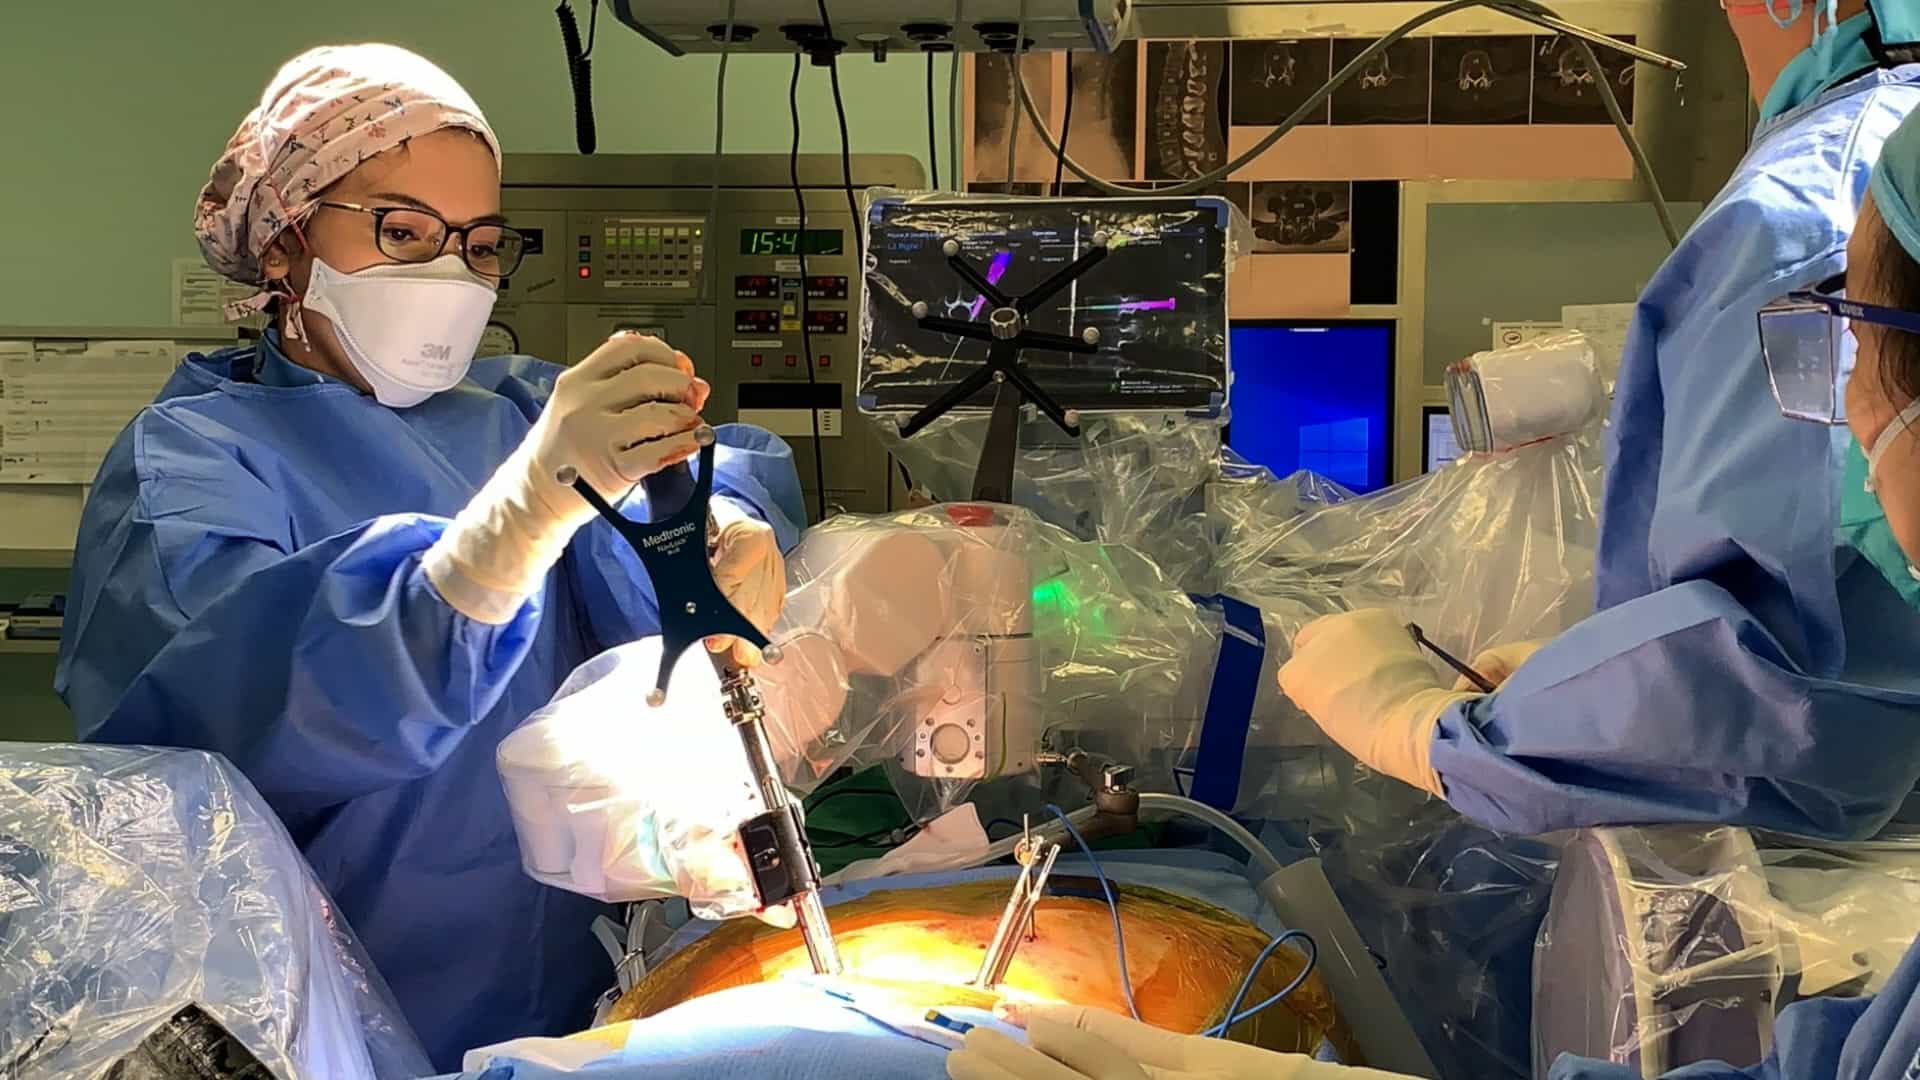

Multilevel Oblique Lumbar Interbody Fusion in Degenerative Lumbar Disc Disease with Instability
Published on: July 25, 2025
Low dose rhBMP-2 use in three- and four-level ACDF without posterior fusion: a comparative analysis and viable
David Cowan1, Aubrie M Sowa1, Stephen R Barchick1
1Department of Orthopaedic Surgery, Emory University School of Medicine, 21 Ortho Lane, Atlanta, GA 30329, USA.

Background Context:
Pseudarthrosis is a known complication following multilevel anterior cervical discectomy and fusion (ACDF), yet data remain limited on its incidence and risk factors in multilevel procedures in the modern era.
Purpose:
This study aimed to characterize the incidence of pseudarthroses and identify associated risk factors in patients undergoing three- or four-level ACDF procedures without posterior fixation, while also evaluating the potential role of low-dose rhBMP-2 in promoting fusion and supporting anterior-only surgical strategies.
Study Design:
Retrospective single-center observational cohort study.
Patient Sample:
Two hundred and six patients treated by three- or four-level ACDF.
Outcome Measures:
Radiological records, including independent review of interspinous motion, Cobb angle, bony bridging, and fusion rate, were collected. Surgical-related information and complications were also recorded.
Methods:
A retrospective review of adults who underwent three- or four-level ACDF with anterior plating between 2011 and 2024 was performed at a single academic institution. Patients were excluded if follow-up imaging was <12 months or if they had a prior cervical procedure, corpectomy, or combined anterior-posterior surgery. Demographic, surgical details, and outcome data were collected. Pseudarthrosis was assessed using dynamic flexion-extension radiographs evaluating interspinous motion and change in Cobb angle. When flexion-extension imaging was not available, fusion status was evaluated using static radiographs and/or computed tomography. The primary outcome measure was fusion status at 1 year. Secondary outcome measures were postoperative complications, readmission, and reoperation rates. Continuous variables were reported as median (interquartile range) and compared using the Wilcoxon rank-sum test. Categorical variables were presented as percentages and compared using Pearson's chi-square or Fisher's exact tests when cell counts were low. Multivariable logistic regression was performed to identify independent predictors of outcome variables.
Results:
A total of 206 patients were included (median age 57 [51-66] years; 59.7% female; 66.0% White). Most underwent three-level fusion (85.9%), and recombinant human bone morphogenetic protein (rhBMP-2) was used in 48.5%. In total, pseudarthroses occurred in 28 patients (13.6%), with 13 (6.3%) patients having symptomatic pseudarthrosis. Pseudarthroses occurred in 13.0% (n=23) of three-level constructs versus 17.2% (n=5) of four-level constructs (p=.56). Pseudarthrosis rates did not vary significantly by implant type. Patients with any smoking history had higher pseudarthrosis rates compared with nonsmokers (23.3% vs. 6.7%, p<.001). Among patients with any smoking history, rhBMP-2 was significantly associated with reduced pseudarthrosis incidence (14.0% vs. 36.1%, p=.017). Among all patients, multivariable logistic regression identified rhBMP-2 use as independently protective of pseudarthrosis (odds ratio=0.15, 95% confidence interval 0.04-0.55, p=.004). However, rhBMP-2 was identified as an independent predictor of increased complication rates (odds ratio=2.70, 95% confidence interval 1.01-7.16, p=.047), with transient dysphagia being the most frequent complication (n=15, 93.8%).
Conclusions:
Three- and four-level ACDF without posterior fusion demonstrated much lower nonunion rate compared to historic and recently reported rates, with pseudarthroses occurring in 13.6% of patients and symptomatic pseudarthroses occurring in 6.3% of patients. Among all patients, rhBMP-2 use was associated with 6.7-fold lower odds of pseudarthrosis. Smoking history was strongly associated with nonunion, and rhBMP-2 use appeared to mitigate this risk among smokers. These findings support individualized fusion strategies and selective use of biologic augmentation in high-risk patients.