Related Experiment Video
Updated: Aug 6, 2026


Robot-assisted Total Mesorectal Excision and Lateral Pelvic Lymph Node Dissection for Locally Advanced Middle-low Rectal Cancer
Published on: February 12, 2022
Operative Approach for Robotic Descending Colon Cancer Requiring Bidirectional Mobilization of the Splenic Flexure
Tsutomu Kumamoto1, Koki Otsuka2, Junichiro Hiro1
1Department of Surgery, Fujita Health University, Toyoake, Japan.

Introduction:
Robotic Descending Colectomy Occasionally Requires Splenic Flexure (SF) and Sigmoid-Descending Junction (SDJ) Mobilization. In Multiport Robotic Surgery, This Bidirectional Mobilization Can Be Technically Demanding Because the Operative Field Extends in Two Directions, and Conventional Curved-Line or Stepped-Line Configurations May Limit Operative Envelope or Cause Arm Interference.
Materials And Surgical Technique:
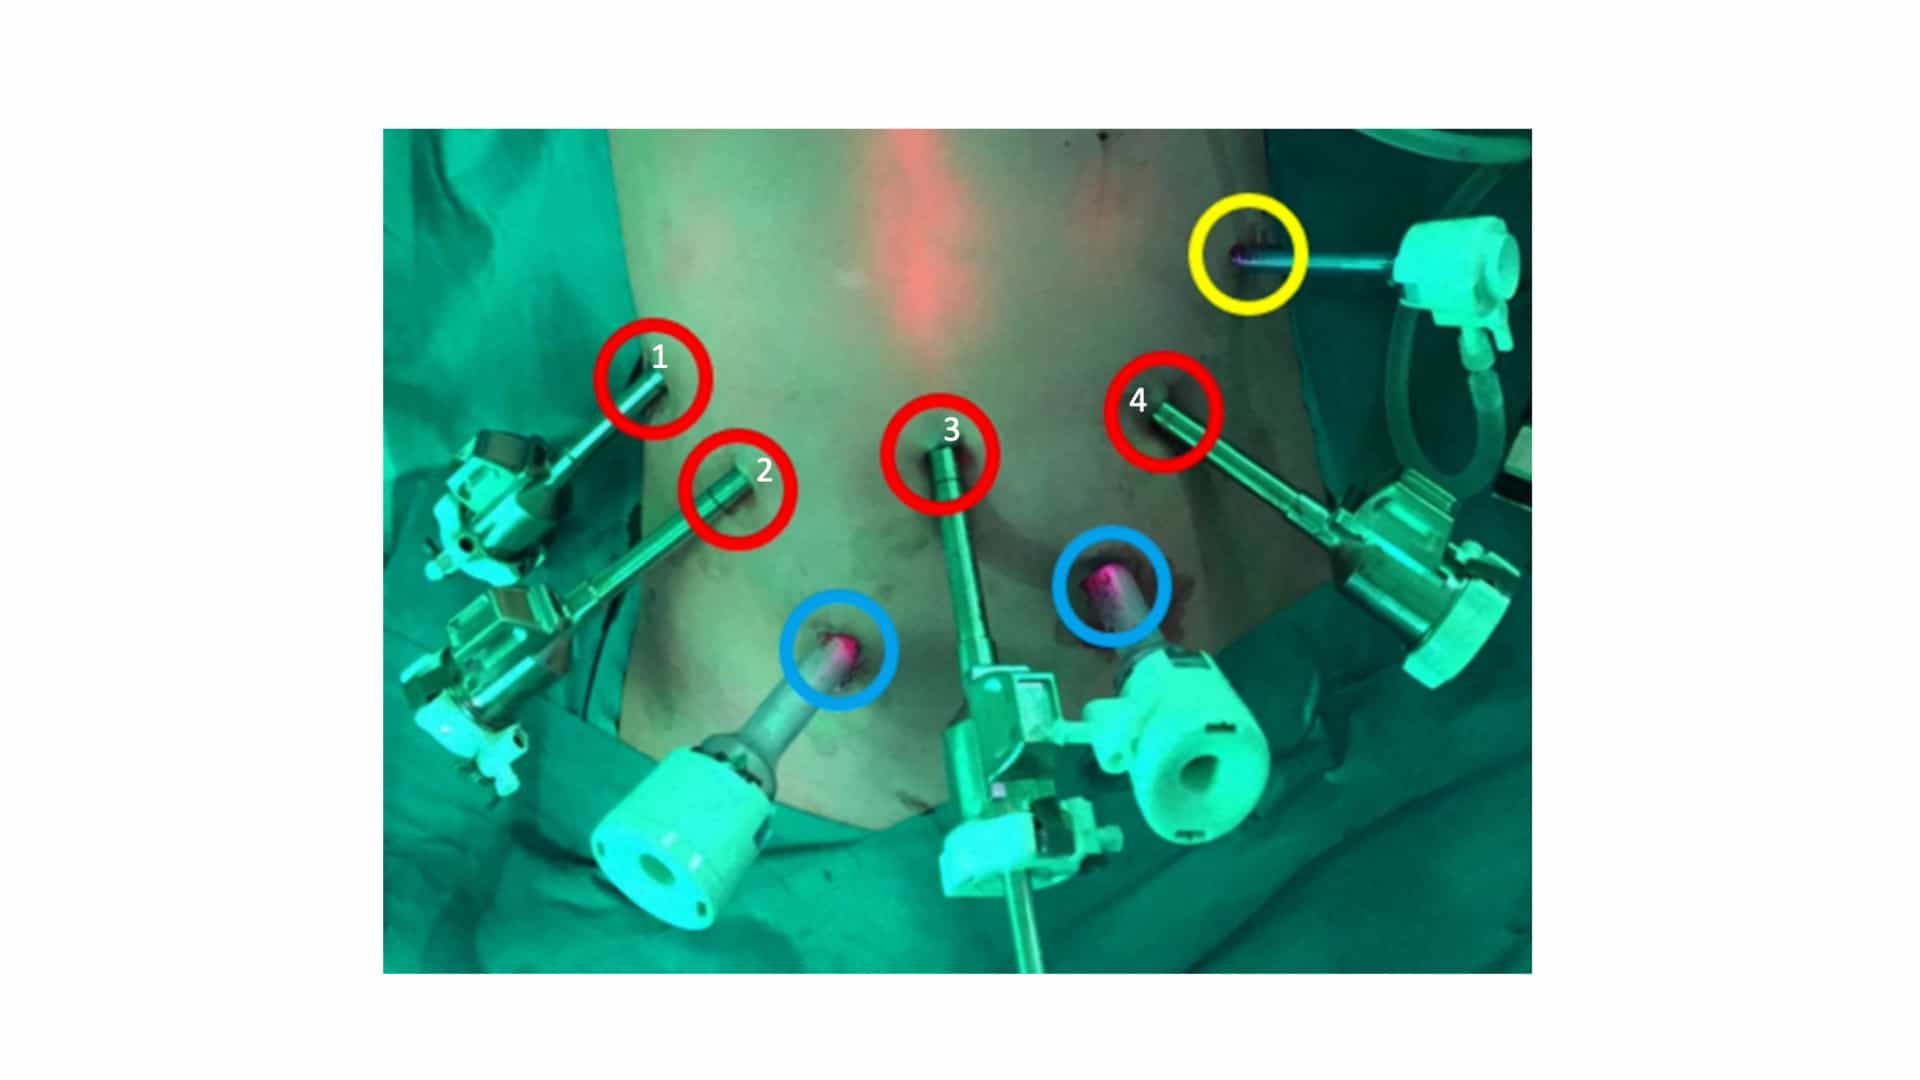
For lesions requiring continuous SF-SDJ access, an oblique-line configuration using the da Vinci Xi (DVXi) or the da Vinci SP (DVSP) system is typically required for an adequate operative envelope. This study describes the selection and use of curved-line, stepped-line, and oblique-line DVXi port configurations, with the DVSP system as a complementary option, based on lesion location and required mobilization direction. In the oblique-line configuration, the robotic ports are arranged diagonally from the right side of the round ligament of the liver toward the lower abdominal midline.
Discussion:
The Oblique-Line Configuration Is Designed to Align the Camera Axis and Working Instruments With the Anticipated Direction of Mobilization, Whereas the DVSP System Provides Flexible Access Across Proximal and Distal Operative Fields. These Strategies May Help Surgeons Gain Stable Robotic Access Without Additional Port Insertion, Redocking, or Excessive Instrument Angulation.