Related Experiment Videos
Appendiceal-source Klebsiella pneumoniae iliac pseudoaneurysm with rupture risk: a three-case series highlighting
Bingjing Chen1, Jingyu Ji1, Yiqing Li1
1Department of Vascular Surgery, Union Hospital, Tongji Medical College, Huazhong University of Science and Technology, Wuhan, China.

Background:
Infective native aorto-iliac aneurysms and pseudoaneurysms are uncommon but life-threatening vascular infections. In rupture-prone presentations, emergency endovascular aneurysm repair (EVAR) may be required to reduce the immediate risk of hemorrhage, but technical exclusion of the aneurysm does not establish infection control.
Case Presentation:
We report three patients with rupture or impending rupture of infective native aorto-iliac aneurysms who underwent emergency EVAR followed by post-procedural reassessment for residual infection. Case 1 was a 66-year-old woman with type 2 diabetes who presented with lower abdominal pain, leukocytosis, elevated C-reactive protein, and a gas-containing left common iliac pseudoaneurysm. Blood anaerobic culture grew Klebsiella pneumoniae with susceptibility to imipenem, meropenem, ceftazidime, cefoperazone-sulbactam, and ceftazidime-avibactam, while urine cultures were negative. Although endovascular exclusion was technically successful, persistent inflammatory signals prompted reassessment and subsequent source-control management. Perforated appendicitis with retroperitoneal contamination supported appendiceal-source contiguous spread to the iliac artery. Case 2 involved a distal abdominal aortic infected pseudoaneurysm with rupture near the inferior mesenteric artery origin; persistent peri-aortic fluid after EVAR required laparoscopic hematoma evacuation and lesion resection. Case 3 involved an infrarenal infected aortic pseudoaneurysm with bilateral common iliac involvement; delayed fever, Escherichia coli bacteremia, and right iliac limb occlusion led to thrombectomy, which retrieved inflammatory fibrinous debris.
Conclusions:
In infective native aorto-iliac aneurysms, emergency EVAR can control the immediate risk of rupture, but exclusion of the aneurysm does not eradicate infection. After EVAR, persistent fever, pain, elevated inflammatory markers, bacteremia, or peri-graft fluid or gas should prompt a search for a residual or occult gastrointestinal, retroperitoneal, or urinary source. An appendiceal source of Klebsiella pneumoniae iliac pseudoaneurysm is rare, and recognizing it may allow timely source control. The short follow-up and small number of patients limit broader conclusions.
Related Concept Videos
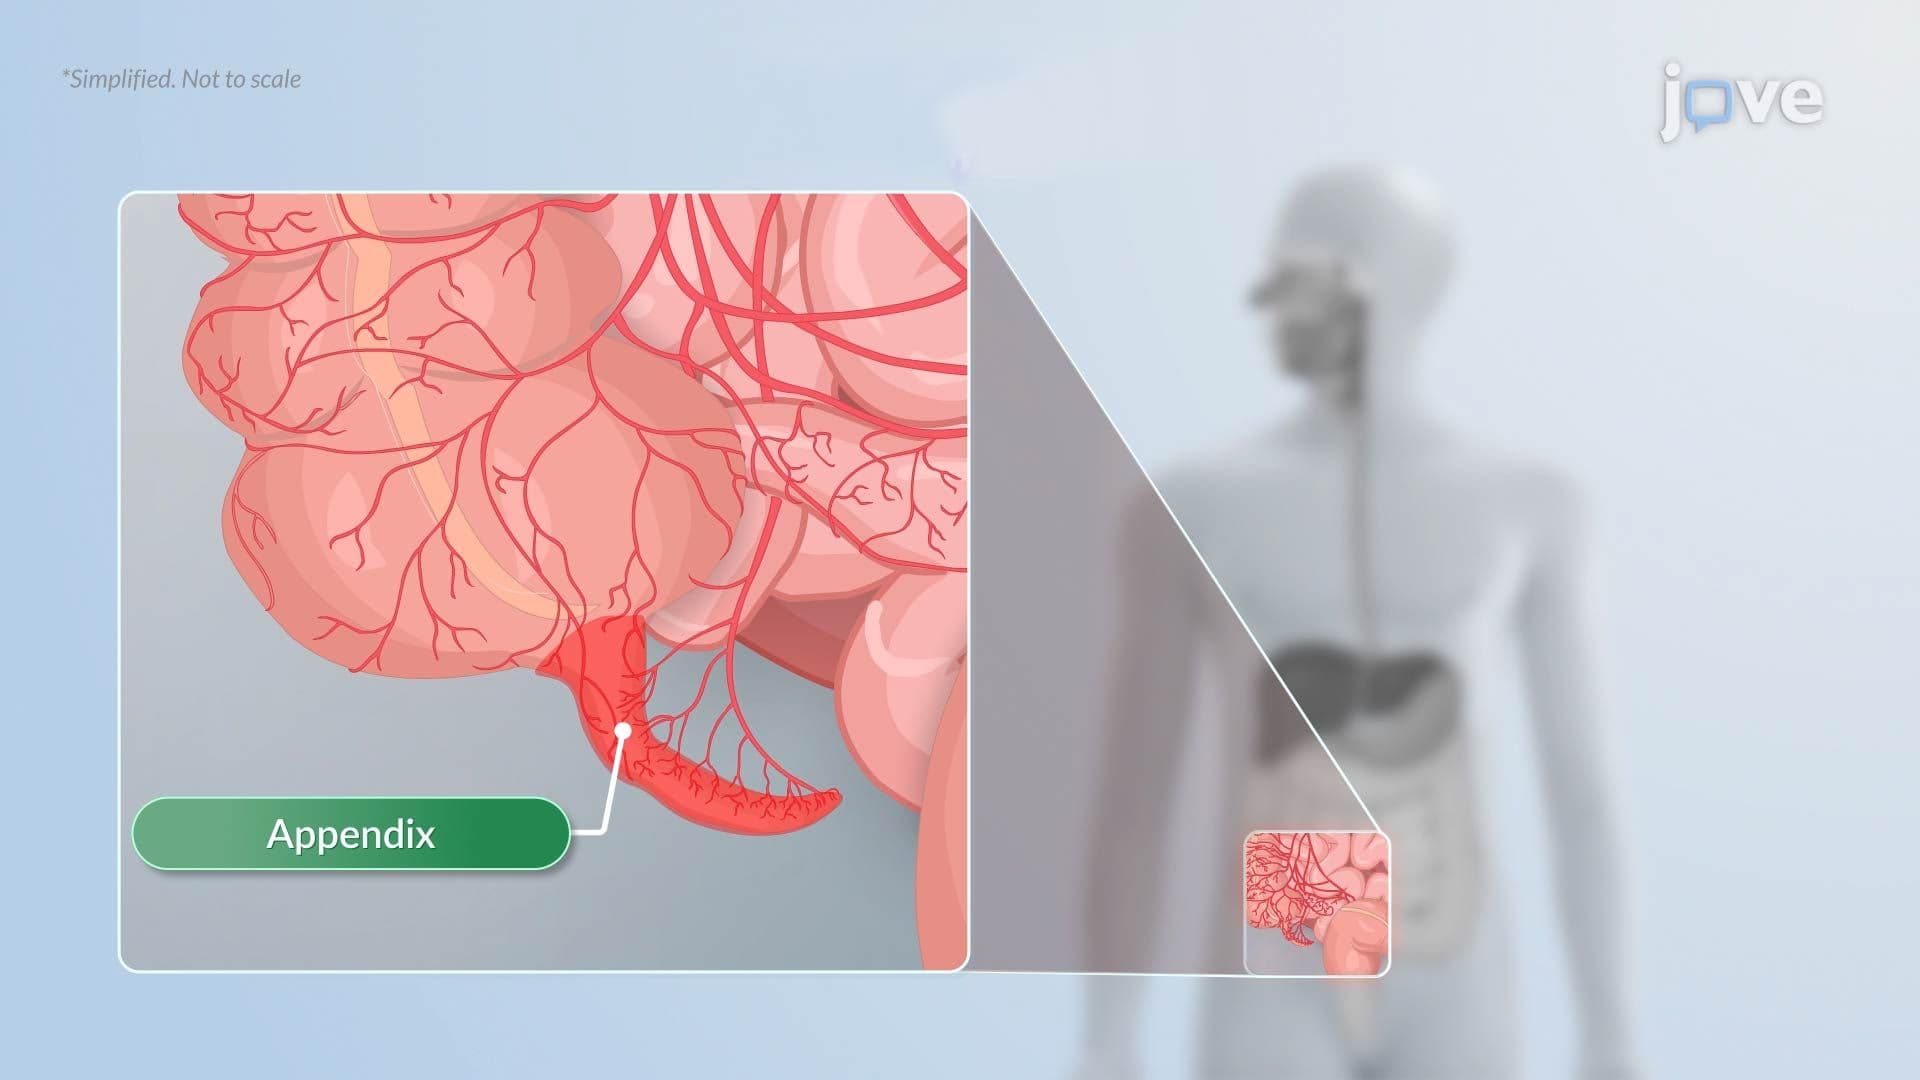 01:19
Appendicitis
 01:22
Appendicitis-I: Introduction
Etiology: Appendicitis can arise from various causes, primarily rooted in the obstruction of the appendix lumen. Factors contributing to this obstruction include fecal accumulation, lymphoid hyperplasia and, in...
 01:26
Aneurysm III: Interprofessional Care
 01:30
Aneurysm I: Introduction
 01:21
Aneurysm II: Clinical Manifestations and Diagnostic Studies
 01:29
Appendicitis-II: Diagnostic Studies and Management
Diagnosing Appendicitis
It requires a multifaceted approach, starting with a detailed physical examination to pinpoint the location and nature of the pain and identify any associated symptoms. Laboratory tests play a crucial role. A complete Blood Count (CBC) typically reveals leukocytosis (an increased number of...