Related Experiment Video
Updated: Aug 6, 2026
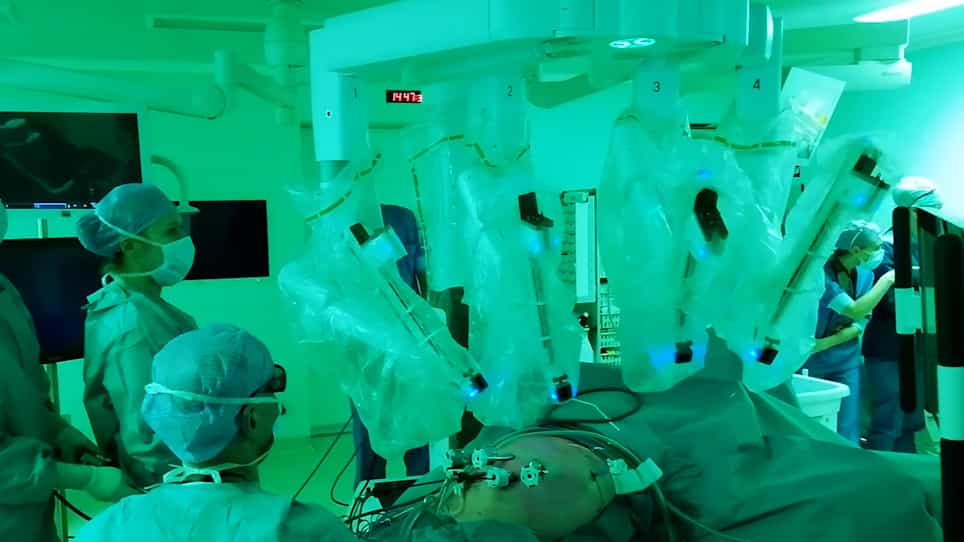

Robotic Pancreatoduodenectomy for Pancreatic Head Cancer: a Case Report of a Standardized Technique
Published on: June 24, 2022
Robotic-assisted pancreaticoduodenectomy: Portal vein-first vs artery-first approach
Yong-Sian Chen1, Yi-Ju Chen1,2, Chia-Man Chou1,2,3
1Department of Surgery, Taichung Veterans General Hospital, Taichung, Taiwan, ROC.

Background:
Robotic pancreaticoduodenectomy (RPD) has emerged as a promising approach for complex pancreatic surgeries. Artery-first approach pancreaticoduodenectomy (AFAPD) prioritizes the early assessment of arterial involvement to improve surgical outcomes. This study compares the clinical, perioperative, and oncological outcomes of AFAPD and traditional portal vein-first pancreaticoduodenectomy (tPD) in patients undergoing RPD.
Methods:
A retrospective analysis was conducted on 151 patients who underwent RPD at a tertiary center in Taiwan from June 2019 to July 2025. Patients were categorized into robotic tPD (n = 81) and AFAPD (n = 70) groups. Propensity score matching (PSM, 1:1) was performed to reduce selection bias. Survival outcomes were analyzed through the Kaplan-Meier method and compared using the log-rank test, and Cox proportional hazards models were employed to estimate hazard ratios with 95% confidence intervals.
Results:
After PSM, no significant difference was observed in the baseline characteristics of both groups. In the matched cohort, no significant differences were found between the two groups in terms of operative time (518.5 vs 480.0 minutes, p = 0.269) or estimated blood loss (200 vs 150 mL, p = 0.106). However, compared with the tPD group, the AFAPD group was associated with a significantly lower rate of delayed gastric emptying (DGE, 15.4% vs 36.5%, p = 0.027). Other complications, such as postpancreatectomy hemorrhage (3.8% vs 11.5%, p = 0.289) and abdominal abscess (1.9% vs 7.7%, p = 0.375), showed lower trends in the AFAPD group than in the tPD group but did not reach statistical significance in the matched cohort. The AFAPD group also had a higher incidence of chylous leakage (19.2% vs 7.7%, p = 0.146) than the tPD group. Overall survival was significantly shorter in the AFAPD group than in the tPD group because of the retrospective design of this study and the recent adoption of the AFAPD approach (15.47 vs 36.15 months, p < 0.001).
Conclusion:
Robotic AFAPD provides perioperative outcomes comparable to those yielded by tPD while significantly reducing DGE. While it has a higher trend of chylous leakage than tPD, it remains a technically superior approach for ensuring early arterial assessment and surgical radicality.
