Related Experiment Video
Updated: Aug 6, 2026
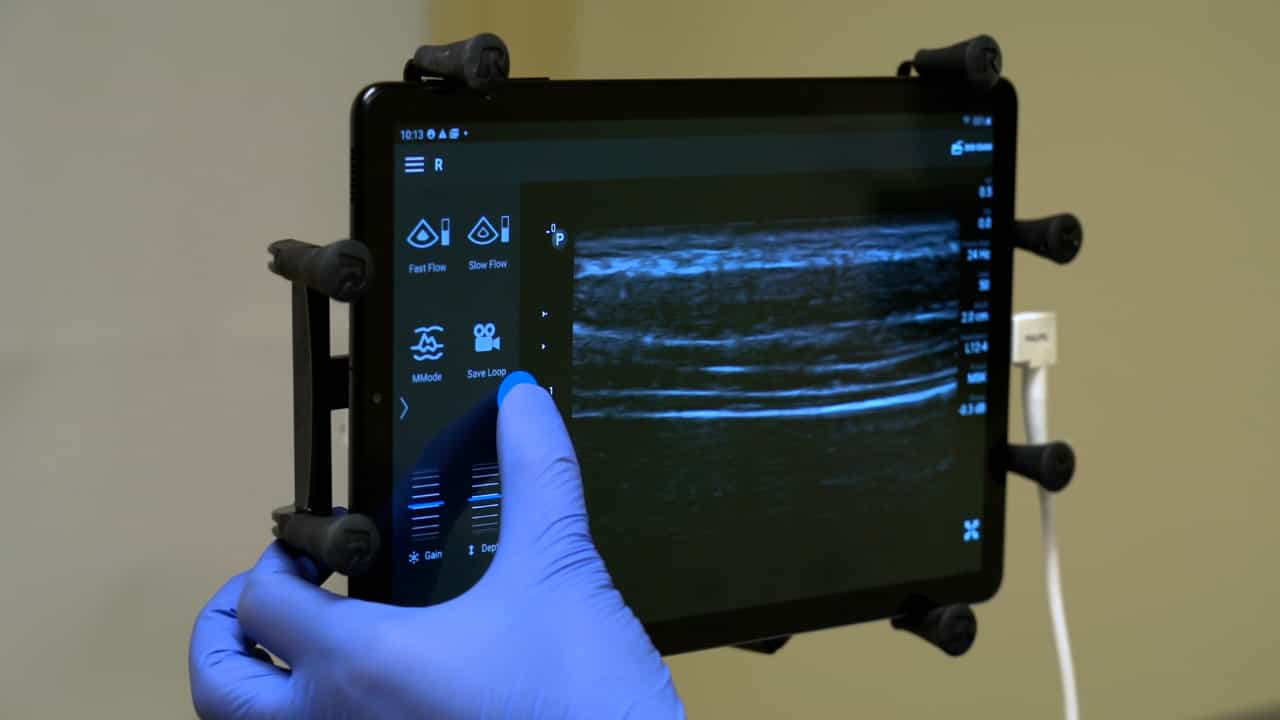

Measuring Diaphragm Thickness and Function Using Point-of-Care Ultrasound
Published on: November 3, 2023
Association of Diaphragmatic Crus Thickness Assessed by Computed Tomography with Diaphragmatic Excursion and Exercise
Masashi Shiraishi1, Yuji Higashimoto2, Hiroki Mizusawa2
1Department of Rehabilitation Medicine, Kindai University Hospital, Faculty of Medicine, Kindai University, 1-14-1 Miharadai, Minami-ku, Sakai, Osaka, 590-0197, Japan. masashi-shiraishi@med.kindai.ac.jp.

Purpose:
Diaphragmatic dysfunction contributes to exercise intolerance in chronic obstructive pulmonary disease (COPD). Although diaphragmatic excursion during deep breathing (DEmax) is associated with exercise capacity, the relationship between computed tomography (CT)-derived diaphragm morphology and diaphragmatic function remains unclear. We investigated the association of CT-derived diaphragmatic crus thickness with diaphragmatic excursion and exercise capacity in COPD.
Methods:
This retrospective single-centre study included 100 patients with stable COPD who underwent chest CT, spirometry, ultrasonographic assessment of DEmax, and 6-minute walk distance (6MWD) testing. Diaphragmatic crus thickness was measured on axial CT images, and the diaphragmatic thickness index (DTI) was calculated after adjustment for body mass index. Multivariable linear regression analyses were performed to identify factors independently associated with DEmax and 6MWD. Patients were stratified according to DTI and DEmax to evaluate combined structural and functional diaphragm phenotypes.
Results:
In multivariable analyses, DTI was independently associated with DEmax (β = 0.57, p < 0.001) and 6MWD (β = 0.25, p < 0.01) after adjustment for age, pulmonary function, and skeletal muscle indices. The combined low-DTI/low- DEmax phenotype was independently associated with reduced exercise capacity (6MWD < 350 m; odds ratio 14.89, 95% confidence interval 3.51-87.89, p < 0.001).
Conclusion:
CT-derived diaphragmatic thickness was independently associated with diaphragmatic excursion and exercise capacity in COPD. Combined structural and functional diaphragm assessment identified patients with markedly reduced exercise capacity, suggesting a role for integrated diaphragm evaluation in functional risk stratification.

Related Concept Videos
 01:27
Chronic Obstructive Pulmonary Disease-IV: Assessement and Diagnostic Studies
Medical History
 01:24
Physical Assessment of the Respiratory Tract II: Palpation
Thoracic Palpation
Thoracic palpation detects tenderness, masses, lesions, respiratory excursions, and vocal fremitus. The nurse assesses...
 01:29
Physical Assessment of the Respiratory Tract III: Percussion
Percussion in Respiratory Assessment
Percussion evaluates underlying tissue composition with audible and tactile vibrations,...
 01:30
Respiratory System Abnormal Finding I: Inspection and Percussion
Inspection Findings
During an inspection, several findings may suggest the presence of respiratory distress or disease. Pursed-lip breathing, where exhalation is slowed by...
 01:25
Muscles of the Thorax
The diaphragm is at the core of thoracic musculature, the primary muscle involved in breathing. This expansive, dome-shaped muscle marks the division between the thoracic and abdominal cavities. It originates...
 01:29
Assessment of Ventilation II: Respiratory Depth and Rhythm
Respiratory depth measures the volume of air inhaled or exhaled during a breath. It can vary from shallow to deep and typically remains consistent when a person is at rest or asleep. Occasionally, individuals will automatically inhale deeply, known as sighing, which inflates the lungs with more air than normal breathing.
To assess respiratory depth, observe the degree of chest excursion or movement: