Related Experiment Video
Updated: Aug 6, 2026
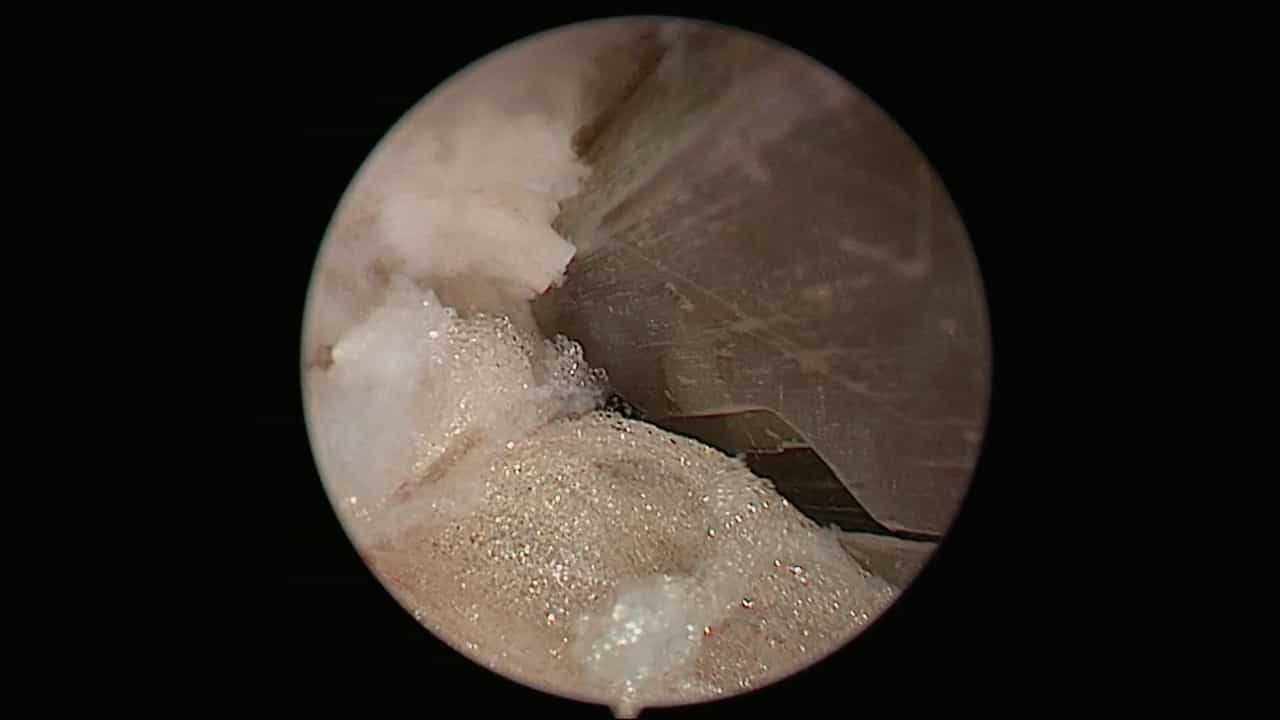

The Third Channel-Assisted Unilateral Biportal Endoscopic Technique for Lumbar Spinal Stenosis Combined with Contralateral Disc Herniation
Published on: November 17, 2023
Cost-effectiveness of biportal endoscopic spine surgery compared with microscopic surgery for lumbar degenerative
Sang-Min Park1, Kwang-Sup Song2, Ho-Joong Kim1
1Spine Center and Department of Orthopaedic Surgery, Seoul National University College of Medicine and Seoul National University Bundang Hospital, Seongnam, Korea.

Background Context:
Although biportal endoscopic spine surgery (BESS) has shown clinical benefits for lumbar degenerative diseases, comprehensive cost-utility analyses comparing BESS with microscopic spine surgery (MSS) remain limited.
Purpose:
We aimed to compare the cost-effectiveness of BESS and MSS for lumbar degenerative diseases from a healthcare provider's perspective using quality-adjusted life years (QALYs) as the effectiveness measure.
Study Design:
This economic evaluation was conducted alongside 2 multicenter, prospective, blinded, randomized controlled trials (ENDO-BH for lumbar disc herniation and ENDO-BS for lumbar spinal stenosis) at 6 tertiary hospitals in South Korea.
Patient Sample:
Overall, 220 patients aged 20 to 80 years requiring single-level lumbar surgery were randomized to the BESS or MSS groups, and 187 patients with complete 12-month follow-up data were included in the analysis (BESS, 96; MSS, 91).
Outcome Measures:
The primary outcome was the incremental cost-effectiveness ratio expressed as cost per QALY gained. Secondary outcomes included net monetary benefit (NMB) and probability of cost-effectiveness at the Korean willingness-to-pay (WTP) threshold. QALYs were calculated using the area under the curve of EQ-5D-5L utility values measured at baseline, 2 weeks, 3 months, 6 months, and 12 months postoperatively.
Methods:
Costs were measured from the healthcare provider's perspective using institutional billing data adjusted to Korean won (KRW). Non-parametric bootstrapping (5,000 iterations) was performed to estimate uncertainty, and cost-effectiveness acceptability curves were constructed.
Results:
The mean 1-year QALYs were 0.823±0.079 for BESS and 0.801±0.112 for MSS. The total costs were USD 3,028 for BESS and USD 3,080 for MSS. Confidence intervals for incremental costs and QALYs crossed zero. At the WTP threshold of USD 21,429 (30,000,000 KRW) per QALY, the probability that BESS would be cost-effective was 94.9%.
Conclusions:
BESS is a cost-effective alternative to MSS for treating lumbar degenerative diseases, with a cost-effectiveness probability of 94.9% at the WTP threshold during the 12-month follow-up. Neither technique showed a statistically significant advantage in terms of cost or QALYs, indicating that BESS can be adopted without increasing direct medical costs.
Level Of Evidence:
I.