Related Experiment Video
Updated: Aug 6, 2026
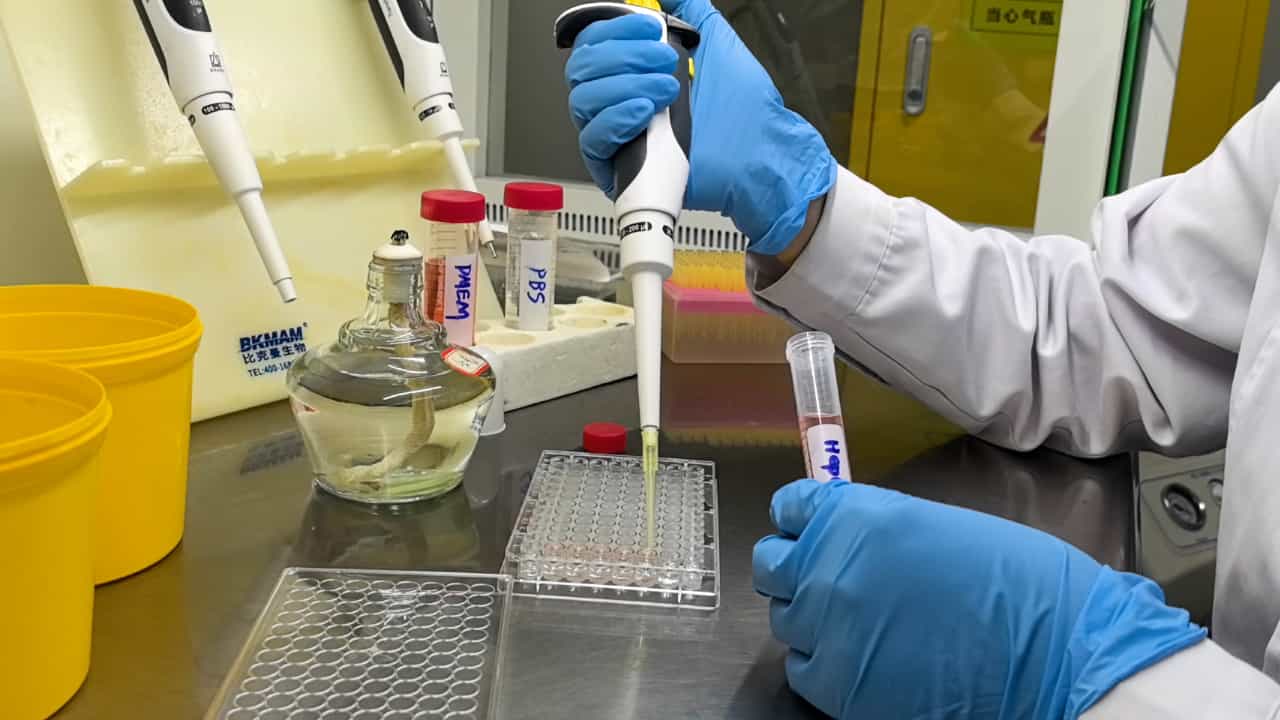

In Vitro Modeling of Fat Deposition in Metabolic Dysfunction-Associated Steatotic Liver Disease
Published on: July 19, 2024
Regional Inequities in Metabolic Dysfunction-associated Steatotic Liver Disease Burden and Care Quality in
Kexin Zhang1, Chengxia Kan2,3, Sufang Sheng2,3
1Department of Endocrinology and Metabolism, Tongji Hospital, School of Medicine, Tongji University, Shanghai, China.

Background And Aims:
Metabolic dysfunction-associated steatotic liver disease (MASLD) is increasing rapidly, yet regional differences in burden and care quality remain unclear. This study aimed to compare regional incidence, mortality, and disability; evaluate care quality; identify key determinants; and project future incidence.
Methods:
We analyzed the Global Burden of Disease 2023 estimates of MASLD incidence, deaths, and disability-adjusted life years from 1990 to 2023 by age, sex, country, and region. Age-standardized rates were assessed using joinpoint regression. A composite Quality of Care Index (QCI) was derived through principal component analysis. Gradient boosting models with SHapley Additive exPlanations interpretation identified key predictors, and Bayesian age-period-cohort models generated incidence projections.
Results:
In 2023, South and East Asia had the largest numbers of new cases, while North Africa and the Middle East and Andean Latin America recorded the highest age-standardized incidence, mortality, and disability rates. Eastern Europe and Andean Latin America showed sustained increases in mortality and disability despite moderate incidence growth. QCI values were lowest in South Asia, Western Sub-Saharan Africa, and Eastern Europe. High body mass index and fasting plasma glucose were prominent contributors in comparative risk attribution analyses, and machine learning models identified age and calendar year as the strongest predictors of modeled burden patterns. Incidence is projected to continue increasing through 2050, particularly in India and China.
Conclusions:
MASLD burden and care quality vary widely across regions. Low-QCI regions show higher mortality and disability, unfavorable metabolic risk profiles, and delayed detection patterns. Strengthening prevention, early case finding, fibrosis assessment, and treatment access may slow MASLD progression.


Related Concept Videos
 01:22
Effect of Hepatic Disease on Pharmacokinetics: Pathophysiologic Assessment and Liver Function Test
 01:26
Effect of Hepatic Disease on Pharmacokinetics: Drug Dosing and Hepatic Blood Flow
 01:23
Cirrhosis I: Introduction
 01:26
Diseases of the Liver and Gallbladder
Cirrhosis is characterized by the scarring of hepatic lobules in the liver, which are replaced by fibrous tissue, affecting the liver's normal functioning. NAFLD, on the other hand, is caused by an excessive build-up of fat in the liver, not related to...
 01:20
Pharmacokinetics in Obese Patients: Drug Metabolism and Excretion
 01:24
Cirrhosis II: Pathophysiology