Related Experiment Video
Updated: Aug 6, 2026


Multilevel Microdissection and Functional-Structural Profiling of Human Renal Arterial Branches
Published on: September 5, 2025
Ultra-Low Contrast versus Conventional Percutaneous Coronary Intervention for Patients with Baseline Renal
Marcos Danillo Oliveira1, Ricardo Fonseca Oliveira Suruagy-Motta2, Leonardo Dexheimer da Silva3
1Departamento de Cardiologia Intervencionista, Universidade Federal de São Paulo, São Paulo, SP - Brasil.

Insights
Ultra-low contrast (ULC) percutaneous coronary intervention (PCI) significantly reduces contrast-associated acute kidney injury (CA-AKI) in patients with chronic kidney disease. While safe and feasible, further trials are needed to confirm effects on dialysis, mortality, and MACE.
Area of Science:
- Nephrology
- Cardiology
- Interventional Cardiology
- Radiology
Background:
- Contrast-associated acute kidney injury (CA-AKI) significantly increases patient morbidity, mortality, and healthcare costs.
- Limiting contrast volume (CV) and utilizing ultra-low contrast (ULC) volume coronary procedures (total CV ≤ estimated glomerular filtration rate [eGFR]) are associated with reduced CA-AKI risk.
Purpose of the Study:
- To conduct a systematic review and meta-analysis comparing clinical outcomes of ULC versus conventional percutaneous coronary intervention (PCI) in patients with chronic kidney disease.
Main Methods:
- Comprehensive literature search across major databases (PubMed/MEDLINE, Cochrane, Embase, Scopus, Web of Science).
- Inclusion of studies reporting clinical outcomes of ULC PCI.
- Primary endpoint: incidence of CA-AKI. Secondary endpoints: need for dialysis, all-cause mortality, and major adverse cardiovascular events (MACE).
Main Results:
- Analysis of six studies involving 274,102 patients.
- ULC PCI demonstrated a statistically significant reduction in CA-AKI incidence (risk ratio=0.27; p=0.0004).
- No statistically significant reductions were observed for need for dialysis (p=0.186), all-cause mortality (p=0.18), or MACE (p=0.16).
Conclusions:
- ULC PCI is safe and feasible compared to conventional PCI in patients with chronic kidney disease.
- ULC PCI is associated with a significant reduction in CA-AKI.
- Larger, well-powered randomized controlled trials are necessary to confirm these findings and assess other clinical outcomes.
Background:
Contrast-associated acute kidney injury (CA-AKI) results in increased morbidity and mortality, prolonged hospitalization, and worse clinical outcomes. Prior studies have shown that limiting contrast volume (CV) to less than 3 times the estimated glomerular filtration rate (eGFR) implies a lower risk of CA-AKI, and both efficacy and superior outcomes are associated with ultra-low contrast (ULC) volume coronary procedures (total CV ≤ eGFR).
Objectives:
This systematic review and meta-analysis aimed to compare clinical outcomes of ULC versus conventional percutaneous coronary intervention (PCI) in patients with chronic kidney disease.
Methods:
The search was conducted in the databases PubMed/MEDLINE, Cochrane, Embase, Scopus, and Web of Science, including all studies reporting clinical outcomes of ULC PCI. The primary efficacy endpoint was the incidence of CA-AKI, and secondary endpoints were need for dialysis, all-cause mortality, and major adverse cardiovascular events (MACE), defined as the composite endpoint of all-cause mortality, non-fatal myocardial infarction, and clinically driven target lesion revascularization.
Results:
Six studies met the inclusion criteria and were included in the final analysis, encompassing a total of 274,102 patients. ULC PCI was associated with a statistically significant reduction of CA-AKI (risk ratio=0.27; 95% CI=0.13-0.56; p=0.0004). In turn, ULC PCI did not result in statistically significant reduction of need for dialysis (risk ratio=0.33; 95% CI=0.06-1.72; p=0.186), all-cause mortality (risk ratio=0.48; 95% CI=0.17-1.39; p=0.18), and MACE (risk ratio=0.52; 95% CI= 0.21-1.30; p=0.16).
Conclusions:
ULC, as compared to conventional PCI, in patients with chronic kidney disease, was found to be safe, feasible, and associated with a statistically significant reduction of CA-AKI. Further, larger, well-powered, randomized, and controlled trials are warranted in order to reassure these findings.
Related Concept Videos
 01:17
Factors Affecting Renal Clearance: Renal Impairment
One condition associated with renal failure is uremia. Uremia is characterized by impaired glomerular filtration and fluid accumulation in the body. This condition hinders the renal clearance of drugs, resulting in drug accumulation and potential...
 01:06
Renal Drug Clearance: Overview
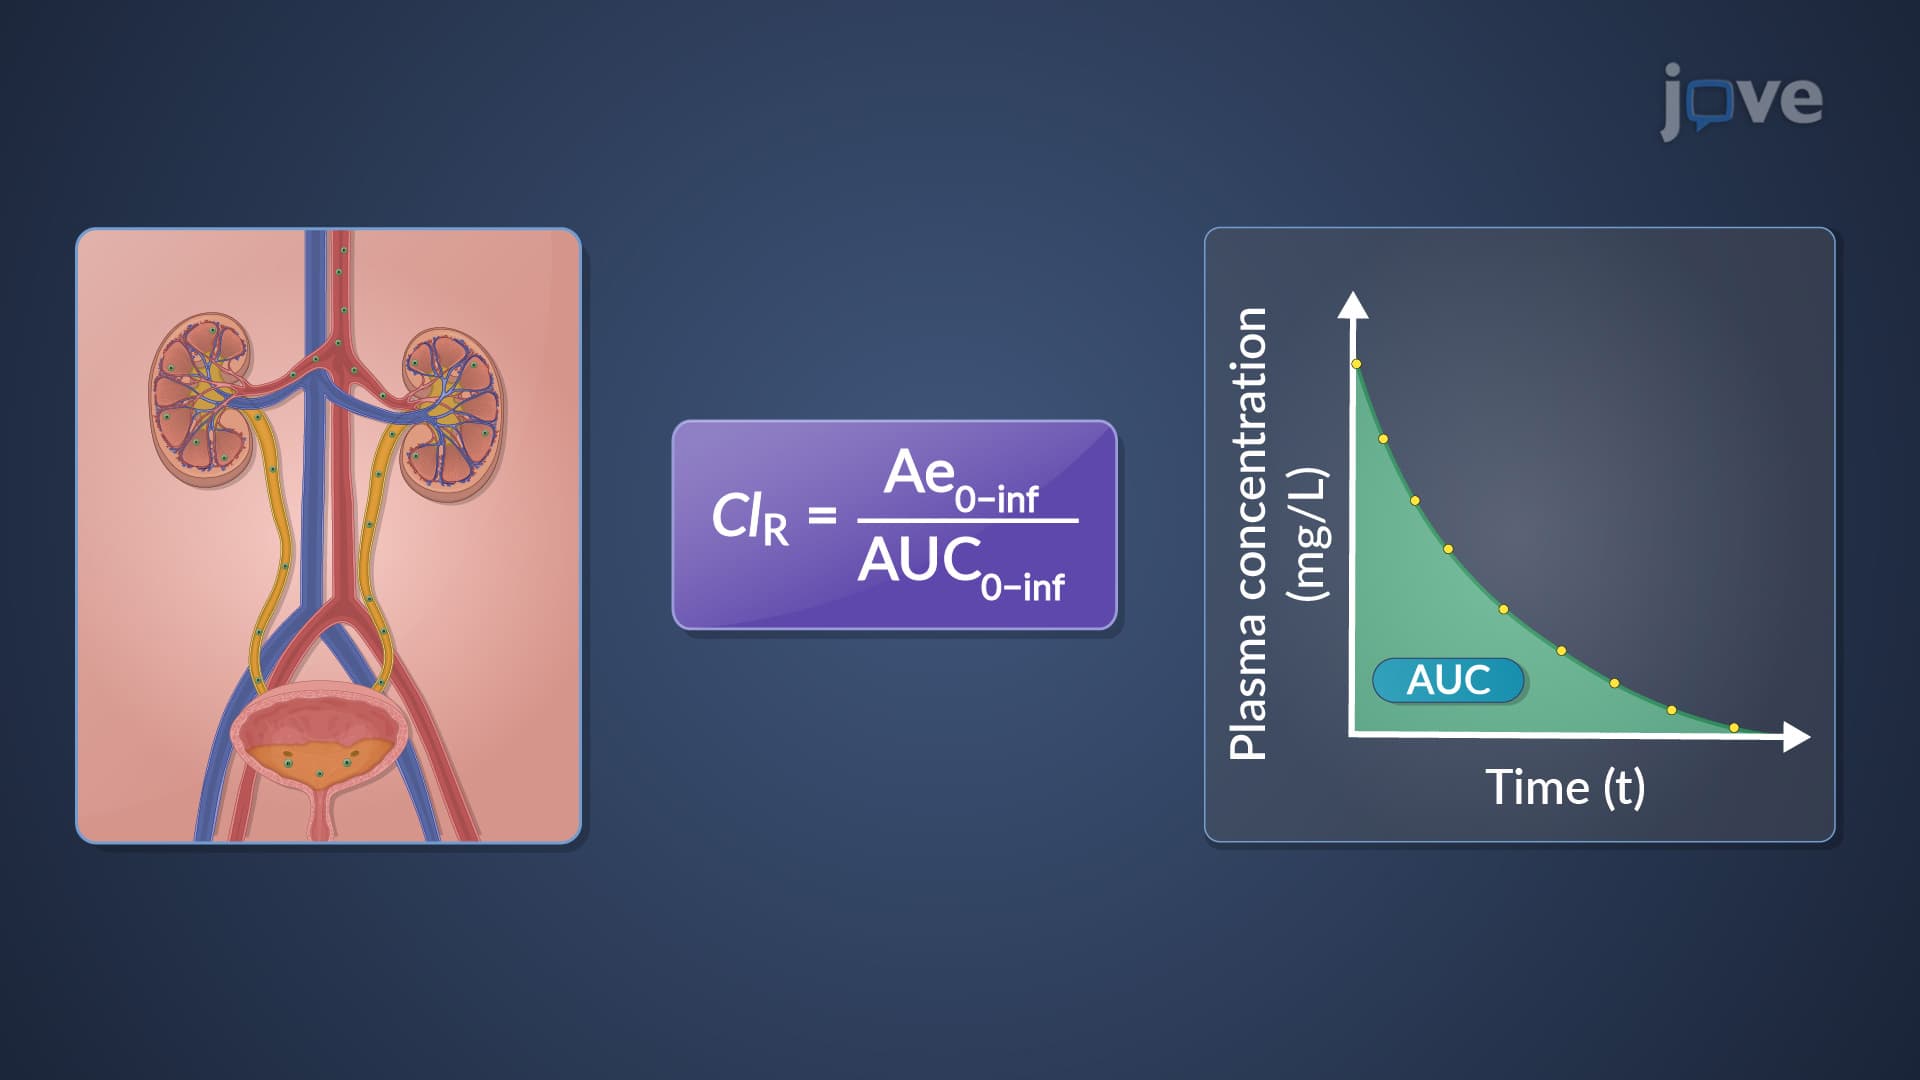
Renal clearance can be calculated using different methods. One approach is to divide the urinary drug excretion rate by the plasma drug concentration. This method directly measures renal clearance, indicating the kidneys' efficiency in...
 01:11
Renal Failure: Dose Adjustments
Reduced renal clearance and elimination rate are common outcomes of renal impairment. These alterations lead to a prolonged elimination half-life and an altered apparent volume of distribution for drugs. As a result, dosage adjustments are typically necessary to maintain optimal drug levels in the body.
However, dosage adjustments...
 01:28
Drug Dosing in Renal Diseases: Estimation of Glomerular Filtration Rate Based on Serum Creatinine Concentration
 01:30
Acute Kidney Injury IV: Diagnostic Studies and Prevention
 01:25
Drug Dosing in Renal Diseases: Dose Adjustments Based on Drug Clearance and Elimination Rate Constant