Related Experiment Video
Updated: Aug 6, 2026
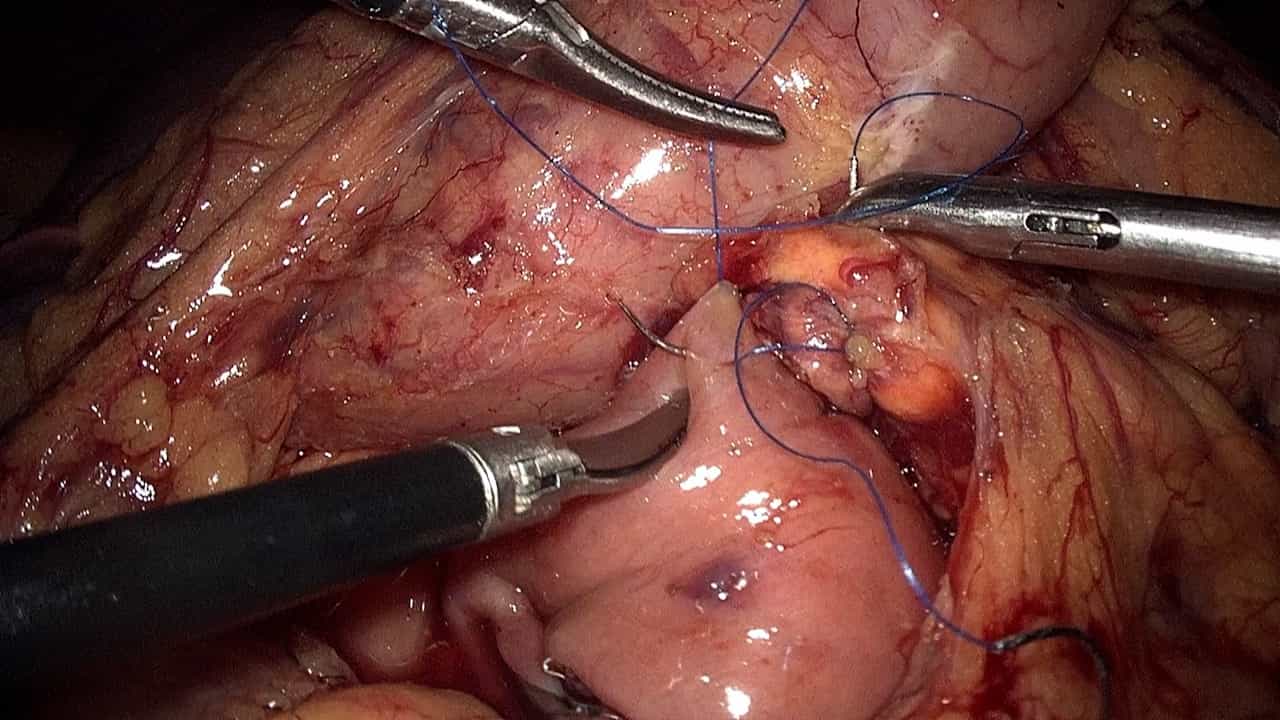

Laparoscopic Duodenum-Preserving Pancreatic Head Resection via Inferior Infracolic Approach: A Surgical Approach for Benign Lesions
Published on: February 9, 2024
Indocyanine green fluorescence-guided intraoperative biliary mapping during pediatric laparoscopic
Xuming Liu1, Guantong Li1, Yong Zhao1
1Department of Neonatal Surgery, Neonatal Center, Beijing Children's Hospital, Capital Medical University, Beijing, China.

Background:
Laparoscopic duodenum-preserving pancreatic head resection (LDPPHR) for focal congenital hyperinsulinism (CHI) poses a specific intraoperative challenge: reliable, continuous identification of the intrapancreatic common bile duct (CBD) in an anatomically diminutive, tactile-feedback-free operative field. We describe a standardized indocyanine green (ICG) fluorescence-guided biliary visualization workflow for pediatric LDPPHR and report its initial implementation experience.
Methods:
In this retrospective case series, we summarized the application of this standardized workflow in seven consecutive children with focal CHI who underwent ICG fluorescence-guided LDPPHR at Beijing Children's Hospital from February 2025 to March 2026. The workflow comprised seven sequential steps: exposure and preparation, first-dose ICG administration, initial biliary mapping, boundary-guided pancreatic head dissection, repeated fluorescence assessment and reinjection when required, post-resection perfusion assessment, and reconstruction with final intraoperative checking.
Results:
The workflow was completed as planned in all seven cases, with full workflow adherence in 7/7 procedures. Continuous visualization of the intrapancreatic CBD under near-infrared (NIR) illumination was achieved in 7/7 procedures. Repeated white-light/NIR correlation was feasible throughout dissection in all cases. The fluorescence-guided workflow was implemented without intraoperative abandonment. No bile leak, clinically relevant postoperative pancreatic fistula (ISGPS 2016 criteria), or duodenal ischemia was observed. Median operative time was 310 min (range 229-570 min).
Conclusions:
This stepwise ICG biliary visualization workflow was technically feasible and was implemented without biliary adverse events in this initial retrospective case series. As a workflow description with feasibility observations rather than an efficacy study, this report suggests that repeated real-time delineation of the intrapancreatic CBD may facilitate duct-sparing dissection; whether it reduces bile duct injury requires validation in larger comparative studies.