Related Experiment Video
Updated: Aug 6, 2026

Analyses of Proteinuria, Renal Infiltration of Leukocytes, and Renal Deposition of Proteins in Lupus-prone MRL/lpr Mice
Published on: June 8, 2022
Finerenone as adjunctive therapy for residual proteinuria in lupus nephritis: a case series of 10 patients
Rui Gao1, Jianan Wang1,2, Qi Liu1,2
1School of Clinical Medicine, Shandong Second Medical University, Weifang, Shandong, China.

Introduction:
After baseline immunosuppression and renin-angiotensin system inhibitor (RASi) treatment for lupus nephritis (LN), the persistence of residual proteinuria is a core risk factor for poor renal prognosis, which is closely related to continuous progression of renal inflammation and fibrosis and long-term elevated risk of end-stage renal disease. Finerenone is a highly selective non-steroidal mineralocorticoid receptor antagonist (MRA) that has been proven to reduce proteinuria and exert renal protective effects in diabetic nephropathy. However, its association with proteinuria changes and safety profile in residual proteinuria of LN remain.
Methods:
This single-center retrospective case series enrolled 10 patients with clinically diagnosed LN who had residual proteinuria (24-h urine protein quantification ≥0.5 g) despite ≥6 months of standard treatment. Finerenone 10 mg once daily was added to the original treatment, and patients were followed for 24 weeks. The primary endpoint was change in 24-h urine protein quantification; secondary endpoints included serum albumin, estimated glomerular filtration rate (eGFR), and safety parameters. Data were presented as median (interquartile range, P25, P75). Repeated measurements were compared using the Friedman test with Bonferroni correction.
Results:
At baseline, 12 weeks, and 24 weeks, 24-h urine protein quantification was 1.595 g (1.52, 2.37), 1.06 g (0.79, 1.63), and 0.315 g (0.27, 0.35), respectively (χ2 = 18.20, p < 0.001). Serum albumin showed an increase from 3.68 g/ dL (3,680 mg/dL, 3,530-3,770 mg/dL) to 4.075 g/dL (4,075 mg/dL, 3,910-4,200 mg/dL). eGFR remained stable during follow-up, changing from 108.3 mL·min-1·(1.73 m2)-1 (88.3, 112.3) to 113.95 mL·min-1·(1.73 m2)-1 (96.6, 119.7). All patients completed the 24-week follow-up.
Conclusion:
In this case series, add-on low-dose finerenone (10 mg/d) was associated with a significant reduction in residual proteinuria, an increase in serum albumin, stable renal function, and favorable safety in LN patients. These observational findings require validation in controlled trials.
Related Concept Videos
 01:26
Nephrotic Syndrome II : Assessment and Medical Management
 01:11
Renal Failure: Dose Adjustments
Reduced renal clearance and elimination rate are common outcomes of renal impairment. These alterations lead to a prolonged elimination half-life and an altered apparent volume of distribution for drugs. As a result, dosage adjustments are typically necessary to maintain optimal drug levels in the body.
However, dosage adjustments...
 01:25
Antihypertensive Drugs: Direct Renin Inhibitors
 01:15
Renal Drug Excretion: Overview
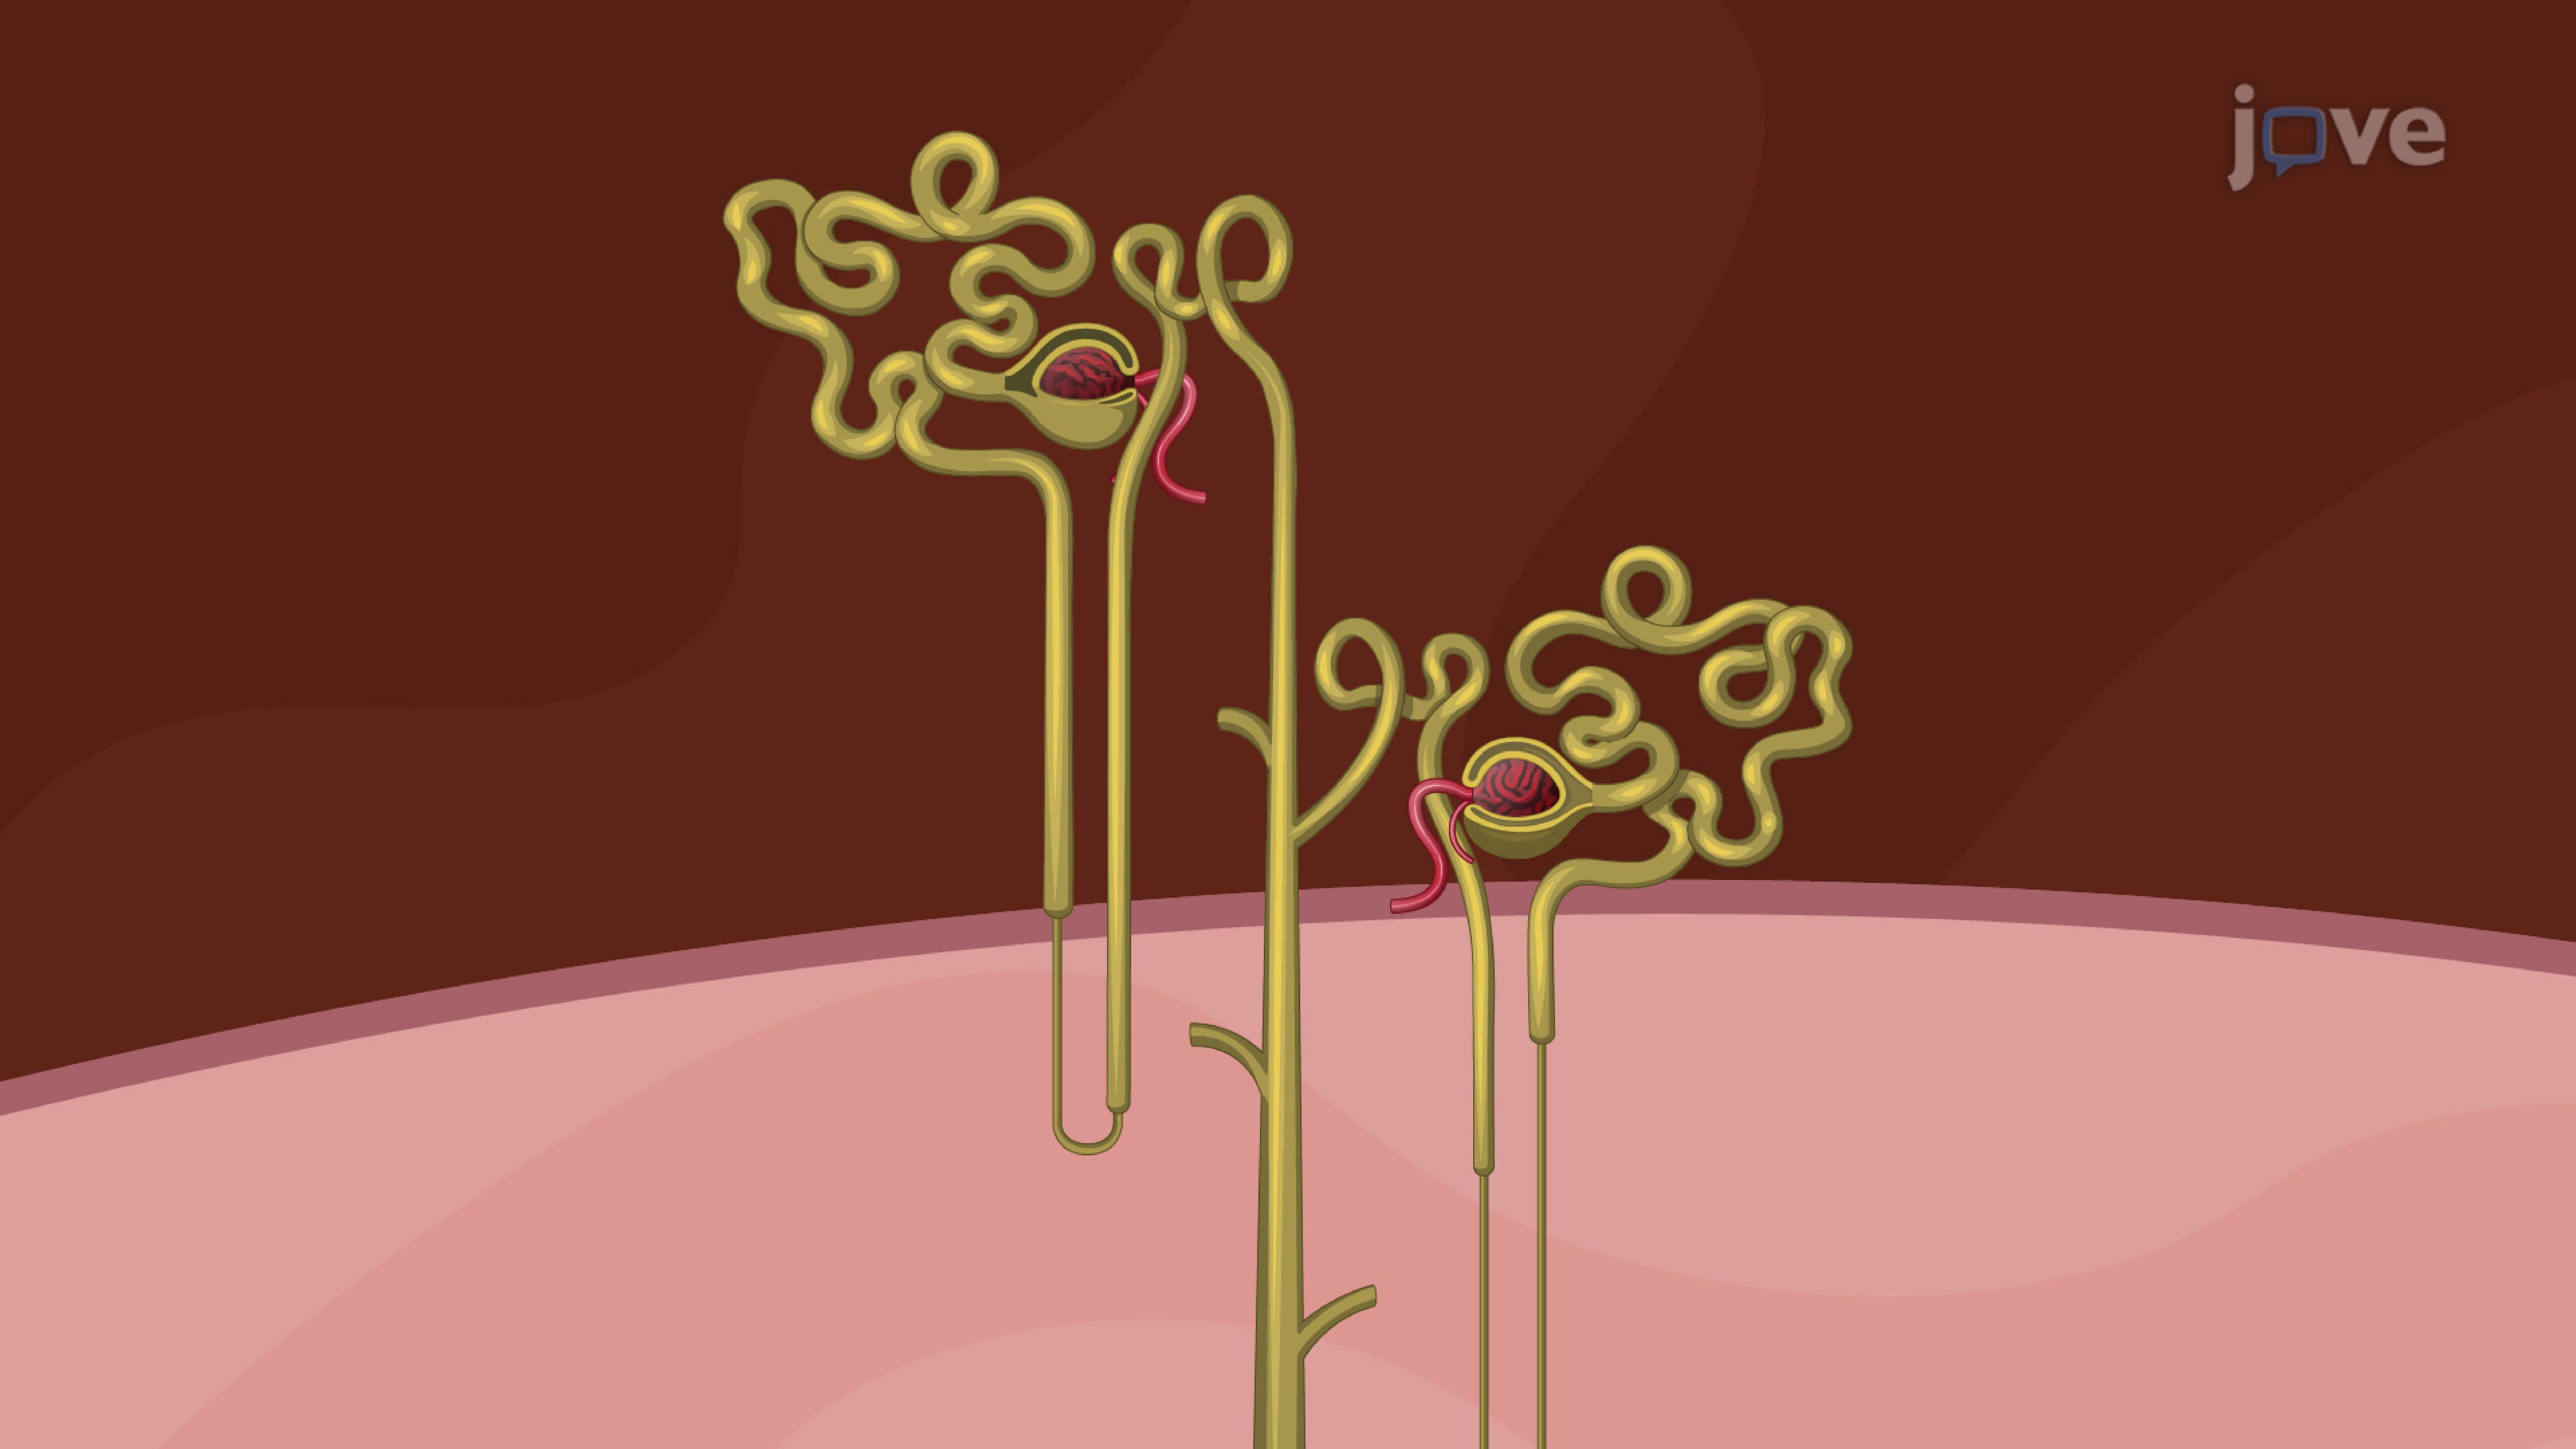
A nephron consists of two primary structures: the renal corpuscle and the renal tubule. The renal corpuscle contains the glomerulus, a network of capillaries where the first step of renal excretion, glomerular filtration, occurs. Blood pressure forces water, ions, and small molecules out...
 01:24
Nephrotic Syndrome I : Introduction
 01:28
Drug Dosing in Renal Diseases: Estimation of Glomerular Filtration Rate Based on Serum Creatinine Concentration