Related Experiment Video
Updated: Aug 6, 2026
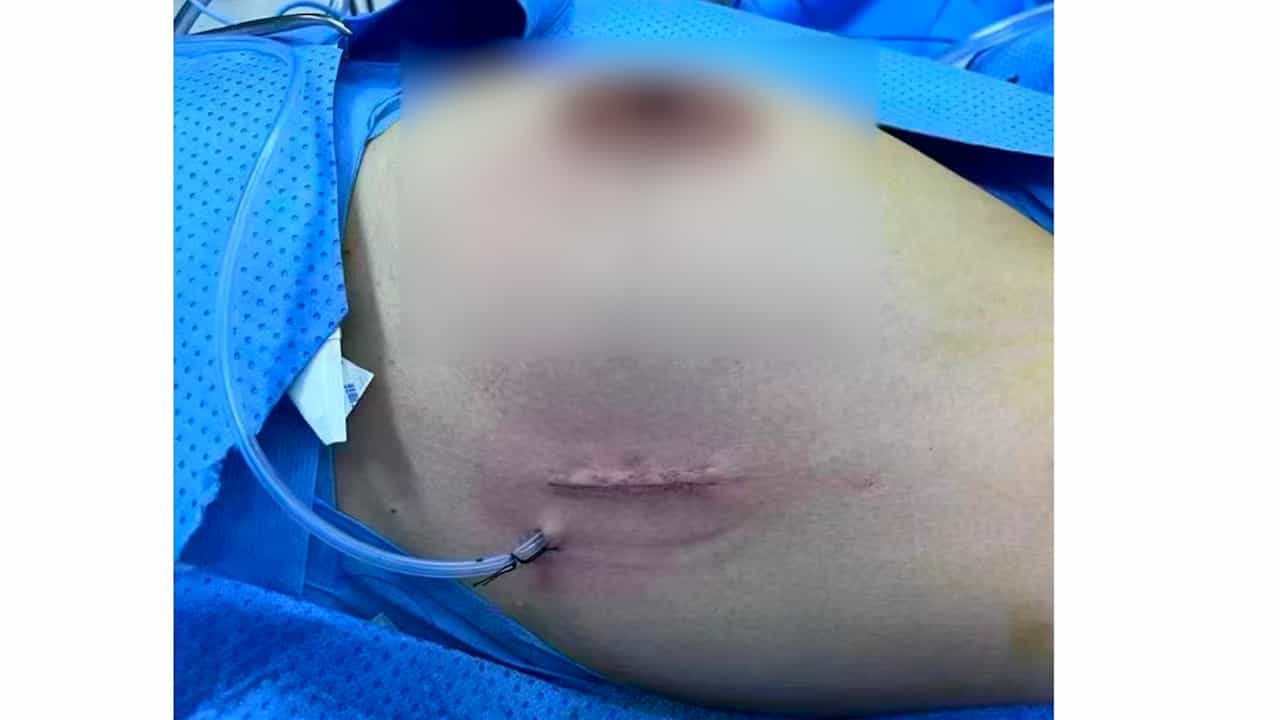
Single-port Non-liposuction Endoscopic Axillary Lymph Node Dissection in Breast Cancer Surgery
Published on: April 3, 2026
[18F]FDG PET/MRI for axillary staging in node positive breast cancer patients receiving primary systemic therapy. A
Rosa Di Micco1, Edoardo Botteri2, Carla Canevari3
1Breast Surgery Unit, IRCCS Ospedale San Raffaele, Milan, Italy.

Background:
Management of axillary nodes in breast cancer (BC) remains controversial. Increasingly, node-positive patients receive primary systemic therapy (PST), achieving axillary downstaging in up to 70% of cases. However, current imaging methods, despite being pivotal in the choice for PST, show limited accuracy in assessing treatment response. This study evaluated the diagnostic performance of hybrid [18F]FDG PET/MRI as non-invasive, single-step tool for post-PST nodal assessment.
Methods:
This prospective, single-arm, monocentric interventional trial (SNBvsPET/MRI1, ClinicalTrials.gov NCT04826211) was conducted at San Raffaele Scientific Institute, Milan. Patients with node-positive BC eligible for PST were enrolled between September 2019 and December 2024. In addition to routine imaging, including axillary ultrasound (A-US), [18F]FDG PET/MRI was performed before and after PST. Scans were independently reviewed by two radiologists and two nuclear medicine physicians. Final pathology served as the reference standard.
Findings:
Of 109 screened patients, 68 were included in the final analysis Mean(SD) age was 52.3(11.0) years. Residual axillary disease was pathologically confirmed in 30(44.2%) patients. [18F]FDG PET/MRI correctly identified 16 cases (sensitivity 53.3%, specificity 68.4%, PPV 57.1%, NPV 65.0%). Diagnostic accuracy varied by BC subtype with higher PPV in luminal (85.7%) and greater NPV in HER2+ and triple-negative tumors (83.3%). Overall, the performance of [18F]FDG PET/MRI and A-US were not significantly different (p > 0.05).
Interpretations:
[18F]FDG PET/MRI accuracy for axillary staging in node-positive BC patients following PST is limited. Our findings are hypothesis-generating to design future trials and suggest that tailoring imaging to molecular subtype may optimize axillary evaluation and better inform surgical decision-making after PST.
