Related Experiment Video
Updated: Aug 6, 2026


In Vivo Infection with Leishmania amazonensis to Evaluate Parasite Virulence in Mice
Published on: February 20, 2020
[Visceral leishmaniasis with suspected autoimmune disease: A report of 2 cases]
Fan Sun1, Maomao Chen1, Aixin Huo1
1Department of Rheumatology and Immunology, Yan'an University Affiliated Hospital, Yan'an 716000, Shaanxi, China.

Abstract:
Visceral leishmaniasis (VL) is a rare parasitic infection characterized by distinctive features, including the overproduction of various autoantibodies by B cells, which may mimic manifestations and antibody profiles associated with autoimmune diseases. In this report, we presented two patients diagnosed with visceral leishmaniasis who were initially suspected of having an autoimmune disease. We discussed the similarities and differences between visceral leishmaniasis and autoimmune diseases based on clinical presentation, physical examination findings, laboratory tests, diagnosis, and treatment. Case 1 involved a 69-year-old female patient who was admitted to the hospital due to irregular fever. Physical examination revealed splenomegaly. Laboratory investigations indicated pancytopenia along with an abnormal autoantibody profile. The initial bone marrow aspirate demonstrated: Proliferative changes in the bone marrow, and abnormal lymphocytes in peripheral blood accounting for approximately 6%. Auto-immune disease was initially considered, and hormone therapy did not respond well. Further screening for immunological disorders, infections, tumors, and other related conditions was conducted. A second bone marrow aspirate was performed actively which revealed Leishman-Donovan body. Subsequent nuc-leic acid detection of pathogenic microorganisms confirmed the presence of Leishmania through real-time fluorescence PCR analysis; thus, confirming a diagnosis of visceral leishmaniasis. Case 2 involved a 41-year-old male patient who presented with fever and abdominal distension. Similar to Case 1, physical examination also showed splenomegaly alongside an abnormal autoantibody profile. During treatment, he tested positive for Leishmania infection and was ultimately diagnosed with visceral leishmaniasis complicated by hemophagocytic syndrome. The symptoms observed in the two patients included recurrent fever, anorexia, and splenomegaly. To further investigate the cause of pancytopenia and to rule out factors such as surgery, infection, tumors, and other related conditions, an abnormal antinuclear antibody profile was assessed. The initial misdiagnosis pointed towards autoimmune diseases; however, during treatment, visceral leishmaniasis infection was identified, leading to a final diagnosis of visceral leishmaniasis. The gold standard for diagnosing visceral leishmaniasis involves detecting Leishmania bodies through aspiration of bone marrow, lymph nodes, or spleen. The positive rate for bone marrow puncture is approximately 80% to 90%. However, clinical practice may encounter missed detections due to limitations associated with the puncture site. This underscores the necessity for secondary punctures when warranted. Addi-tionally, patients presenting with splenomegaly accompanied by trilineage cytopenia often seek care from Department of Hematology or Department of Rheumatology and Immunology rather than Department of Infection. This tendency can contribute to both misdiagnosis and missed diagnoses. It is hoped that this case report will offer valuable insights for clinicians in enhancing their diagnostic capabilities and improving the clinical detection rates of visceral leishmaniasis.

Related Concept Videos
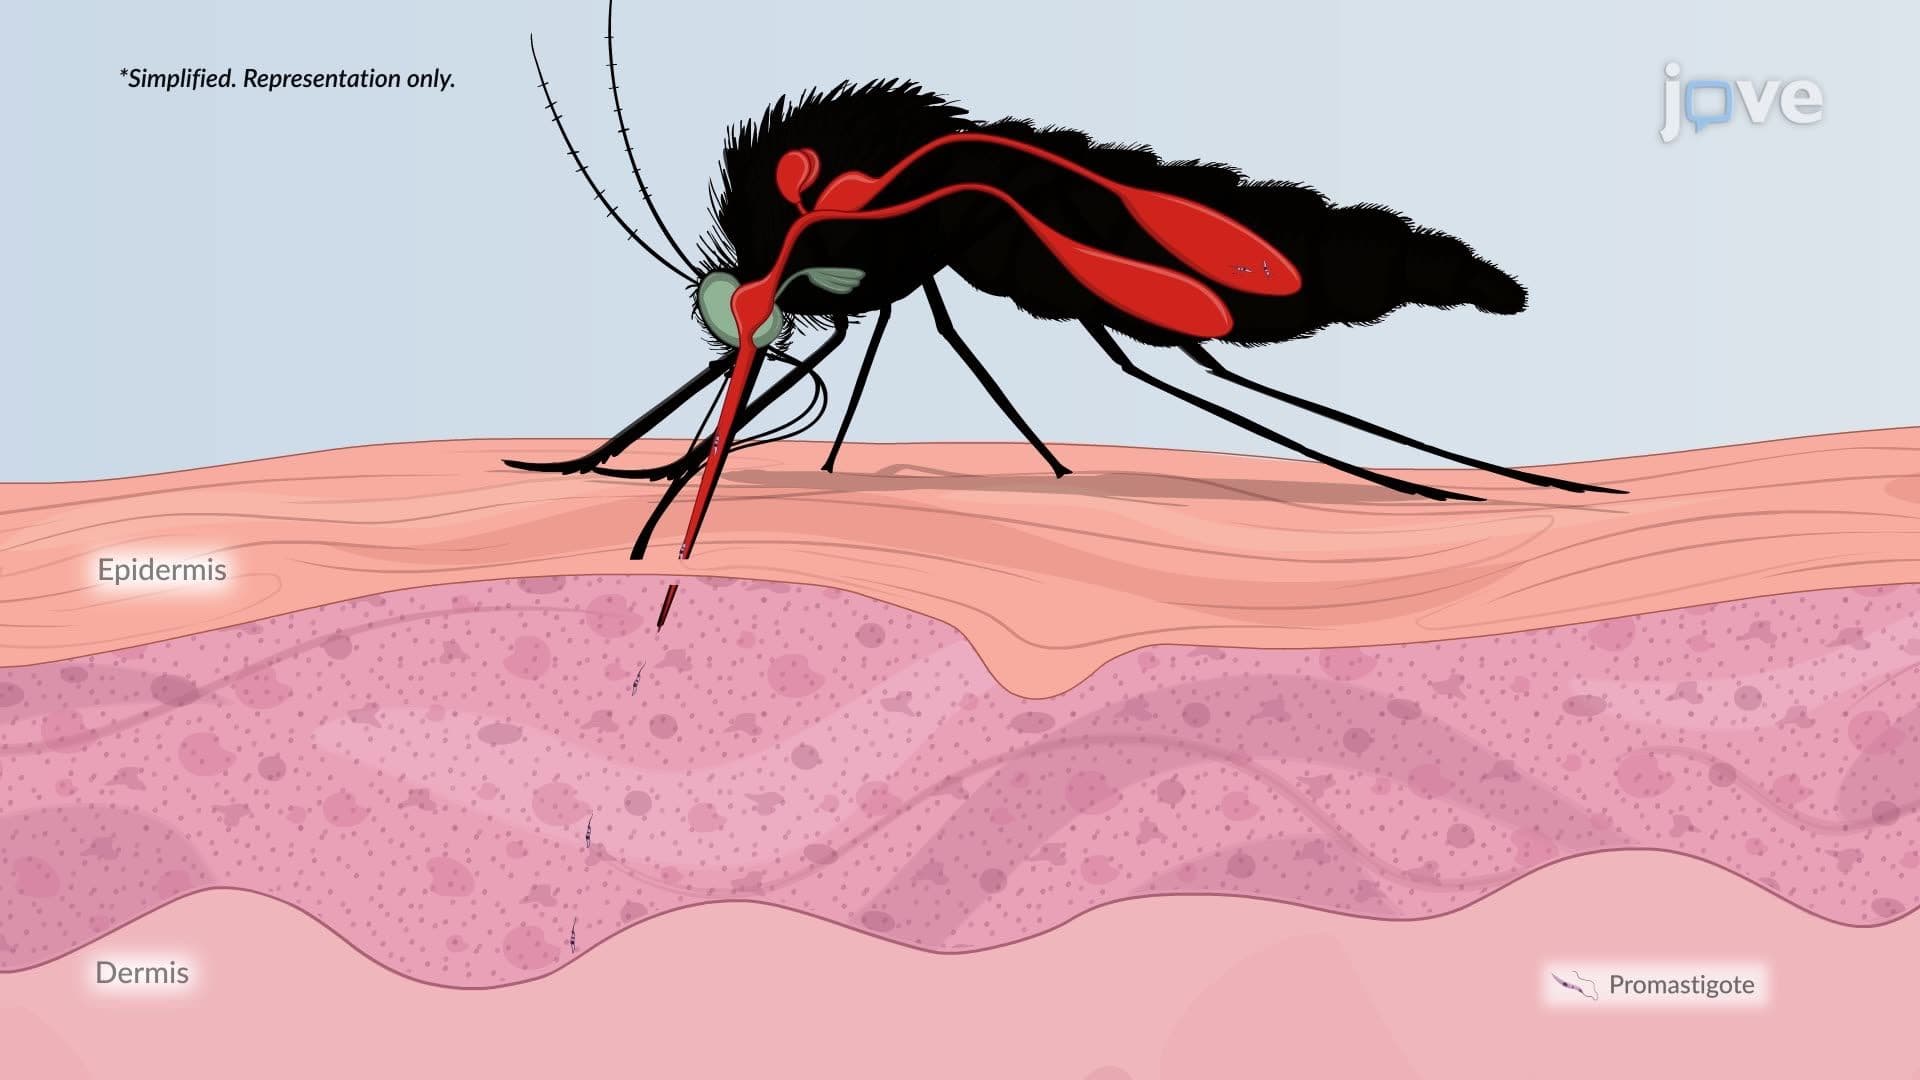 01:30
Leishmaniasis
 01:21
Antiprotozoal Agents