Related Experiment Video
Updated: Aug 6, 2026
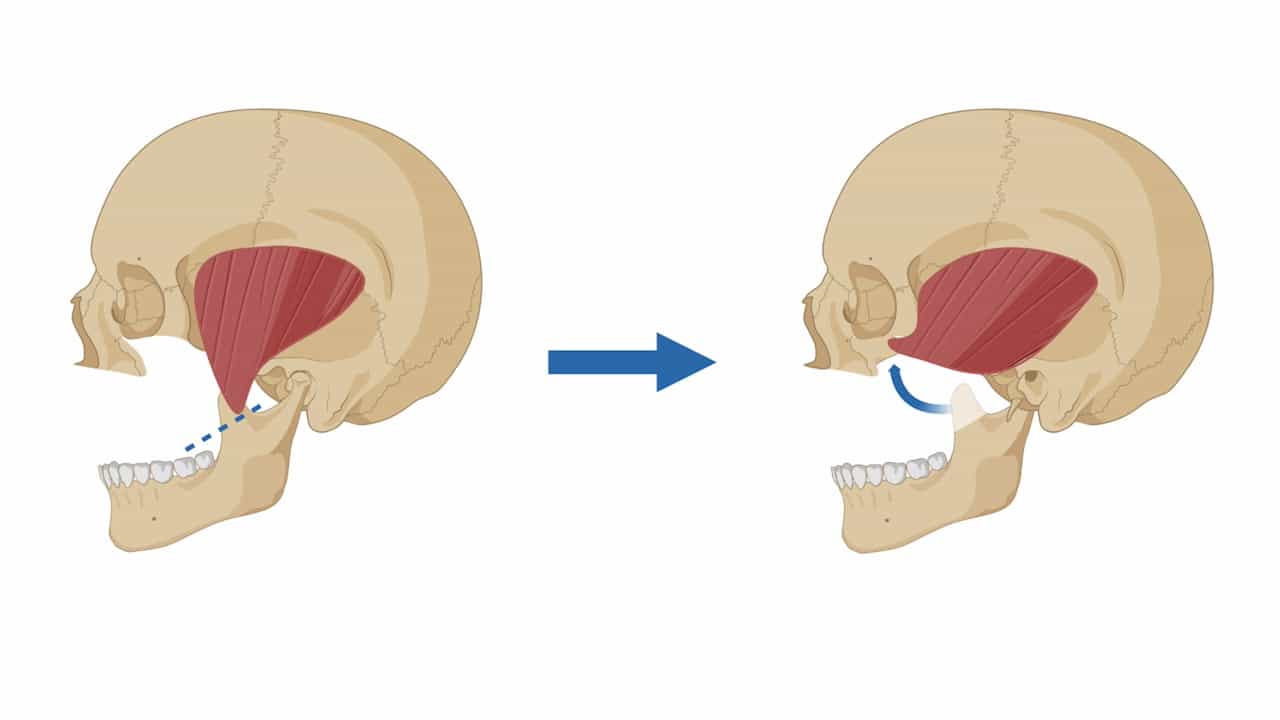

Coronoid-Temporalis Pedicled Flap for Orbital Floor Defect Reconstruction
Published on: December 5, 2025
Extended Forehead Flap With Lowered Pivot Point
Ho Hyung Lee1, An Gyu Jung1, Matias Cancino Abarca2
1Department of Plastic and Reconstructive Surgery, University of Ulsan College of Medicine, Asan Medical Center, Seoul, Korea.

Background:
When the paramedian forehead flap pivot is positioned at or just above the eyebrow, extensive defects may require cephalic extension toward the hairline, increasing donor-site scar burden. We evaluated whether inferior translation of the pivot below the medial eyebrow provides measurable geometric benefit without increasing complications.
Methods:
A single-surgeon retrospective review was performed of consecutive patients undergoing multi-subunit nasal reconstruction with a supratrochlear-based paramedian forehead flap (December 2016 to August 2023). Patients were grouped into a conventional cohort (pivot at or just above the eyebrow without brow transection) and a lowered-pivot cohort (pivot lowered to the midpoint between the eyebrow and medial canthus). Standardized photographs were analyzed using scale-free ratios to calculate shortening fraction (SF=c/a) and proportional forehead-scar reduction [2c/(B-A)]. Complications were compared between techniques; within the lowered-pivot cohort, exploratory analyses assessed associations between SF and complications.
Results:
Thirty patients met the inclusion criteria (conventional, n=16; lowered pivot, n=14). In the lowered-pivot cohort, mean SF was 0.156±0.025 and mean proportional forehead-scar reduction was 0.432±0.106 [2c/(B-A)]. Complication rates did not differ significantly between groups, including unintended hair-bearing transfer (43.8% vs. 28.6%, P =0.466), partial distal necrosis (6.3% vs. 7.1%, P =1.000), and donor-site scarring (62.5% vs. 35.7%, P =0.272) in the conventional versus lowered-pivot cohorts, respectively. Within the lowered-pivot cohort, SF was not associated with hair-bearing transfer ( P =0.354), partial distal necrosis ( P =0.532), or donor-site scarring ( P =0.638) on exploratory analysis.
Conclusions:
Notably, lowering the pivot point by a given distance reduces the required cephalic donor incision by approximately twice that distance in the proposed geometric model, representing a substantial reduction in donor-site scar burden. Inferior translation of the pivot below the eyebrow provides measurable geometric benefit while maintaining a similar complication profile in this cohort. This modification may be useful when additional reach is needed, and tissue expansion is not planned.
