Related Experiment Video
Updated: Aug 6, 2026

Robotic Duodenum-preserving Total Pancreatic Head Resection for Intraductal Papillary Mucinous Neoplasms
Published on: April 17, 2026
Pancreatic mucinous cystic neoplasms in a young female: A case report
Ethan Burg1,2, Gabrielle K Sharbin1,3, Max E Edeson1,4
1Department of Gastroenterology, Hackensack Meridian School of Medicine, Hackensack University Medical Center, Hackensack, NJ.

Rationale:
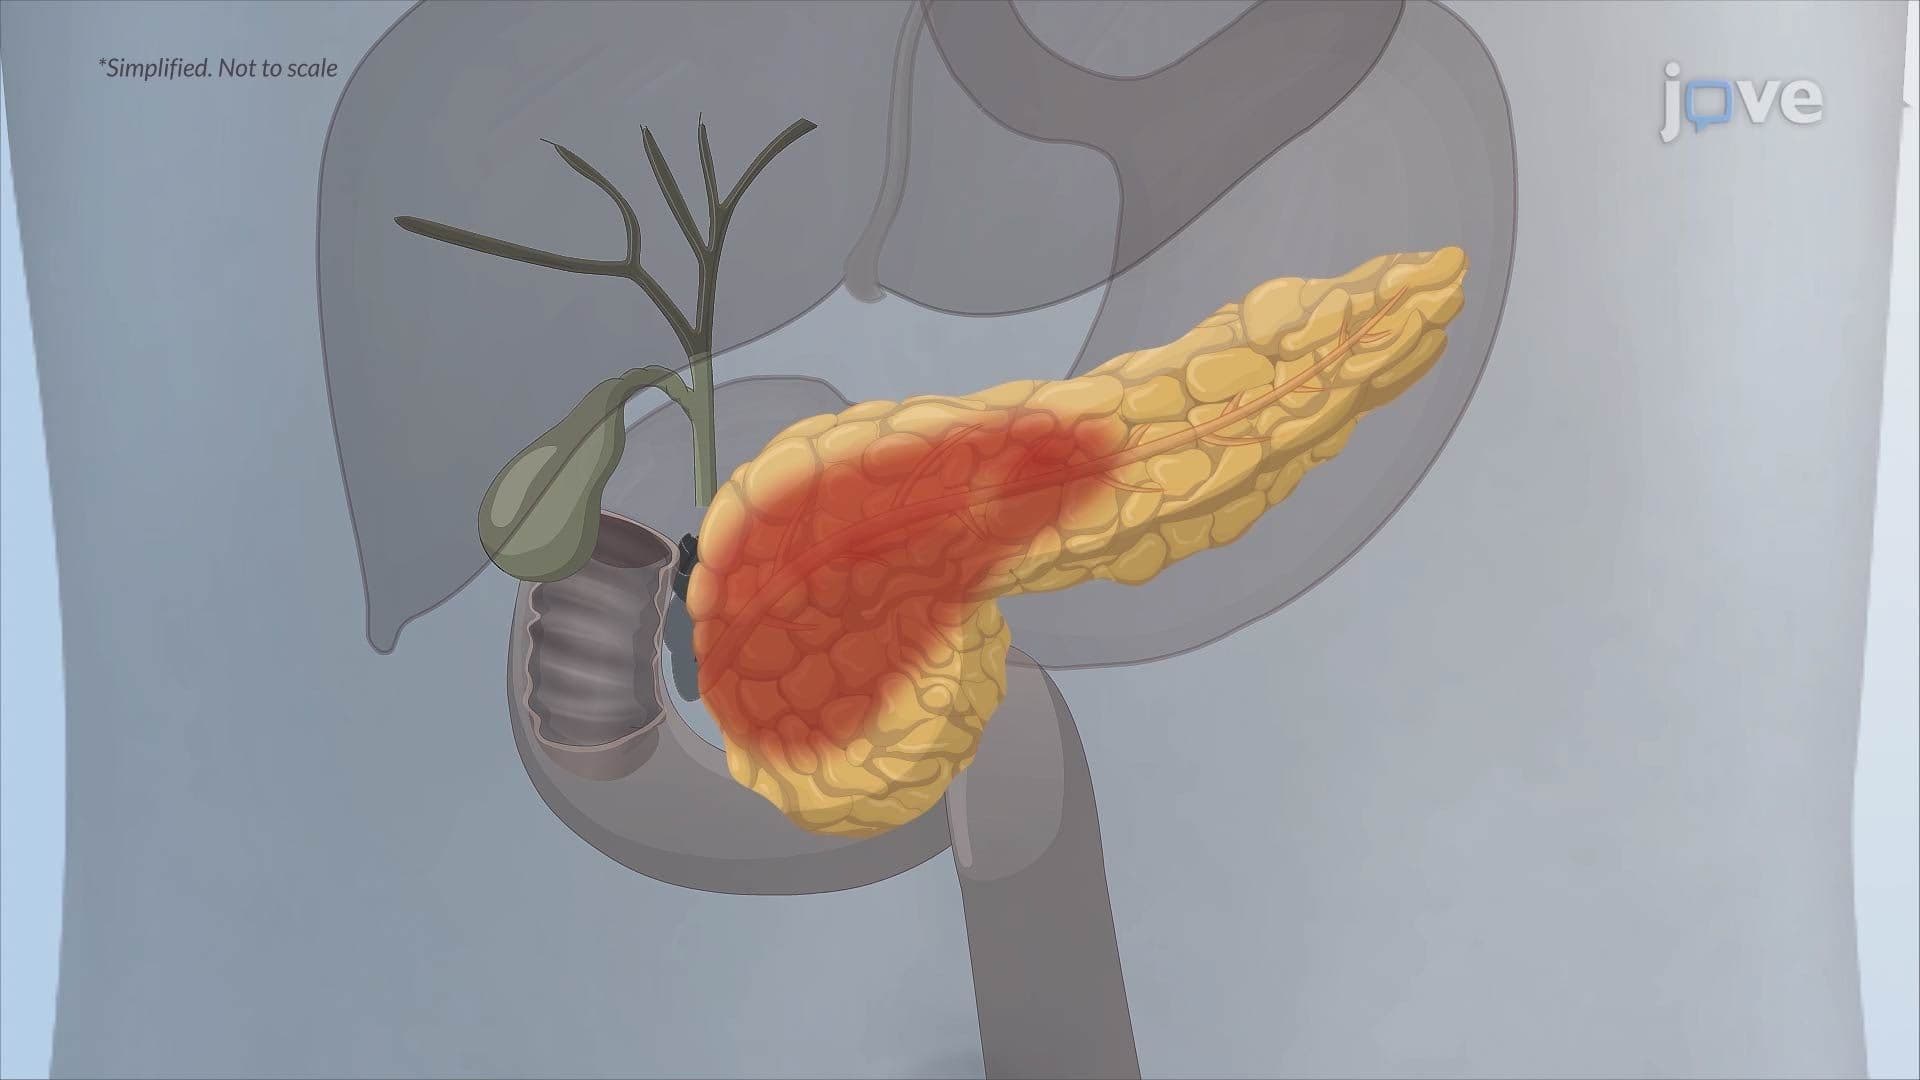
Pancreatic cystic neoplasms (PCNs) encompass a wide spectrum of disease from benign to malignant. Mucinous cystic neoplasms (MCNs) are the second most common PCNs, typically occurring as solitary masses in the pancreatic body or tail of middle-aged women. They are characterized by elevated cyst fluid carcinoembryonic antigen (CEA) and low amylase due to lack of ductal communication. While MCNs have malignant potential, and lesions >3 cm are higher risk, size alone is not an absolute predictor of malignancy. We present a rare case of an exceptionally large, yet benign, PCN in a 24-year-old female, with a paradoxical cyst fluid biomarker profile.
Patient Concerns:
A 24-year-old female with a known pancreatic tail cystic mass presented with acute-on-chronic abdominal pain, nausea, and vomiting - endorsing epigastric pain for the past year. The lesion was initially identified in January 2024 on imaging, measuring 11.7 × 10.2 × 8.1 cm, with prior non-diagnostic cytology.
Diagnoses:
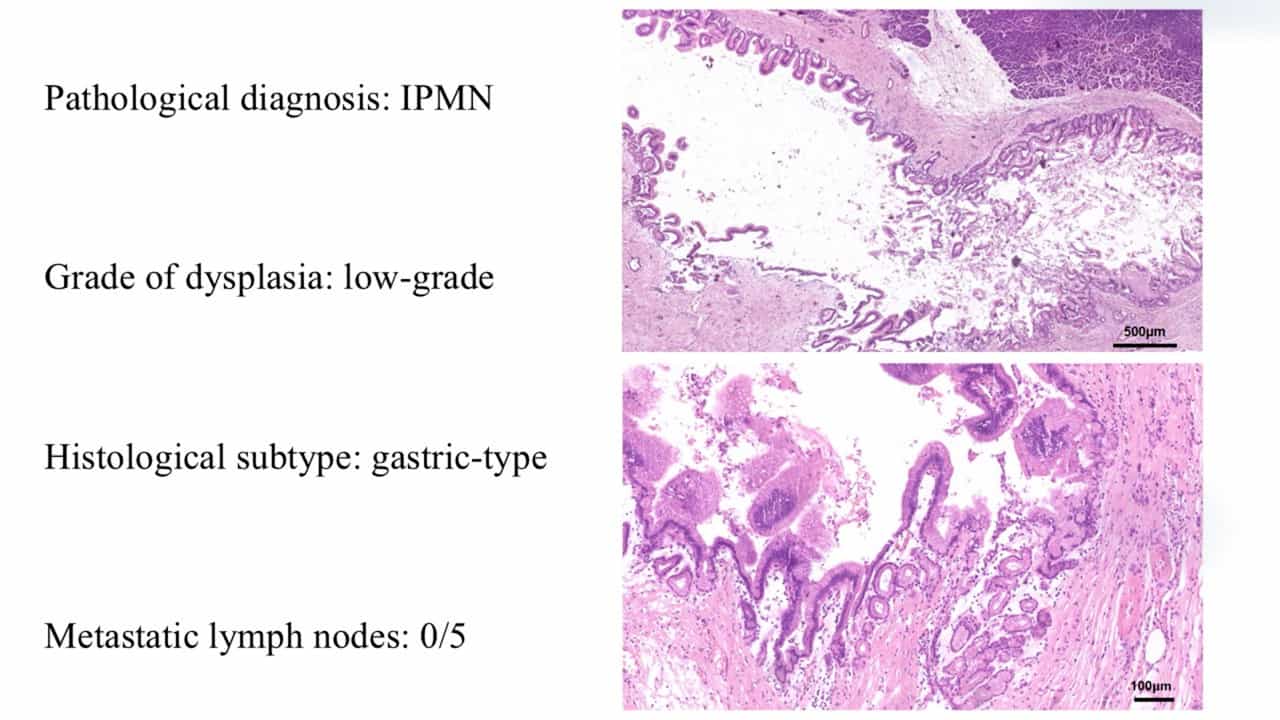
Abdominal magnetic resonance imaging with cholangiopancreatography demonstrated a complex cystic mass measuring 8.4 × 12.8 × 16 cm abutting the pancreas with moderate volume ascites. Endoscopic ultrasound (EUS)-guided fine-needle biopsy revealed a 12 cm complex mass encompassing the distal pancreas. Surgical pathology confirmed a noninvasive, low-grade MCN with no evidence of high-grade dysplasia.
Interventions:
Given the significant symptom burden and cyst size, she underwent distal pancreatectomy with splenectomy; the cystic mass was adherent to the splenic vessels at the hilum, precluding a spleen-sparing procedure.
Outcomes:
Pathology revealed a 14 × 11 × 7 cm multilocular cystic mass consistent with a benign, noninvasive, low-grade MCN. The patient had an uncomplicated post-operative course and is following with outpatient providers.
Lessons:
This case highlights the limitations of cyst size as a predictor of malignancy in MCN. Further, there is a possibility of discordant cyst fluid biomarkers such as low CEA and high amylase as opposed to the inverse, as seen here, which may reflect sample heterogeneity, partial ductal communication, or mixed lesions. This case therefore emphasizes the importance of integrating imaging, cyst fluid biomarkers, histopathology, and molecular testing together for accurate classification and individualized management of PCNs.